Related Experiment Video
Updated: May 21, 2026


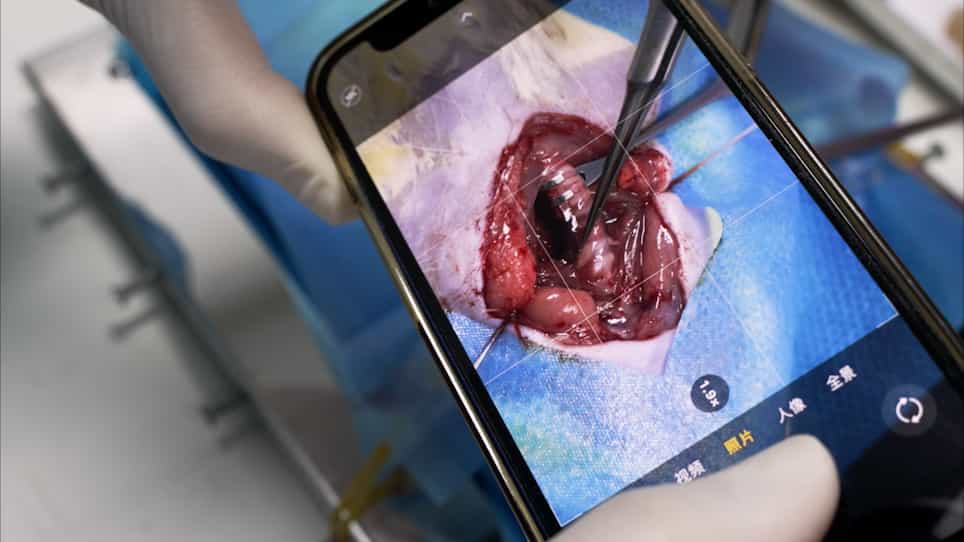
Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Development and treatment of tertiary hyperparathyroidism in patients with pseudohypoparathyroidism type 1B
Nicola M Neary1, Diala El-Maouche, Rachel Hopkins
1Metabolic Diseases Branch, National Institute of Diabetes and Digestive and Kidney Diseases, National Institutes of Health, Bethesda, Maryland 20892-1752, USA.

Context:
Pseudohypoparathyroidism type 1B (PHP1B) patients have PTH resistance at the renal proximal tubule and develop hypocalcemia and secondary hyperparathyroidism. Hyperparathyroid bone disease also develops in some patients. PHP1B patients are at theoretical risk of developing tertiary hyperparathyroidism.
Setting:
Patients were studied in a clinical research center.
Patients:
Five female PHP1B patients presented with hypercalcemia and elevated PTH.
Intervention:
Patients either underwent parathyroidectomy (n = 4) or received cinacalcet (n = 1).
Main Outcome Measures:
Serum calcium and PTH were serially measured before and after intervention.
Results:
Five PHP1B patients developed concomitantly elevated serum calcium and PTH levels (range, 235-864 ng/liter) requiring termination of calcium and vitamin D therapy (time after diagnosis, 21-42 yr; median, 34 yr), consistent with tertiary hyperparathyroidism. Four patients underwent parathyroidectomy with removal of one (n = 2) or two (n = 2) enlarged parathyroid glands. Calcium and vitamin D therapy was reinstituted postoperatively, and at 93-month median follow-up, PTH levels ranged between 56 and 182 (normal, <87) ng/liter. One patient was treated with cinacalcet, resulting in resolution of hypercalcemia.
Conclusions:
PHP1B patients are at risk of developing tertiary hyperparathyroidism and/or hyperparathyroid bone disease and should therefore be treated with sufficient doses of calcium and vitamin D to achieve serum calcium and PTH levels within or as close to the normal range as possible. Surgery is the treatment of choice in this setting. Cinacalcet may be a useful alternative in those who do not undergo surgery.
Related Concept Videos
 01:23
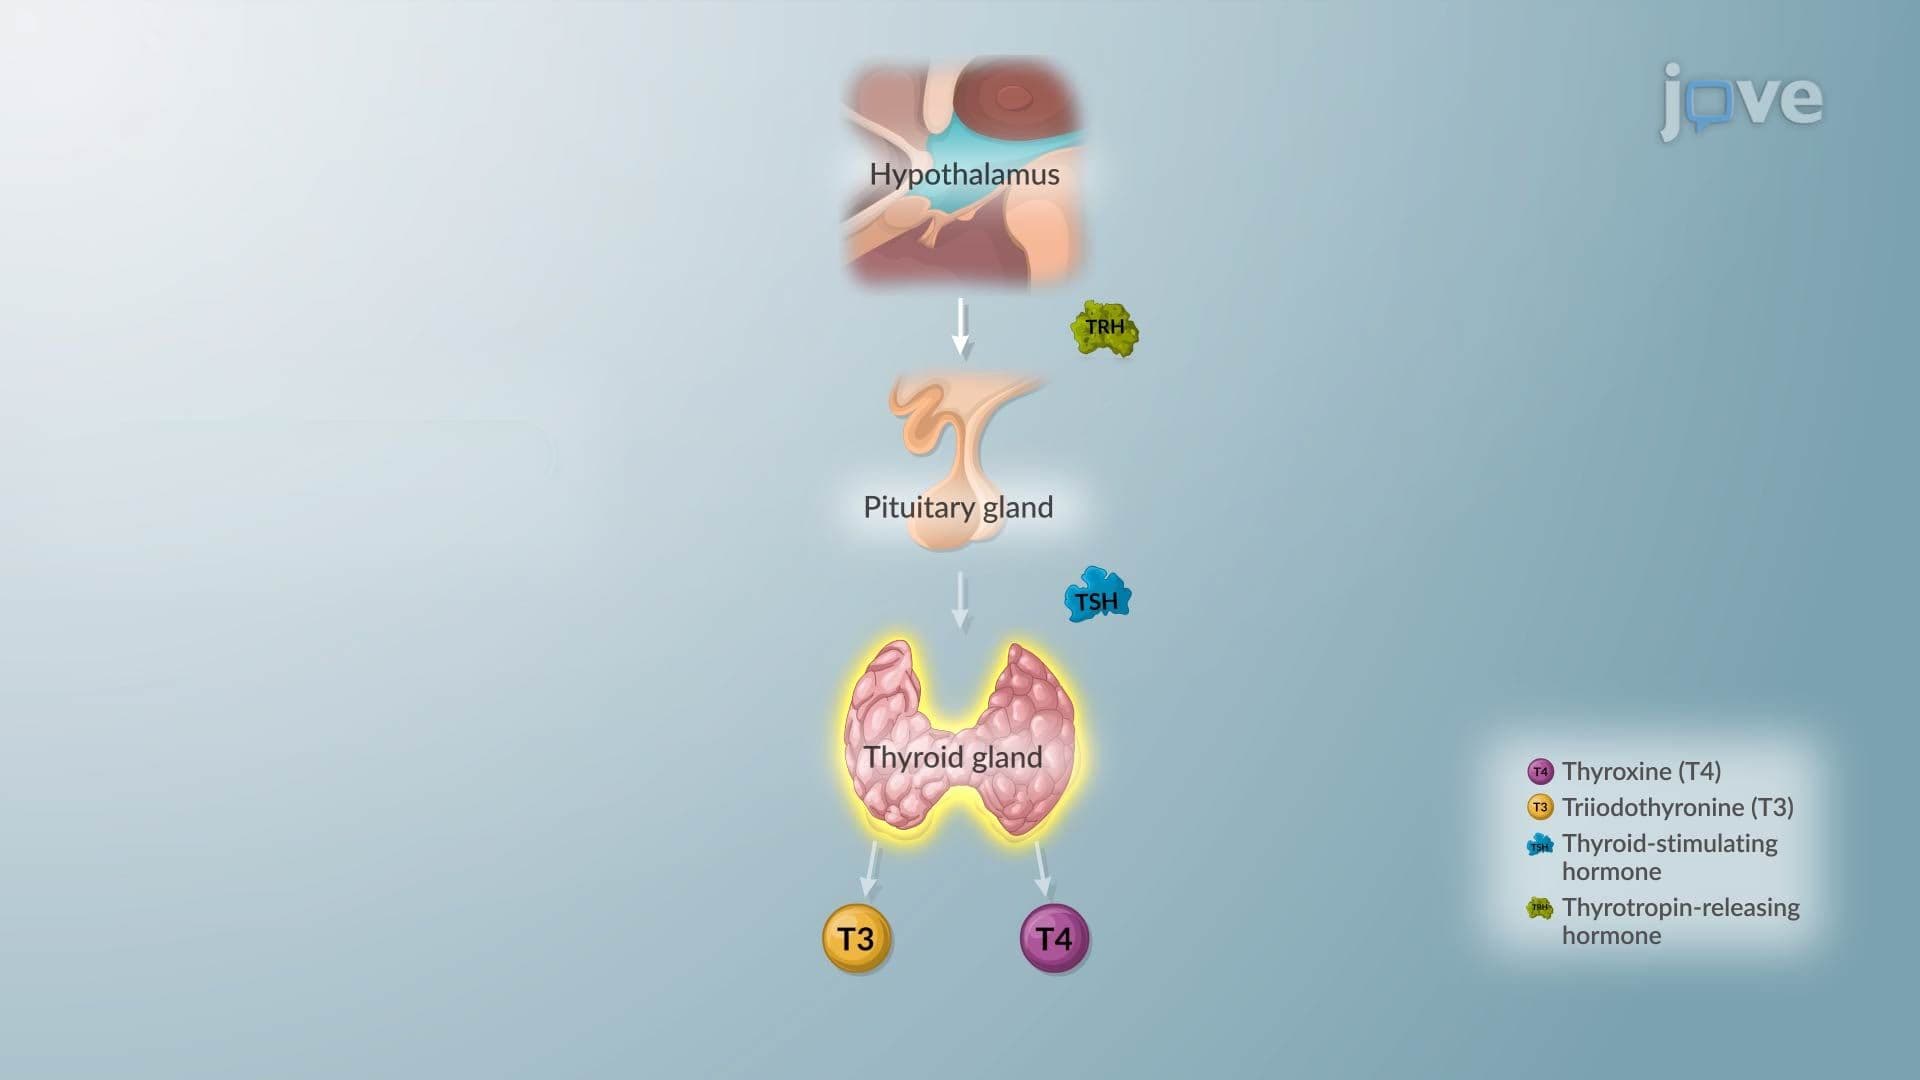
Hypothyroidism II: Pathophysiology
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:27
Hyperthyroidism II: Pathophysiology
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Hyperthyroidism I: Introduction