Related Experiment Video
Updated: May 21, 2026


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Clinical and microbiological efficacy of continuous versus intermittent application of meropenem in critically ill

Introduction:
Meropenem bactericidal activity depends on the time when the free drug concentrations remain above the minimum inhibitory concentration of pathogens. The goal of this study was to compare clinical and bacteriological efficacy of continuous meropenem infusion versus bolus administration in critically ill patients with severe infection, and to evaluate the safety of both dosing regimens.
Methods:
Patients admitted to the interdisciplinary Intensive Care Unit (ICU) who suffered from severe infections and received meropenem were randomized either in the Infusion group (n = 120) or in the Bolus group (n = 120). Patients in the Infusion group received a loading dose of 2 g of meropenem followed by a continuous infusion of 4 g of meropenem over 24 hours. Patients in the Bolus group were given 2 g of meropenem over 30 minutes every 8 hours. Clinical and microbiological outcome, safety, meropenem-related length of ICU and hospital stay, meropenem-related length of mechanical ventilation, duration of meropenem treatment, total dose of meropenem, and ICU and in-hospital mortality were assessed.
Results:
Clinical cure at the end of meropenem therapy was comparable between both groups (83.0% patients in the Infusion vs. 75.0% patients in the Bolus group; P = 0.180). Microbiological success rate was higher in the Infusion group as opposed to the Bolus group (90.6% vs. 78.4%; P = 0.020). Multivariate logistic regression identified continuous administration of meropenem as an independent predictor of microbiological success (OR = 2.977; 95% CI = 1.050 to 8.443; P = 0.040). Meropenem-related ICU stay was shorter in the Infusion group compared to the Bolus group (10 (7 to 14) days vs. 12 (7 to 19) days; P = 0.044) as well as shorter duration of meropenem therapy (7 (6 to 8) days vs. 8 (7 to 10) days; P = 0.035) and lower total dose of meropenem (24 (21 to 32) grams vs. 48 (42 to 60) grams; P < 0.0001). No severe adverse events related to meropenem administration in either group were observed.
Conclusions:
Continuous infusion of meropenem is safe and, in comparison with higher intermittent dosage, provides equal clinical outcome, generates superior bacteriological efficacy and offers encouraging alternative of antimicrobial therapy in critically ill patients.
Insights
Continuous meropenem infusion in critically ill patients demonstrated superior microbiological success compared to intermittent bolus dosing. This safe, effective method offers an alternative antimicrobial therapy, reducing treatment duration and total meropenem dosage.
Area of Science:
- Pharmacology
- Infectious Diseases
- Critical Care Medicine
Background:
- Meropenem's efficacy relies on maintaining drug concentrations above pathogen minimum inhibitory concentrations.
- Severe infections in critically ill patients necessitate optimized antibiotic dosing strategies.
Purpose of the Study:
- To compare the clinical and bacteriological efficacy of continuous meropenem infusion versus bolus administration.
- To evaluate the safety of both meropenem dosing regimens in critically ill patients.
Main Methods:
- Randomized controlled trial involving 240 critically ill patients with severe infections.
- Patients were assigned to either continuous meropenem infusion (4 g/24h) or intermittent bolus dosing (2 g every 8 hours).
- Outcomes assessed included clinical and microbiological success, safety, length of stay, mechanical ventilation, and mortality.
Main Results:
- Microbiological success rates were significantly higher with continuous infusion (90.6%) versus bolus (78.4%) (P=0.020).
- Continuous infusion was an independent predictor of microbiological success (OR=2.977; P=0.040).
- No significant difference in clinical cure rates was observed; however, continuous infusion led to shorter ICU stays and reduced total meropenem dosage.
Conclusions:
- Continuous meropenem infusion is a safe and effective alternative for treating severe infections in critically ill patients.
- It offers superior bacteriological efficacy compared to intermittent dosing, with comparable clinical outcomes.
- This approach optimizes antimicrobial therapy, potentially reducing treatment costs and duration.

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:15
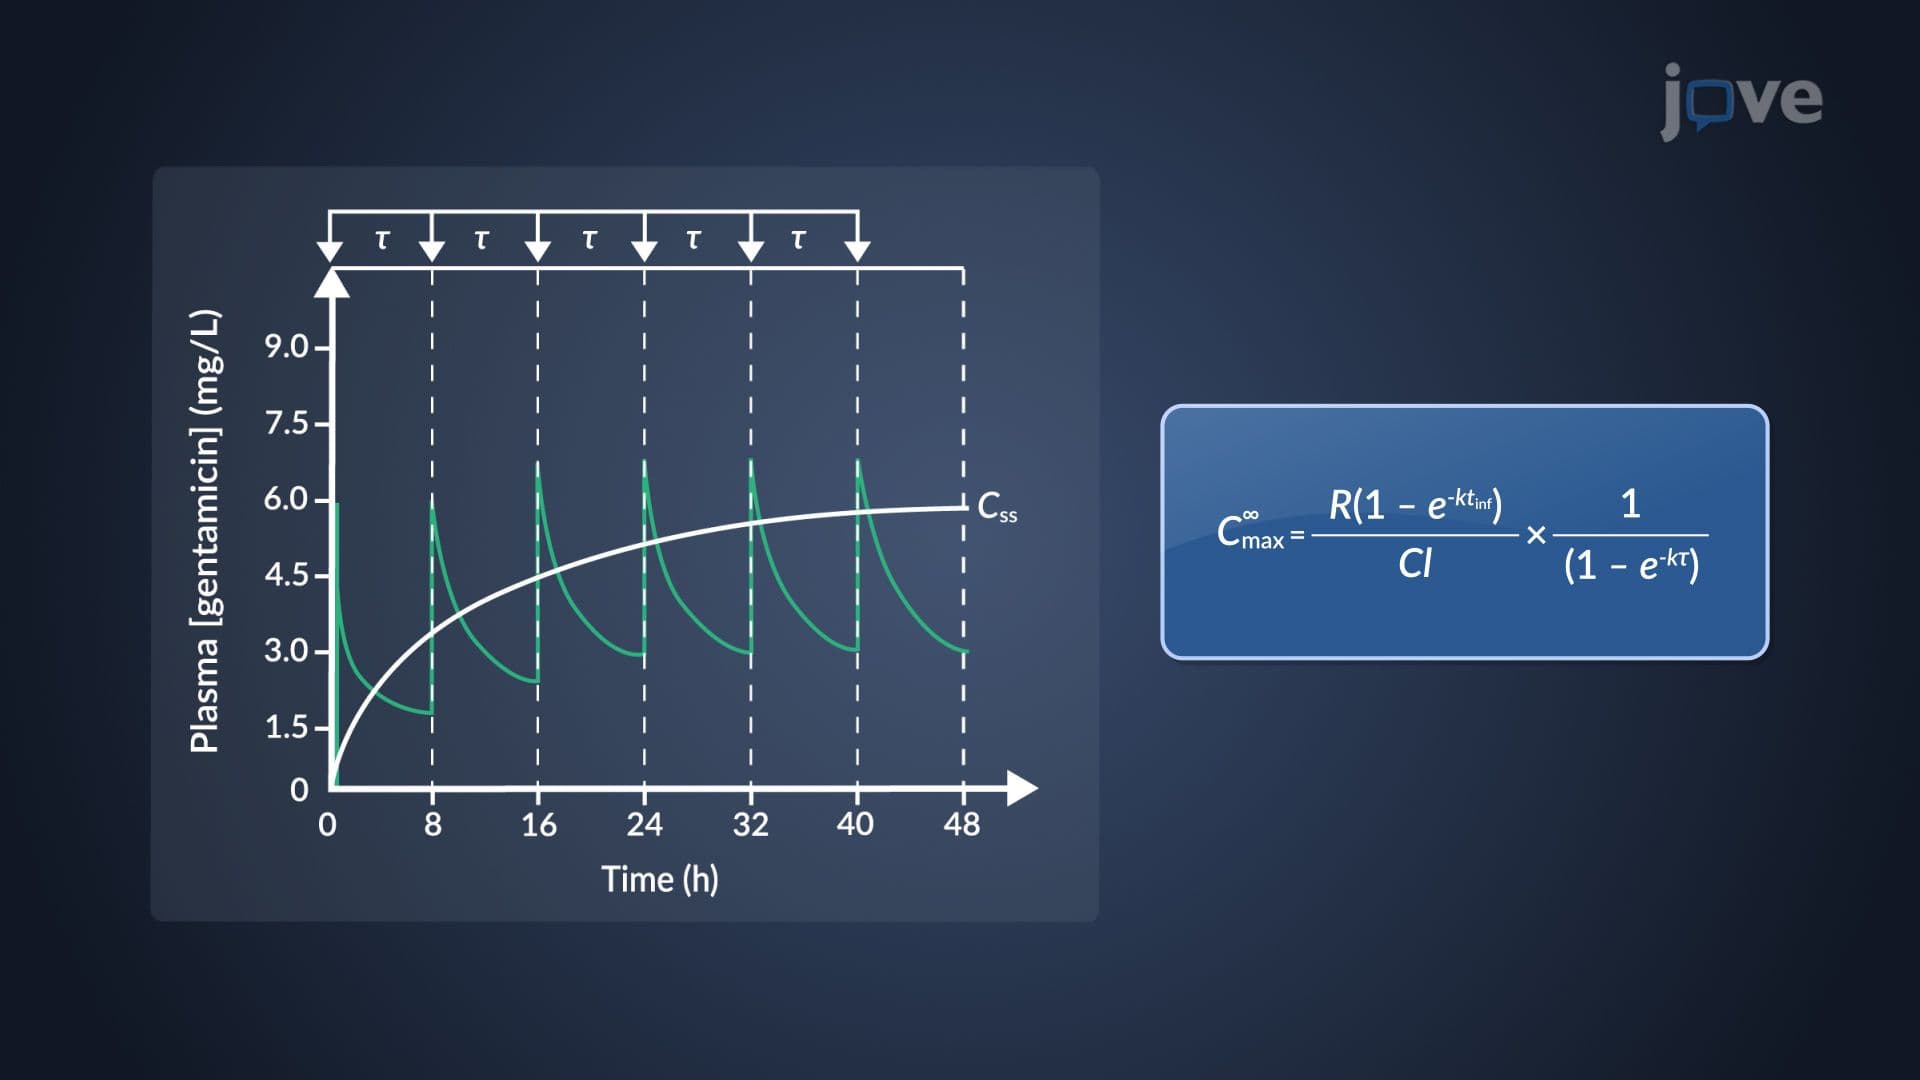
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Antimicrobial Effectiveness
 01:25
Clinical Significance of Antibiotic Resistance
 01:24
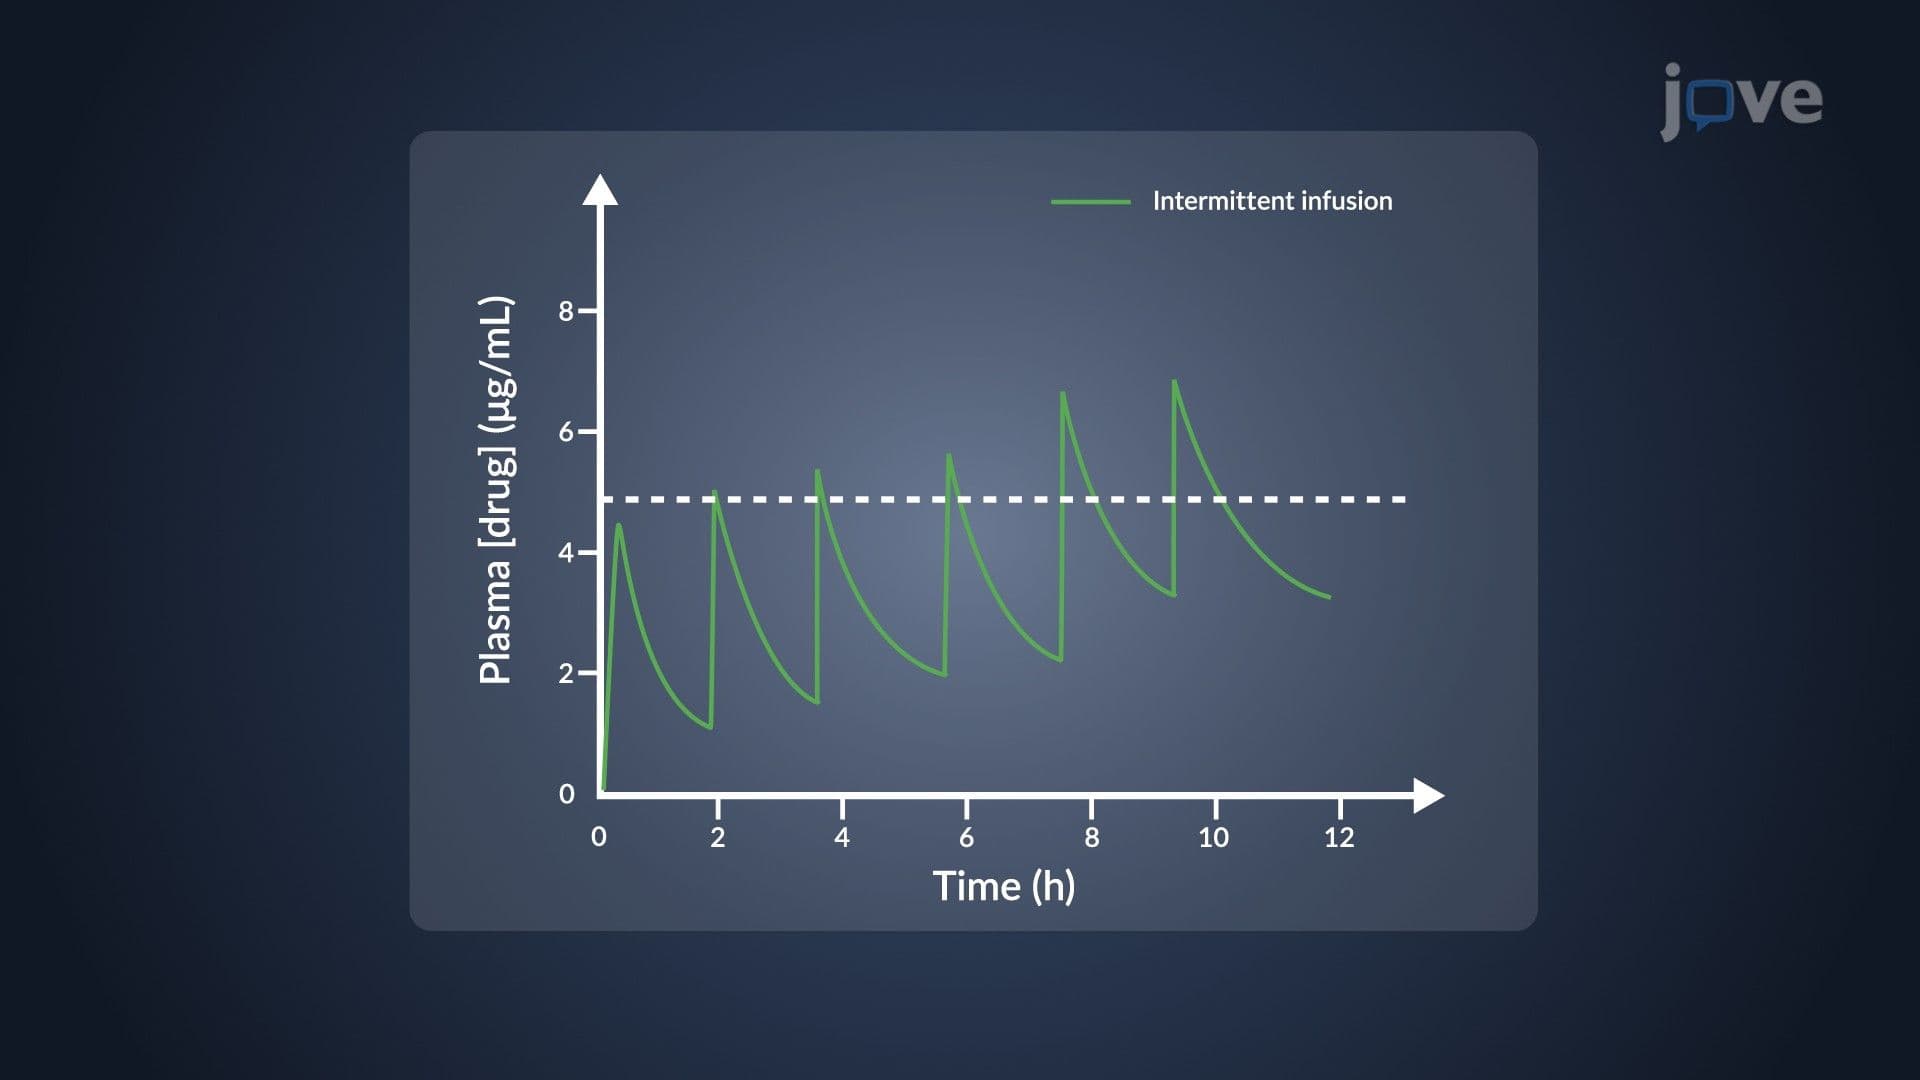
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence