Related Experiment Video
Updated: May 20, 2026
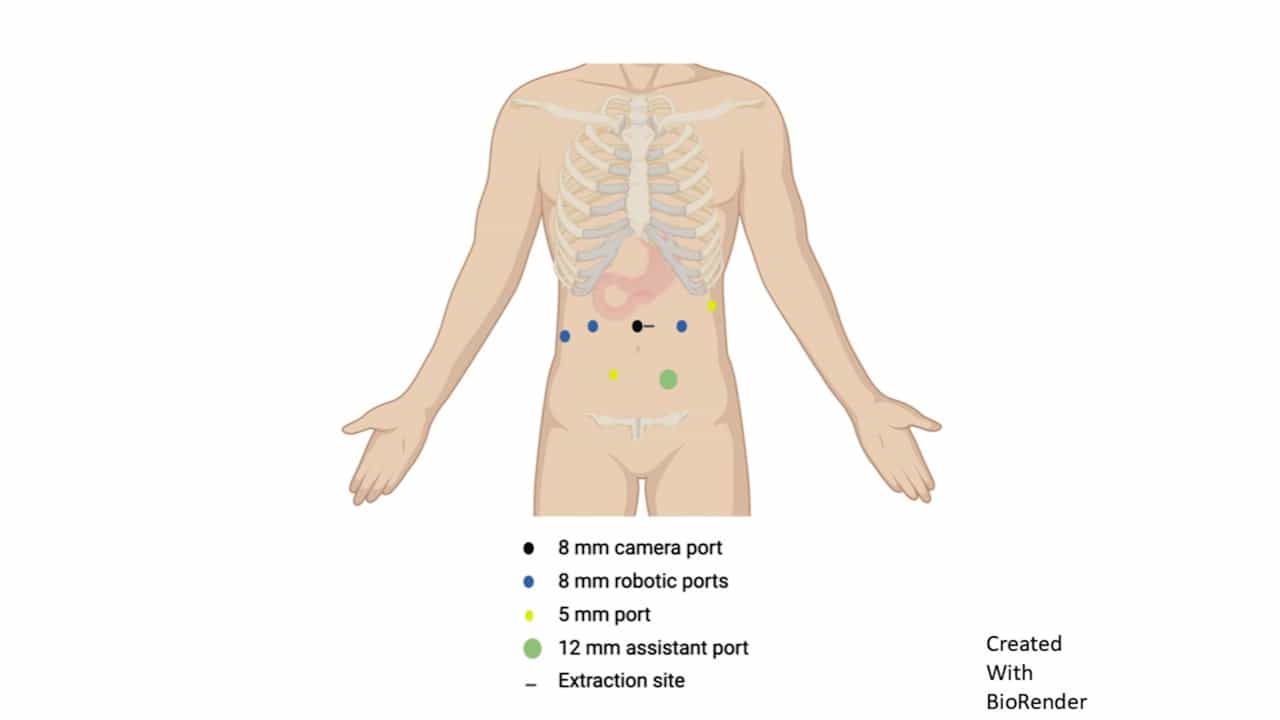

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Adjuvant therapy of gastrointestinal stromal tumors (GIST)
Paolo G Casali1, Elena Fumagalli, Alessandro Gronchi
1Adult Mesenchymal Tumour Medical Oncology Unit, Istituto Nazionale Tumori, Via G. Venezian 1, 20133, Milano, Italy. paolo.casali@istitutotumori.mi.it

Imatinib was proven to be effective for the adjuvant treatment of localized, surgically excised, gastrointestinal stromal tumors (GIST). Currently, there is proof that it is able to delay relapse and prolong survival. An effect on cure rate of localized GIST is still to be proven, given the shape of relapse-free survival curves, which apparently tend to overlap after 2-3 years from completion of the adjuvant period. Although observation for a longer follow-up is needed, attempts to prolong adjuvant therapy beyond the currently standard 3 years have been made and the results are awaited. However, the impact of more prolonged adjuvant intervals on secondary resistance is unknown, so that standard practice is still 3 years in most institutions. The adjuvant choice should be based on a rather precise identification of the relapse risk of the single patient, reserving treatment to the high-risk subgroups. The choice also should be personalized on the basis of genotype: generally, PDGFRA D842V mutated and wild-type GIST are excluded. Additional results from completed trials on a longer follow-up are awaited to further refine such "precision" decision-making. There are several instances in which part of the "adjuvant" treatment may be administered preoperatively, even on the face of a surgically resectable GIST, to make surgery more limited and/or safer.
Imatinib was proven to be effective for the adjuvant treatment of localized, surgically excised, gastrointestinal stromal tumors (GIST). Currently, there is proof that it is able to delay relapse and prolong survival. An effect on cure rate of localized GIST is still to be proven, given the shape of relapse-free survival curves, which apparently tend to overlap after 2-3 years from completion of the adjuvant period. Although observation for a longer follow-up is needed, attempts to prolong adjuvant therapy beyond the currently standard 3 years have been made and the results are awaited. However, the impact of more prolonged adjuvant intervals on secondary resistance is unknown, so that standard practice is still 3 years in most institutions. The adjuvant choice should be based on a rather precise identification of the relapse risk of the single patient, reserving treatment to the high-risk subgroups. The choice also should be personalized on the basis of genotype: generally, PDGFRA D842V mutated and wild-type GIST are excluded. Additional results from completed trials on a longer follow-up are awaited to further refine such "precision" decision-making. There are several instances in which part of the "adjuvant" treatment may be administered preoperatively, even on the face of a surgically resectable GIST, to make surgery more limited and/or safer.

Related Concept Videos
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
02:57Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:15
Drugs that Stabilize Microtubules
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD
 02:56
Treatment Resistent Cancers
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...