Related Experiment Video
Updated: May 20, 2026
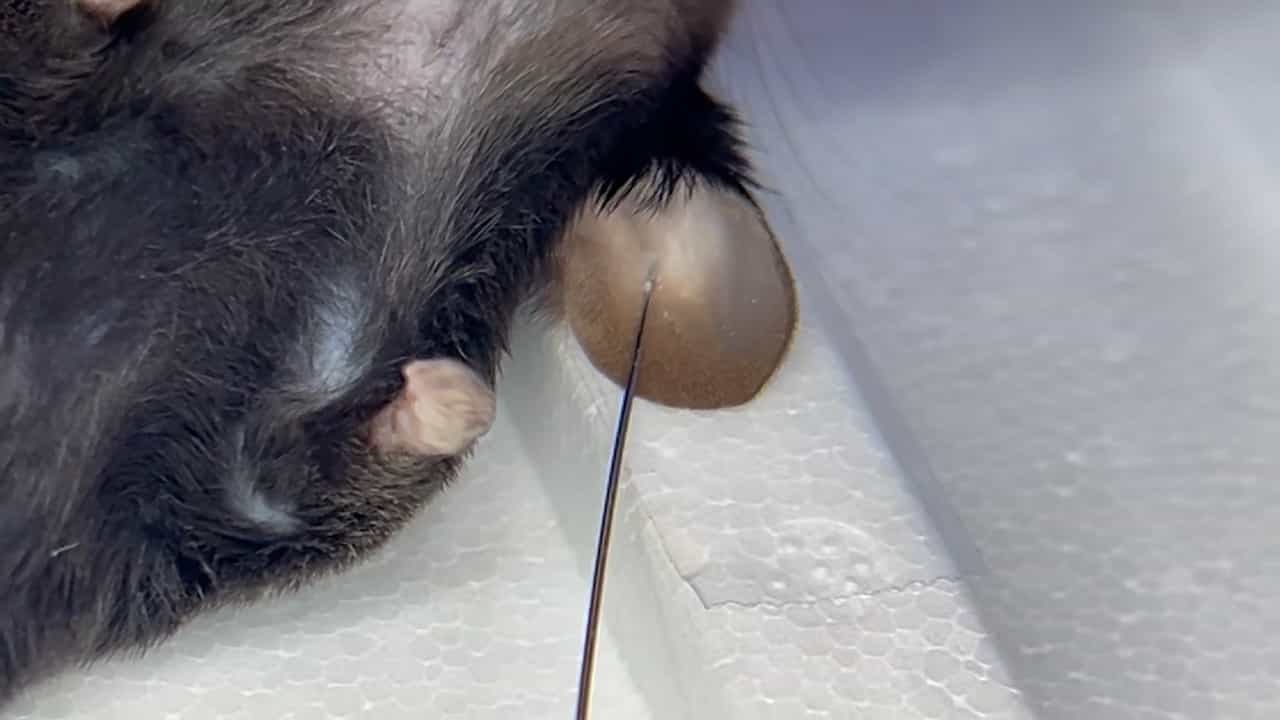
Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
The pharmacokinetics and pharmacodynamics of pulmonary Mycobacterium avium complex disease treatment
Jakko van Ingen1, Eric F Egelund, Adrah Levin
1Division of Mycobacterial and Respiratory Infections, National Jewish Health, Denver, CO, USA. j.vaningen@mmb.umcn.nl

Rationale:
Currently recommended multidrug treatment regimens for Mycobacterium avium complex (MAC) lung disease yield limited cure rates. This results, in part, from incomplete understanding of the pharmacokinetics and pharmacodynamics of the drugs.
Objectives:
To study pharmacokinetics, pharmacodynamics, and drug interactions of multidrug treatment regimens in a large cohort of patients with MAC lung disease.
Methods:
We retrospectively collected pharmacokinetic data of all patients treated for MAC lung disease in the Adult Care Unit at National Jewish Health, Denver, Colorado, in the January 2006 to January 2010 period; we retrospectively calculated areas under the time-concentration curve (AUC). Minimum inhibitory concentrations (MIC) of their MAC isolates were retrieved for pharmacodynamic calculations.
Measurements And Main Results:
We included 531 pharmacokinetic analyses, performed for 481 patients (84% females; mean age, 63 yr; mean body mass index, 21.6). Peak serum concentrations (C(max)) below target range were frequent for ethambutol (48% of patients); clarithromycin (56%); and azithromycin (35%). Concurrent administration of rifampicin led to 68%, 23%, and 10% decreases in C(max) of clarithromycin, azithromycin, and moxifloxacin. C(max)/MIC or AUC/MIC ratios associated with bactericidal activity were seldom met; 57% of patients achieved target ratios for ethambutol, versus 42% for clarithromycin, 19% for amikacin, 18% for rifampicin, and 11% for moxifloxacin.
Conclusions:
Currently recommended regimens for MAC lung disease yield important pharmacologic interactions and low concentrations of key drugs including macrolides. Pharmacodynamic indices for rifampicin, clarithromycin, amikacin, and moxifloxacin are seldom met. This may partly explain the poor outcomes of currently recommended treatment regimens. Trials of new drugs and new dosing strategies are needed.


Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...