Related Experiment Video
Updated: May 20, 2026
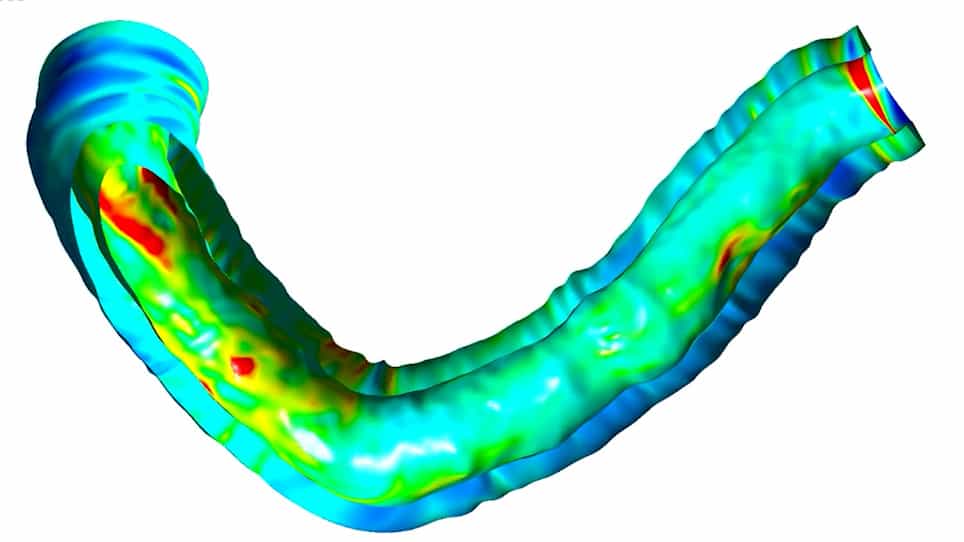
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Association of systemic lupus erythematosus with angiographically defined coronary artery disease: a retrospective
Mala S Kaul1, Sunil V Rao, Linda K Shaw
1Duke University Medical Center, Durham, NC 27710, USA. mala.kaul@duke.edu

Insights
Systemic lupus erythematosus (SLE) is linked to a higher likelihood of coronary artery disease (CAD), even in younger patients without typical risk factors. This study highlights the importance of considering CAD in SLE patients.
Area of Science:
- Cardiology
- Rheumatology
- Immunology
Background:
- Systemic lupus erythematosus (SLE) is a chronic autoimmune disease.
- Cardiovascular disease (CVD) is a leading cause of morbidity and mortality in SLE patients.
- The relationship between SLE and coronary artery disease (CAD) requires further investigation.
Purpose of the Study:
- To investigate the association between SLE and the prevalence of CAD.
- To compare CAD risk factors and all-cause mortality in SLE patients versus non-SLE controls.
- To determine if SLE independently predicts CAD in patients undergoing coronary angiography.
Main Methods:
- A case-control study comparing 86 SLE patients with 258 matched non-SLE controls undergoing coronary angiography.
- Obstructive CAD was defined as ≥70% stenosis in a major epicardial coronary artery.
- Multivariable logistic regression and Cox proportional hazards modeling were used to assess CAD prevalence and mortality risk.
Main Results:
- SLE patients were younger (median 49 vs 70 years) and had lower rates of diabetes and hyperlipidemia.
- After adjusting for risk factors, SLE was significantly associated with an increased likelihood of CAD (OR 2.24).
- SLE patients showed similar CAD severity to controls despite younger age and fewer traditional risk factors.
Conclusions:
- Systemic lupus erythematosus is significantly associated with the presence of coronary artery disease.
- SLE patients exhibit a higher prevalence of CAD despite a younger age and fewer cardiovascular risk factors.
- Coronary angiography confirms a strong link between SLE and obstructive CAD.
Objective:
To determine if systemic lupus erythematosus (SLE) is associated with a higher prevalence of coronary artery disease (CAD) in select patients undergoing coronary angiography. We compared the extent of angiographic abnormalities, CAD risk factors, and all-cause mortality in SLE patients with non-SLE controls.
Methods:
We identified SLE patients (n = 86) and controls matched by sex and year of cardiac catheterization (n = 258) undergoing cardiac catheterization for the evaluation of CAD (median followup duration of 4.3 years). Multivariable logistic regression was used to determine if SLE was associated with obstructive CAD, defined as ≥70% stenosis in a major epicardial coronary artery. Risk-adjusted survival differences between the 2 groups were assessed using Cox proportional hazards modeling.
Results:
The SLE patients (85% women) were younger than the non-SLE patients (median age 49 years versus 70 years; P < 0.001) and were less likely to have diabetes mellitus and hyperlipidemia, but had similar rates of hypertension (70% versus 71%; P = 0.892). In unadjusted analyses, SLE and non-SLE patients had similar rates of obstructive CAD by angiography (52% versus 62%; overall P = 0.11). After adjustment for known CAD risk factors, SLE was associated with a significantly increased likelihood of CAD (odds ratio 2.24 [95% confidence interval (95% CI) 1.08-4.67]). SLE was also associated with a nonsignificant increase in all-cause mortality (hazard ratio 1.683 [95% CI 0.98-2.89], P = 0.060).
Conclusion:
In this selected population, SLE was significantly associated with the presence of CAD as defined by coronary angiography, the gold standard for assessing flow-limiting lesions in this disease. The patients with SLE showed a similar severity of CAD as the controls despite having less than half the rate of diabetes mellitus and being 20 years younger.
Related Concept Videos
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:30
Coronary Artery Disease I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Coronary Artery Disease II: Pathophysiology
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Coronary Artery Disease III: Clinical Manifestations