[The influence of positive end-expiratory pressure on stroke volume variation for the accuracy of evaluating volume]
Related Experiment Video
Updated: May 20, 2026
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Ning Liu1, Qin Gu, Jian-feng Yu
1Intensive Care Unit, the Affiliated Drum Tower Hospital of Nanjing University Medical School, Nanjing, Jiangsu, China.

Objective:
To investigate the influence of positive end-expiratory pressure (PEEP) on hemodynamic and the ability of stroke volume variation (SVV) to predict cardiac preload.
Methods:
Thirty healthy anesthetized pigs were given tracheal intubation and ventilated. With the envelope method, they were all randomly divided into control group(n = 10), hypovolemia group (n = 10) and hypervolemia group (n = 10). Hypovolemia group were exsanguinated 20% blood volume within 5 minutes, hypervolemia group: additional infusion of hydroxyethyl starch equal to 20% blood volume,and control group: no intervention. In each group, ventilator settings were changed in a randomized order by changing PEEP [0, 5, 10 and 15 cm H(2)O, PEEP0, PEEP5, PEEP10, PEEP15, 1 cm H(2)O = 0.098 kPa]. The changes in hemodynamic parameters, including heart rate (HR), mean arterial pressure (MAP), central venous pressure (CVP), cardiac index (CI), stroke volume index (SVI), systemic vascular resistance index (SVRI), intrathoracic blood volume index (ITBVI) and SVV, were monitored with a pulse-indicated continuous cardiac output (PiCCO).
Results:
In the control group, HR, CVP, SVRI and SVV were evaluated accompanying with the increasing of PEEP, but CI, SVI and ITBVI submitted decreasing tendency. The value reached peaking or valley on the level of PEEP15, and there was significance compared with PEEP0 [HR (bpm): 124 ± 18 vs. 88 ± 12, CVP (mm Hg, 1 mm Hg = 0.133 kPa): 11 ± 1 vs. 8 ± 3, SVRI [kPa×s×L(-1)×m(-2)]: 289.6 ± 81.5 vs. 215.0 ± 79.1, SVV: (23 ± 6)% vs. (11 ± 2)%, CI [L×min(-1)×m(-2)]: 3.1 ± 0.8 vs. 4.3 ± 1.4, SVI [ml×min(-1)×m(-2)]: 26 ± 7 vs. 41 ± 4, ITBVI [ml/m(2)]: 440 ± 43 vs. 491 ± 47, all P < 0.05]. There was no change in MAP. In the hypovolemia group, HR, CVP and SVV were evaluated accompanying with the increasing of PEEP, but MAP, CI, SVI and ITBVI submitted decreasing tendency. The value reached peaking or valley on the level of PEEP15, and there was significance compared with PEEP0 [HR (bpm): 146 ± 31 vs. 115 ± 27, CVP (mm Hg): 11 ± 2 vs. 5 ± 1, SVV: (28 ± 4)% vs. (20 ± 5)%, MAP(mm Hg): 90 ± 26 vs. 115 ± 19, CI [L×min(-1)×m(-2)]: 2.3 ± 0.6 vs. 3.4 ± 1.1, SVI [ml×min(-1)×m(-2)]: 20 ± 6 vs. 31 ± 9, ITBVI [ml/m(2)]: 355 ± 34 vs. 396 ± 53, all P < 0.05]. There was no change in SVRI. In the hypervolemia group, SVV submitted increasing tendency with the increasing of PEEP, but CI, SVI and ITBVI were in the tendency of decreasing, the value reached peaking or valley on the level of PEEP15, and there was significance compared with PEEP0 [SVV: (18 ± 4)% vs. (6 ± 2)%, CI [L×min(-1)×m(-2)]: 4.5 ± 0.9 vs. 5.0 ± 1.2, SVI [ml×min(-1)×m(-2)]: 37 ± 9 vs. 49 ± 7, ITBVI [ml/m(2)]: 473 ± 71 vs. 565 ± 94, all P < 0.05]. There was no change in HR, MAP, CVP and SVRI. SVV was increased in the hypovolemia group compared with control group, and decreased in the hypervolemia group. In the control group, SVV was negatively related to CI on different level of PEEP [r(PEEP0) = -0.831, r(PEEP5) = -0.790, r(PEEP10) = -0.875, r(PEEP15) = -0.560, P < 0.05 or P < 0.01].
Conclusion:
SVV was a precise indicator of cardiac preload, however high PEEP may influence hemodynamic and the accuracy of SVV.
Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:15
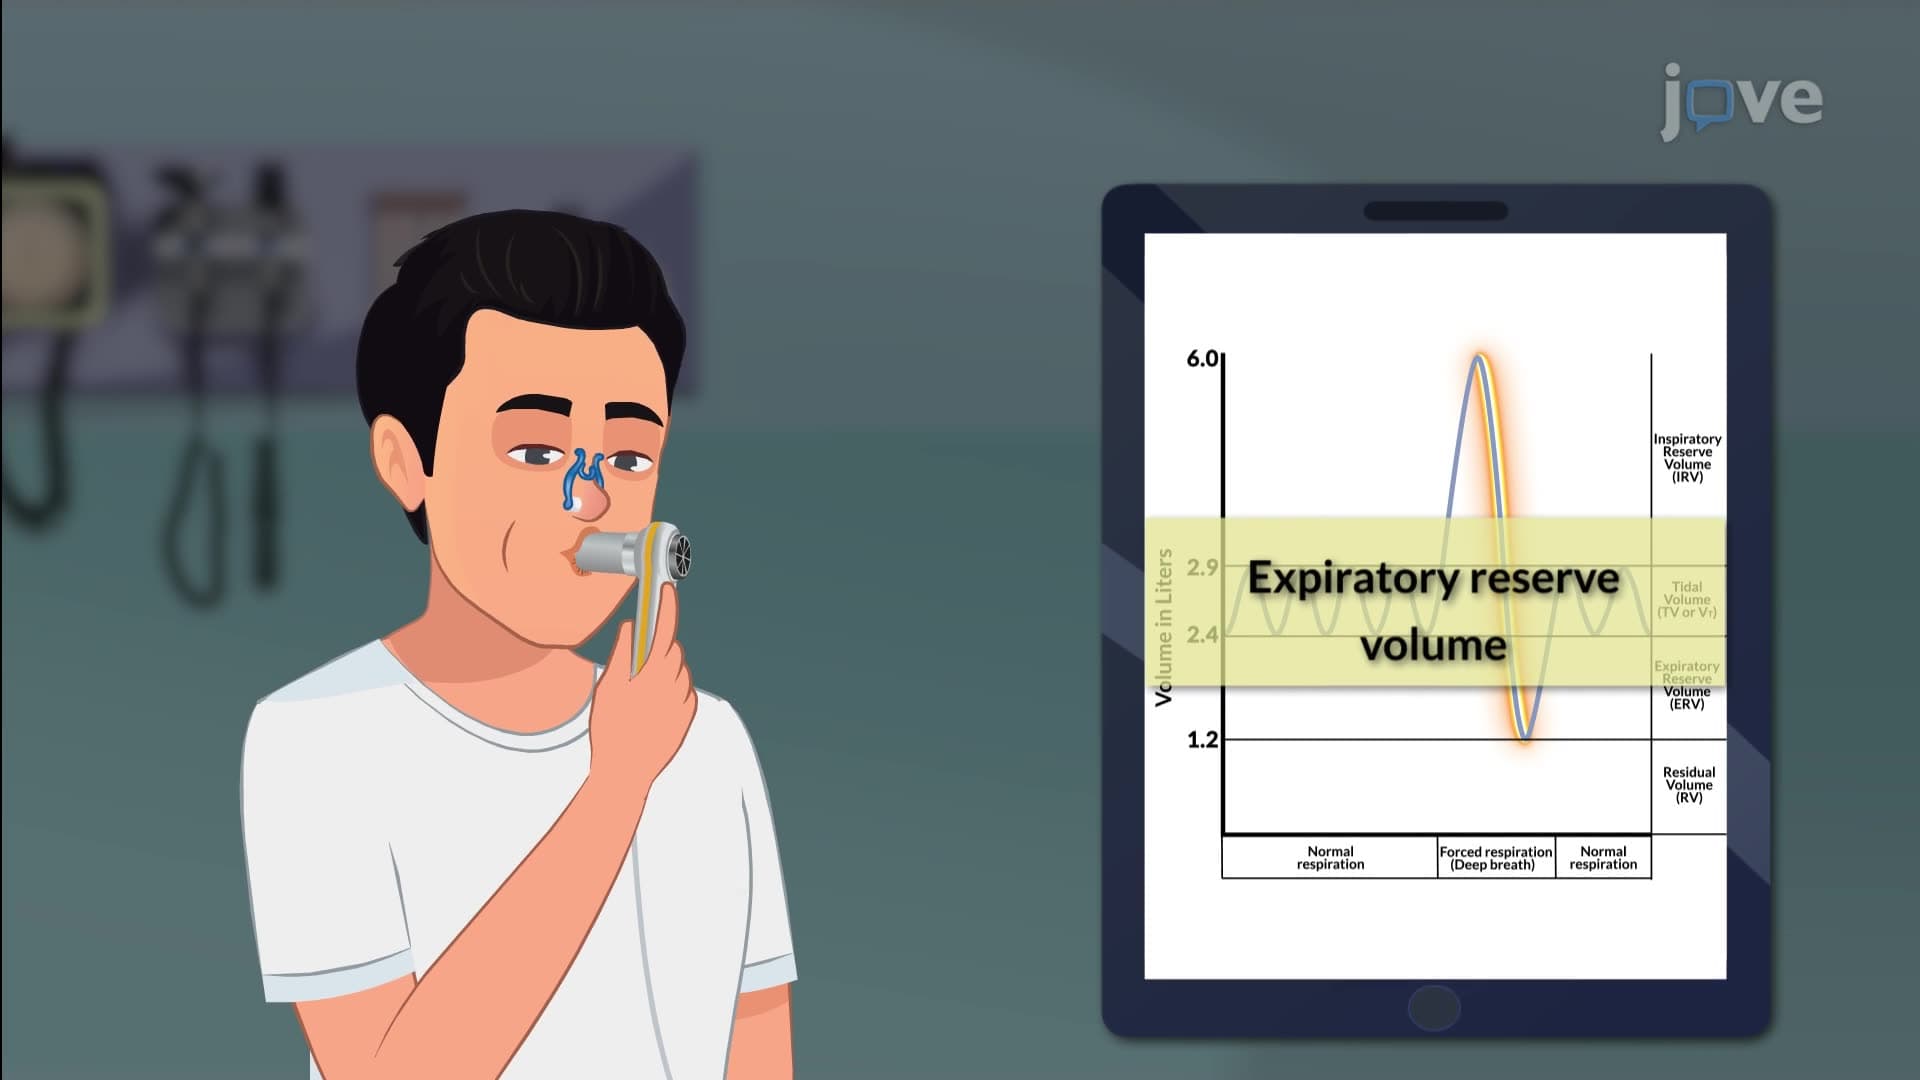
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings