Related Experiment Video
Updated: May 20, 2026

A Bioluminescent and Fluorescent Orthotopic Syngeneic Murine Model of Androgen-dependent and Castration-resistant Prostate Cancer
Published on: March 6, 2018
New considerations for ADT in advanced prostate cancer and the emerging role of GnRH antagonists
N D Shore1, P-A Abrahamsson, J Anderson
1Carolina Urologic Research Center, Myrtle Beach, SC 29572, USA. nshore@grandstrandurology.com

Abstract:
Androgen deprivation therapy (ADT) is first-line treatment for metastatic prostate cancer (PCa). Gonadotrophin-releasing hormone (GnRH) agonists are the most commonly used ADT but have several theoretical physiologic disadvantages (e.g. initial testosterone surge, potential microsurges upon repeat administration). Testosterone surge delays the intended serologic endpoint of testosterone suppression and may exacerbate clinical symptoms. GnRH antagonists were developed with a view toward overcoming these potential adverse physiologic events. This review evaluates GnRH agonists and antagonists, assessing the potential future role of antagonists in PCa and strategies to minimize ADT adverse events (AEs). Evidence was identified via PubMed search (by GnRH agent and other ADT-related terms), from review article bibliographies, and authors' therapy area knowledge, with articles included by author consensus. Degarelix shows similar efficacy to a GnRH agonist in achieving and maintaining castration, with faster onset and without testosterone surge/microsurges. Phase III data showed that, in the first treatment year, degarelix displayed a lower risk of PSA failure or death (composite endpoint), lower levels of the bone marker serum alkaline phosphatase (in baseline metastatic disease), and fewer musculoskeletal AEs than the agonist leuprolide. Also, crossing over from leuprolide to degarelix after 1 year reduced the risk of PSA failure or death. ADT displays an AE spectrum which can impact quality of life as well as causing significant morbidities. Strategies to improve ADT tolerability have become increasingly important including: a holistic management approach, improved diet and exercise, more specific monitoring to detect and prevent testosterone depletion toxicities, and intermittent ADT allowing hormonal recovery between treatment periods. Clinical studies suggest possible benefits of GnRH antagonists over agonists based on different mechanisms of action. GnRH antagonists should now be considered as an alternative first-line ADT option in advanced PCa. Intermittent ADT and a holistic treatment approach are promising strategies to improve ADT tolerability.
Related Concept Videos
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
Transducer Mechanism: Enzyme-Linked Receptors
Major types that are helpful drug targets include:
 01:17
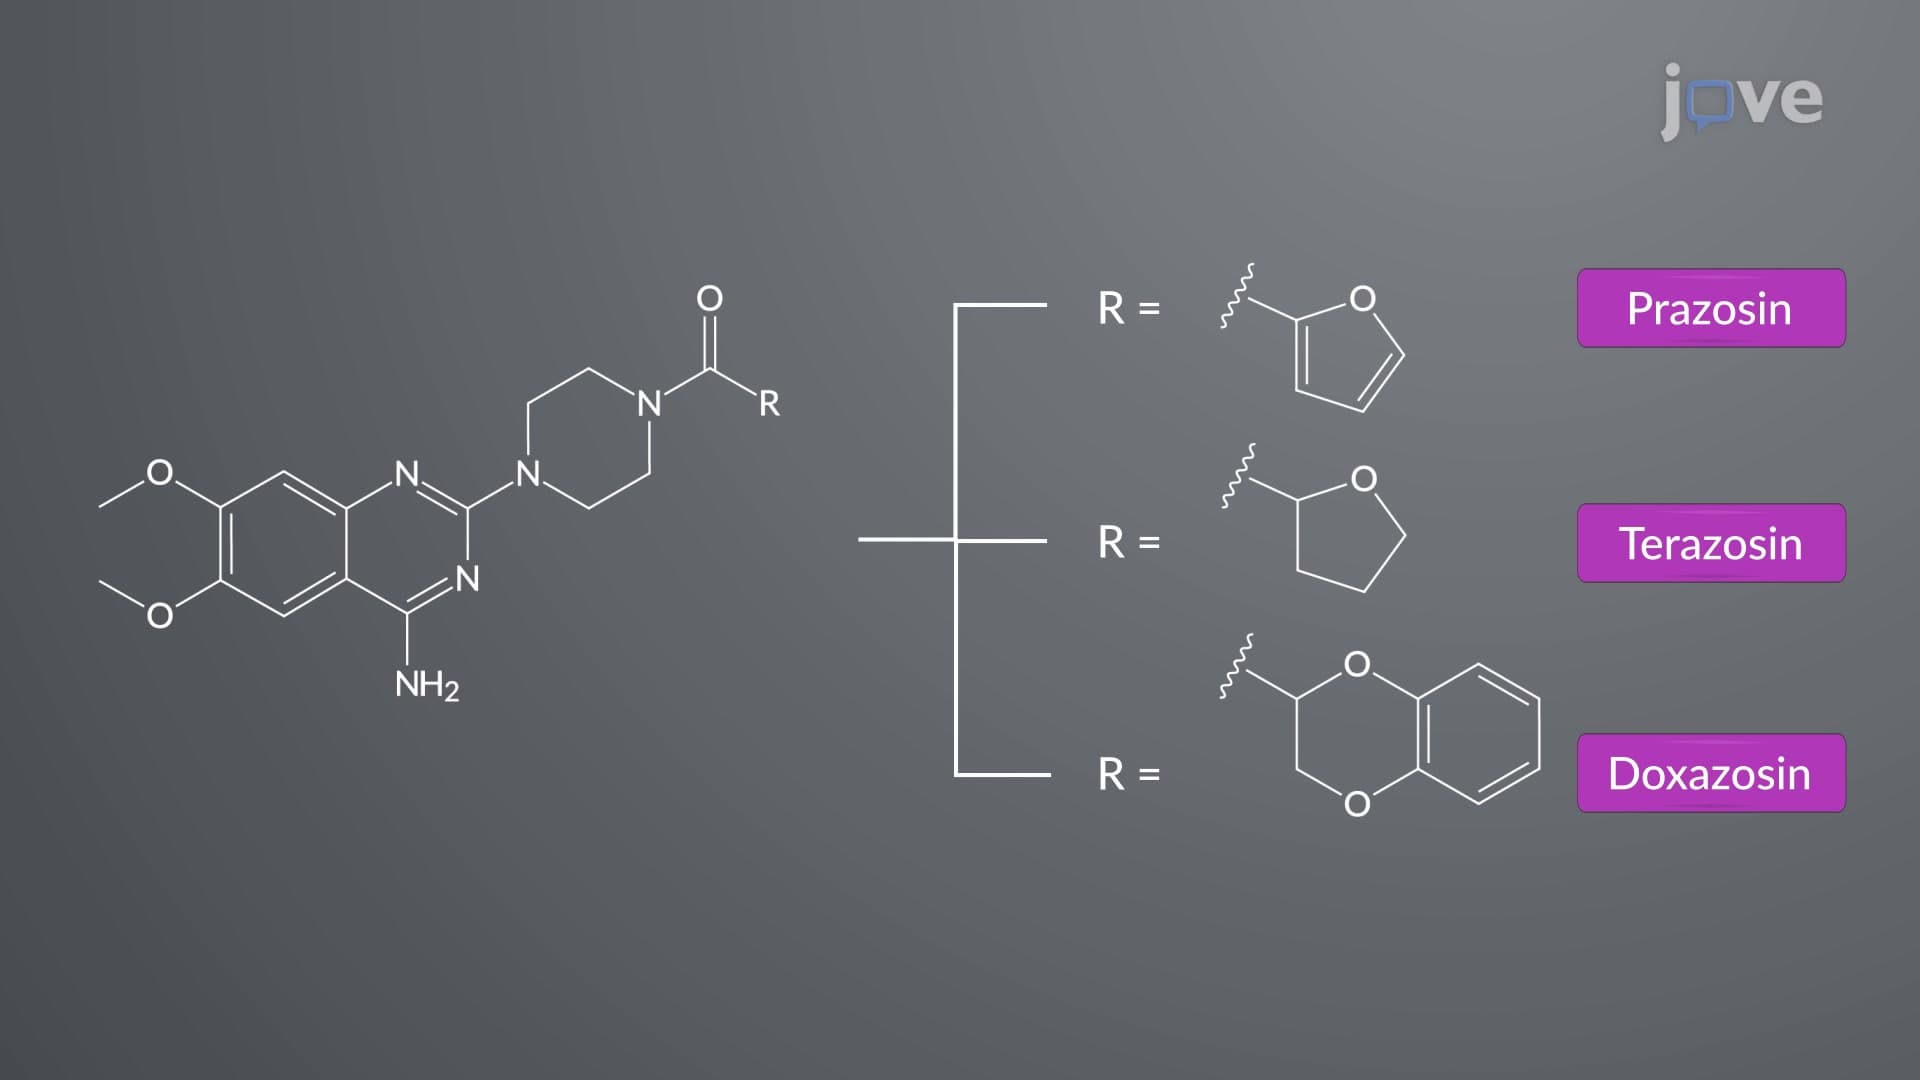
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
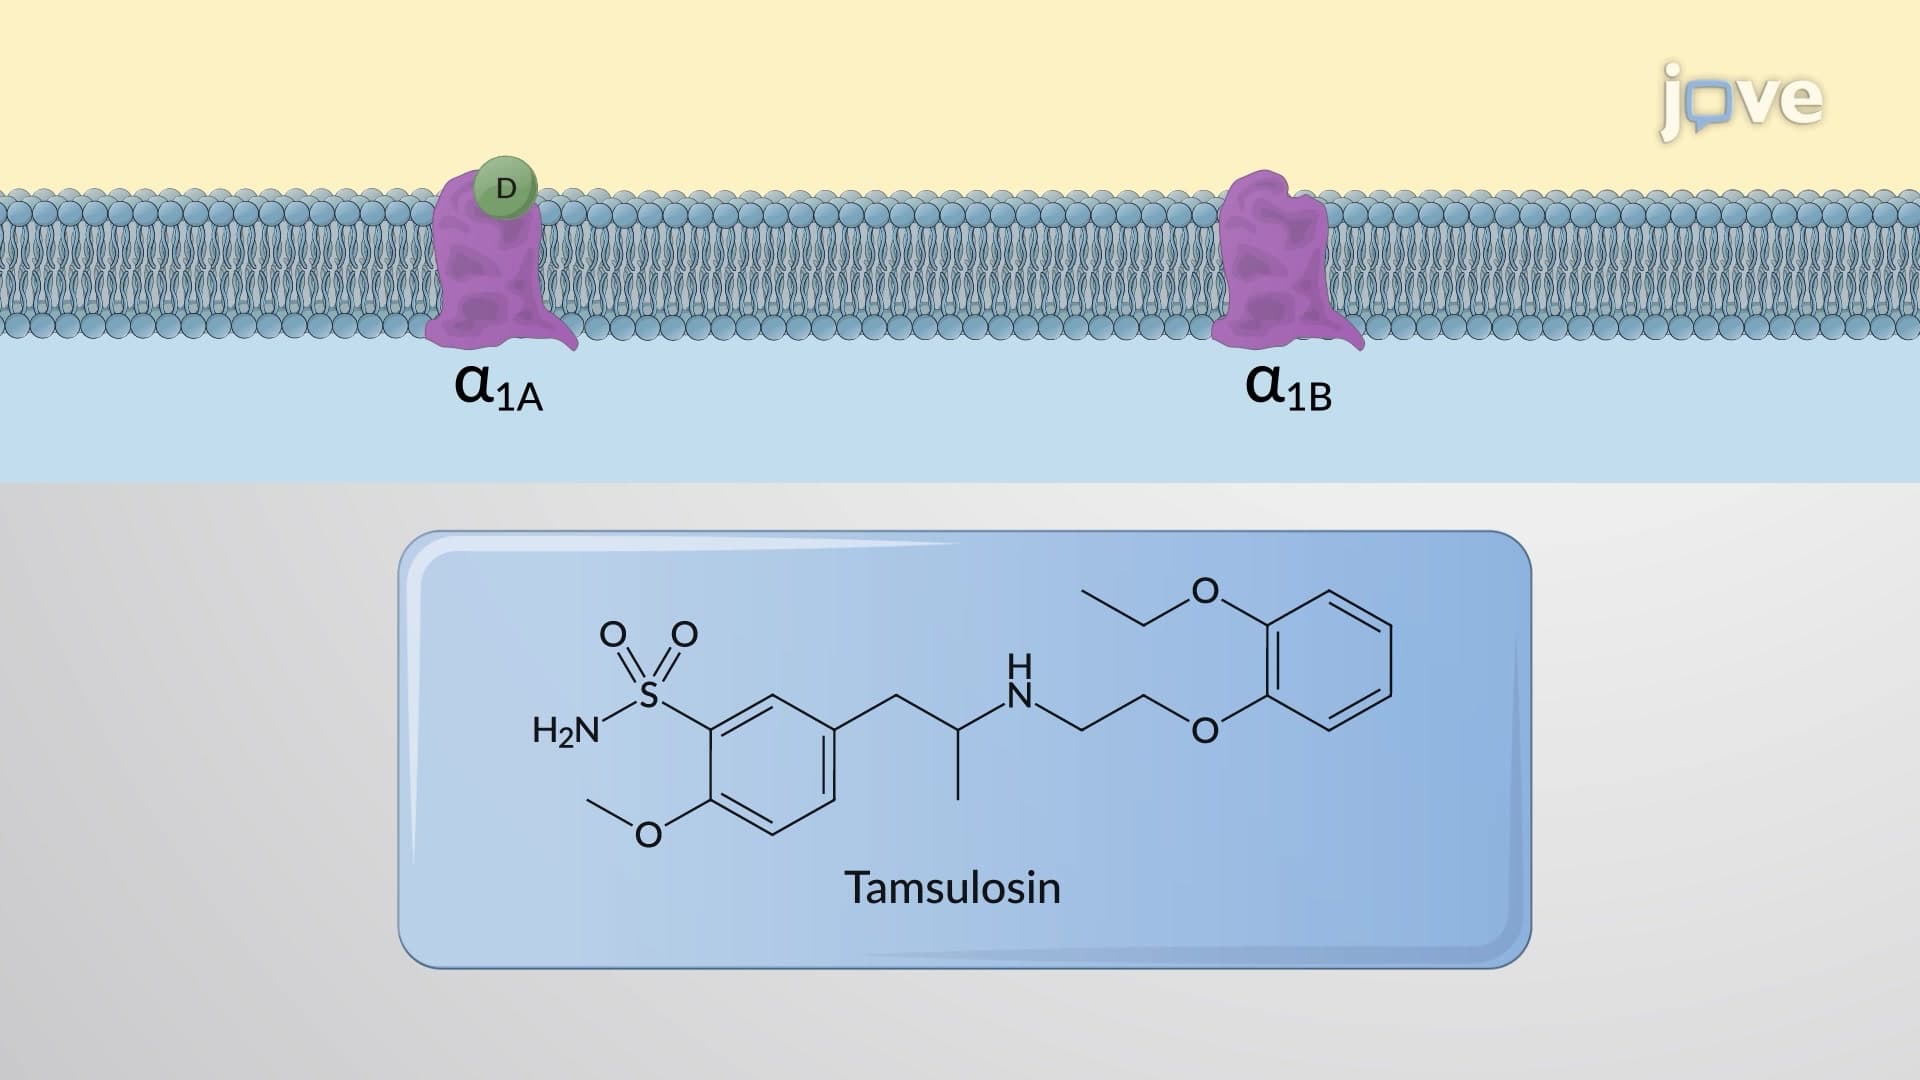 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...