Related Experiment Video
Updated: May 20, 2026
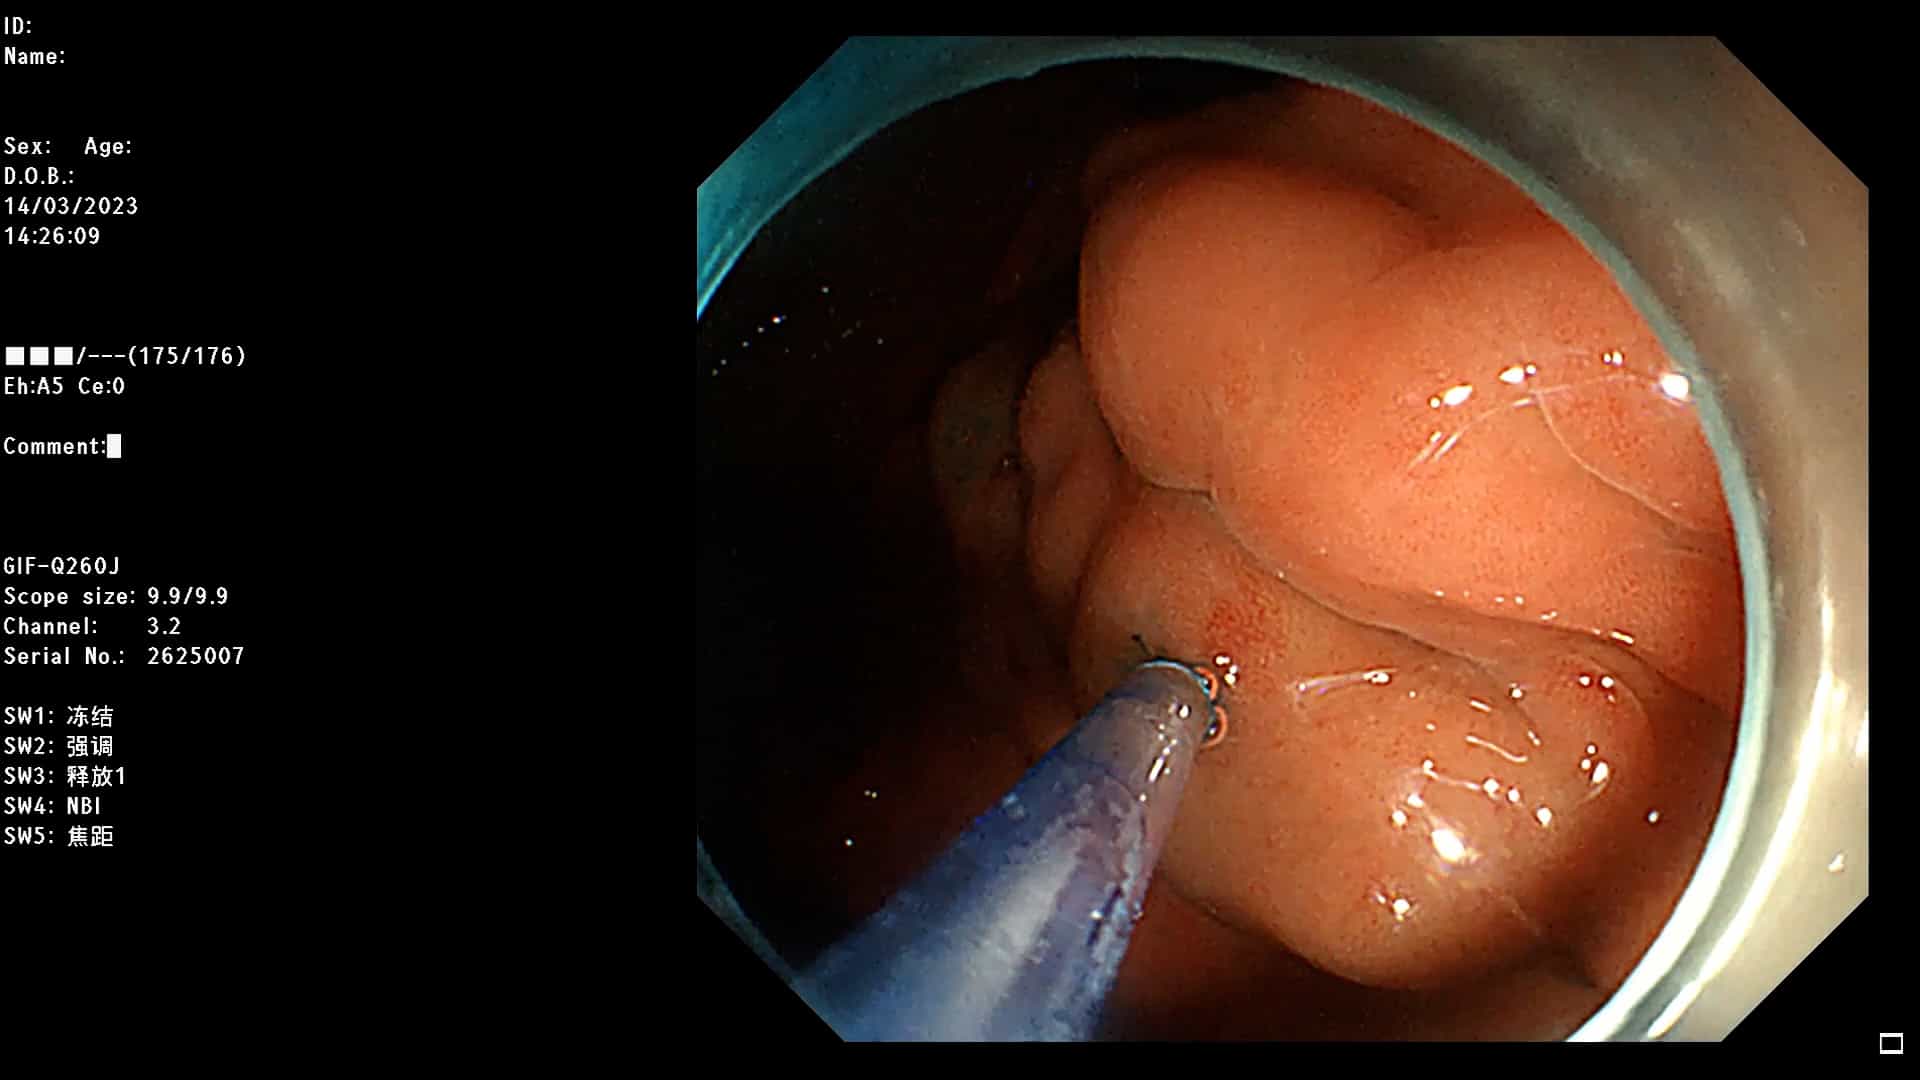
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Outcomes following acute nonvariceal upper gastrointestinal bleeding in relation to time to endoscopy: results from a
V Jairath1, B C Kahan, R F A Logan
1NHS Blood and Transplant, John Radcliffe Hospital, Oxford, UK. vipul.jairath@nhsbt.nhs.uk

Background And Study Aims:
Despite the established efficacy of therapeutic endoscopy, the optimum timeframe for performing endoscopy in patients with nonvariceal upper gastrointestinal bleeding (NVUGIB) remains unclear. The aim of the current audit study was to examine the relationship between time to endoscopy and clinical outcomes in patients presenting with NVUGIB.
Patients And Methods:
This study was a prospective national audit performed in 212 UK hospitals. Regression models examined the relationship between time to endoscopy and mortality, rebleeding, need for surgery, and length of hospital stay.
Results:
In 4478 patients, earlier endoscopy ( < 12 hours) was not associated with a lower mortality or need for surgery compared with later ( > 24 hours) endoscopy (odds ratio [OR] for mortality 0.98, 95 % confidence interval [CI] 0.88 - 1.09 for endoscopy > 24 hours vs. < 12 hours; P = 0.70). In patients receiving therapeutic endoscopy, there was a nonsignificant trend towards an increase in rebleeding associated with later endoscopy (OR 1.13, 95 %CI 0.97 - 1.32 for endoscopy > 24 hours vs. < 12 hours), with the converse seen in patients not requiring therapeutic endoscopy (OR 0.83, 95 %CI 0.73 - 0.95 for endoscopy > 24 hours vs. < 12 hours; interaction P = 0.003). Later endoscopy ( > 24 hours) was associated with an increase in risk-adjusted length of hospital stay (1.7 days longer, 95 %CI 1.39 - 1.99 vs. < 12 hours; P < 0.001).
Conclusions:
Earlier endoscopy was not associated with a reduction in mortality or need for surgery. However, it was associated with an increased efficiency of care and potentially improved control of hemorrhage in higher risk patients, supporting the routine use of early endoscopy unless specific contraindications exist. These results may help inform the debate about emergency endoscopy service provision.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:24
Esophageal Varices-I: Introduction
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications