Related Experiment Video
Updated: May 20, 2026


Echocardiographic Evaluation of Atrial Communications before Transcatheter Closure
Published on: February 8, 2022
To close or not to close an atrial septal defect in ischemic cardiomyopathy
Thomas Bartel1, Silvana Müller
1Division of Cardiology, Department of Internal Medicine III, Medical University Innsbruck, Austria. thomas.bartel@i-med.ac.at

Insights
A patient with severe heart failure and an atrial septal defect (ASD) underwent successful defect closure. Preconditioning and testing minimized risks, improving the patient's heart function.
Area of Science:
- Cardiology
- Cardiovascular Surgery
- Interventional Cardiology
Background:
- A 67-year-old male presented with significant heart failure (NYHA class III-IV) and a low left ventricular ejection fraction (21%).
- The patient had an atrial septal defect (ASD) identified as a major contributor to his heart failure.
- Closure of the ASD posed a potential risk of exacerbating the patient's already compromised clinical status.
Observation:
- Diagnostic procedures including preconditioning and echocardiographic testing were performed.
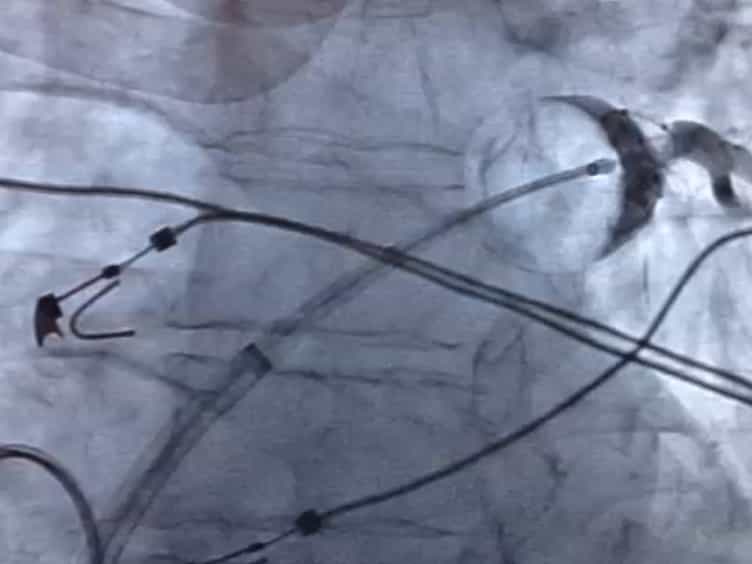
- A temporary test closure of the ASD was conducted to assess hemodynamic impact.
- These measures were implemented to mitigate risks associated with definitive ASD closure.
Findings:
- The atrial septal defect was successfully closed.
- The interventions successfully minimized the risks associated with the procedure.
- The patient's condition improved following the successful ASD closure.
Implications:
- This case highlights the successful management of complex heart failure patients with ASD.
- Preconditioning and test closure are valuable strategies for risk mitigation in ASD interventions.
- Successful ASD closure can significantly improve cardiac function and heart failure symptoms in select patients.
Abstract:
A 67-year-old male presented with a left ventricular ejection fraction of 21% and an atrial septal defect (ASD), the closure of which carries a risk of worsening the patients' clinical situation. The ASD contributed significantly to heart failure according to NYHA class III to IV, on the other hand. Preconditioning, echocardiographic testing, and test closure were carried out in order to minimize the risk and to finally close the defect successfully in behoof of the patient.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Mitral Stenosis III: Medical Management
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:25
Mitral Regurgitation III: Medical Management
 01:25
Aortic Regurgitation III: Medical Management
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy