Derivation and validation of age and temperature specific reference values and centile charts to predict lower respiratory tract infection in children with fever: prospective observational study
Related Experiment Video
Updated: May 20, 2026
Noninvasive Sampling of Mucosal Lining Fluid for the Quantification of In Vivo Upper Airway Immune-mediator Levels
Published on: August 7, 2017
R G Nijman1, M Thompson, M van Veen
1Department of General Paediatrics, Erasmus MC-Sophia Children's Hospital, 3015 GJ Rotterdam, Netherlands.

Insights
New reference values for respiratory rate in febrile children were developed using age and temperature-dependent centile charts. These charts improve the detection of lower respiratory tract infections (LRTI) compared to existing thresholds.
Area of Science:
- Pediatric Medicine
- Respiratory Physiology
- Infectious Diseases
Background:
- Accurate respiratory rate assessment is crucial for diagnosing lower respiratory tract infections (LRTI) in children.
- Existing respiratory rate thresholds lack precision in identifying LRTI in febrile children.
- Age and body temperature significantly influence respiratory rate, necessitating context-specific reference values.
Purpose of the Study:
- To establish age- and temperature-dependent reference values and centile charts for respiratory rate in children.
- To evaluate the predictive accuracy of these new reference values for identifying LRTI in febrile children.
- To compare the diagnostic performance of new thresholds against existing guidelines.
Main Methods:
- A prospective observational study involving febrile children aged 1 month to 16 years.
- Development of respiratory rate centile charts (50th, 75th, 90th, 97th) using a derivation population (n=1555).
- Validation of diagnostic performance using a separate validation population (n=671) and multivariable regression analysis.
Main Results:
- Respiratory rate increased by 2.2 breaths/min per 1°C rise, independent of age.
- The 97th centile cut-off values demonstrated higher specificity (0.94) and positive likelihood ratio (3.66) for LRTI detection.
- New centile cut-offs outperformed existing thresholds (e.g., Advanced Pediatrics Life Support) but could not differentiate between pneumonic and non-pneumonic LRTI.
Conclusions:
- Age- and temperature-dependent centile charts provide novel reference values for respiratory rate in febrile children.
- The 97th centile cut-off values are more effective in detecting the presence of LRTI than current respiratory rate thresholds.
- These findings support the use of new reference values for improved LRTI diagnosis in pediatric emergency settings.
Objectives:
To develop reference values and centile charts for respiratory rate based on age and body temperature, and to determine how well these reference values can predict the presence of lower respiratory tract infections (LRTI) in children with fever.
Design:
Prospective observational study.
Participants:
Febrile children aged at least 1 month to just under 16 years (derivation population, n = 1555; validation population, n = 671) selected from patients attending paediatric emergency departments or assessment units in hospitals.
Setting:
One hospital in the Netherlands in 2006 and 2008 (derivation population); one hospital in the Netherlands in 2003-05 and one hospital in the United Kingdom in 2005-06 (validation population).
Intervention:
We used the derivation population to produce respiratory rate centile charts, and calculated 50th, 75th, 90th, and 97th centiles of respiratory rate at a specific body temperature. Multivariable regression analysis explored associations between respiratory rate, age, and temperature; results were validated in the validation population by calculating diagnostic performance measures, z scores, and corresponding centiles of children with diagnoses of pneumonic LRTI (as confirmed by chest radiograph), non-pneumonic LRTI, and non-LRTI.
Main Outcome Measure:
Age, respiratory rate (breaths/min) and body temperature (°C), presence of LRTI.
Results:
Respiratory rate increased overall by 2.2 breaths/min per 1°C rise (standard error 0.2) after accounting for age and temperature in the model. We observed no interactions between age, temperature, and respiratory rates. Age and temperature dependent cut-off values at the 97th centile were more useful for ruling in LRTI (specificity 0.94 (95% confidence interval 0.92 to 0.96), positive likelihood ratio 3.66 (2.34 to 5.73)) than existing respiratory rate thresholds such as Advanced Pediatrics Life Support values (0.53 (0.48 to 0.57), 1.59 (1.41 to 1.80)). However, centile cut-offs could not discriminate between pneumonic LRTI and non-pneumonic LRTI.
Conclusions:
Age specific and temperature dependent centile charts describe new reference values for respiratory rate in children with fever. Cut-off values at the 97th centile were more useful in detecting the presence of LRTI than existing respiratory rate thresholds.
Related Concept Videos
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:27
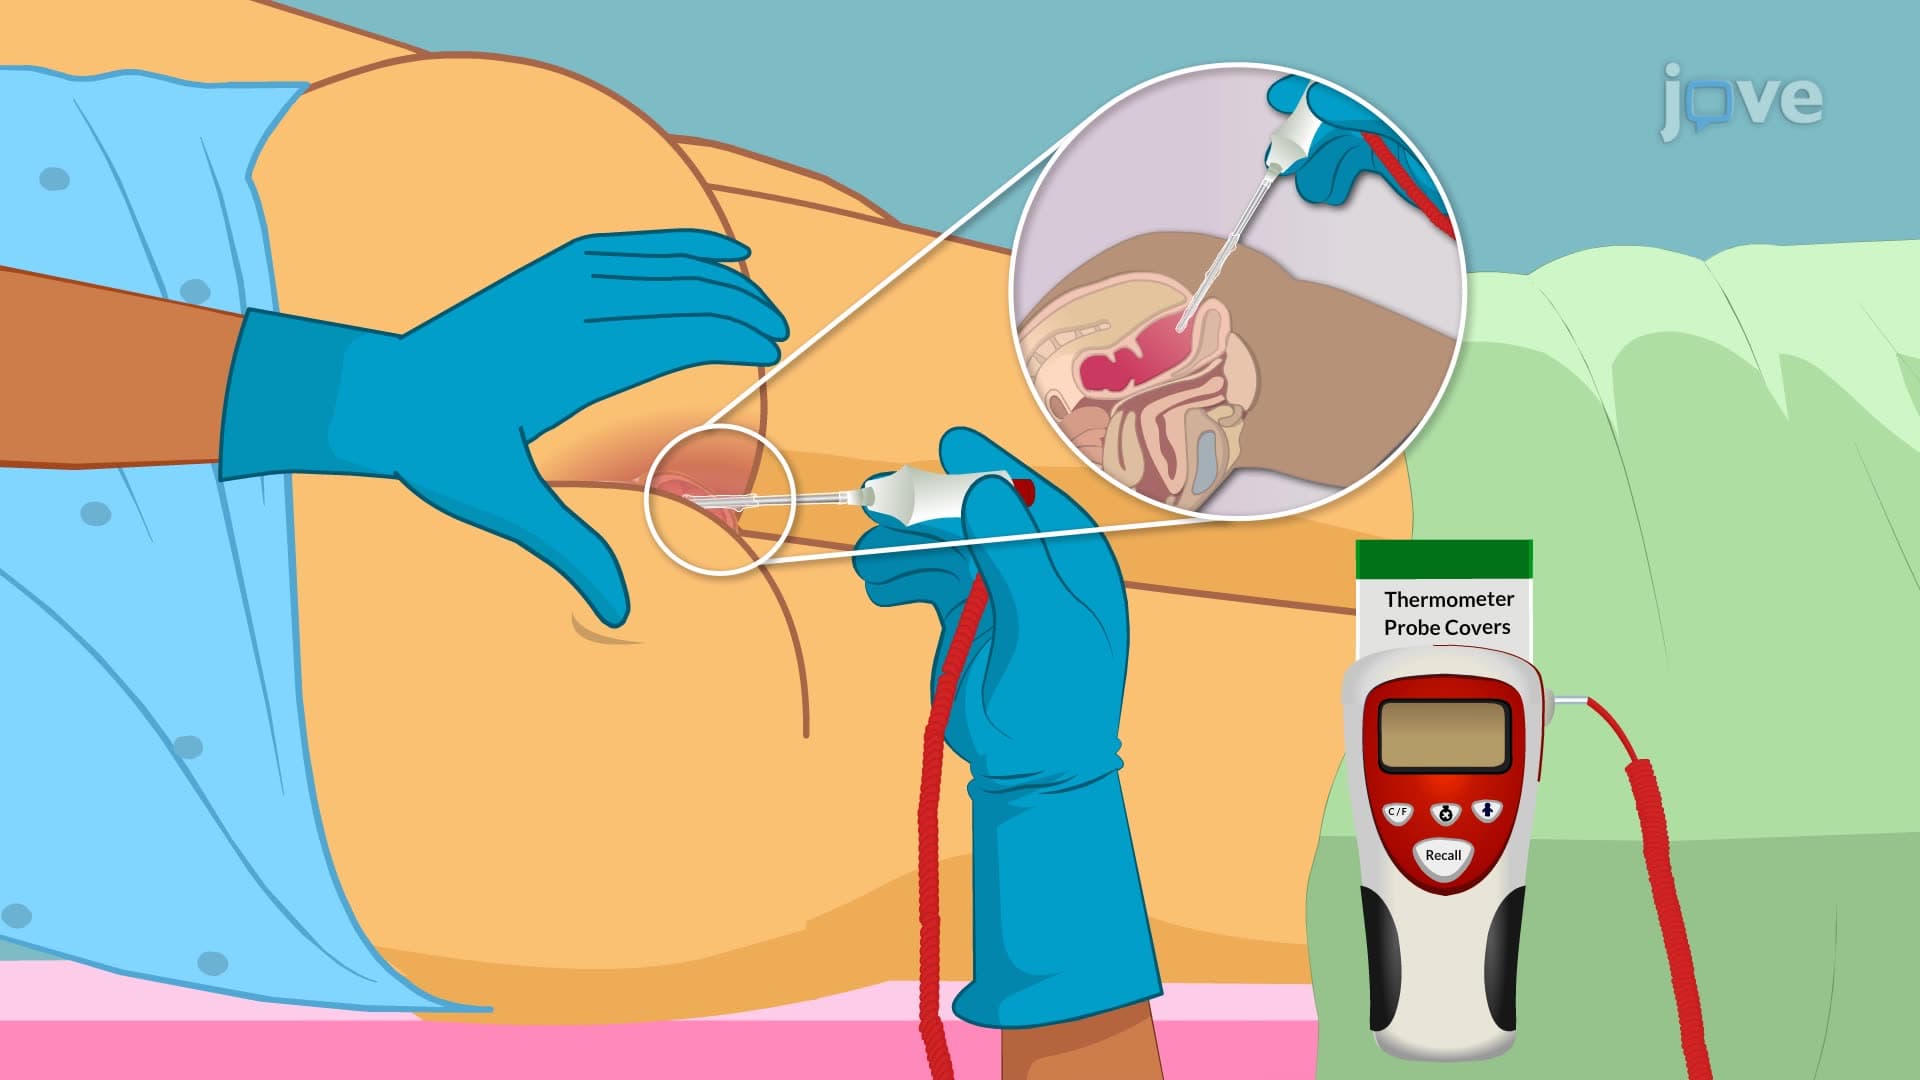
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:14
Assessing Body Temperature - Oral
Step 1:
Start by practicing proper hand hygiene to prevent the spread of microorganisms.
Step 2:
Take the thermometer out of the charging unit, switch it on, and wait for the ready sign.
Step 3:
Gently slide the probe cover until a click is heard. This simple action prevents cross-contamination and ensures the correct placement of the probe cover.
Step 4:
Instruct the patient to open their mouth and place...
 01:26
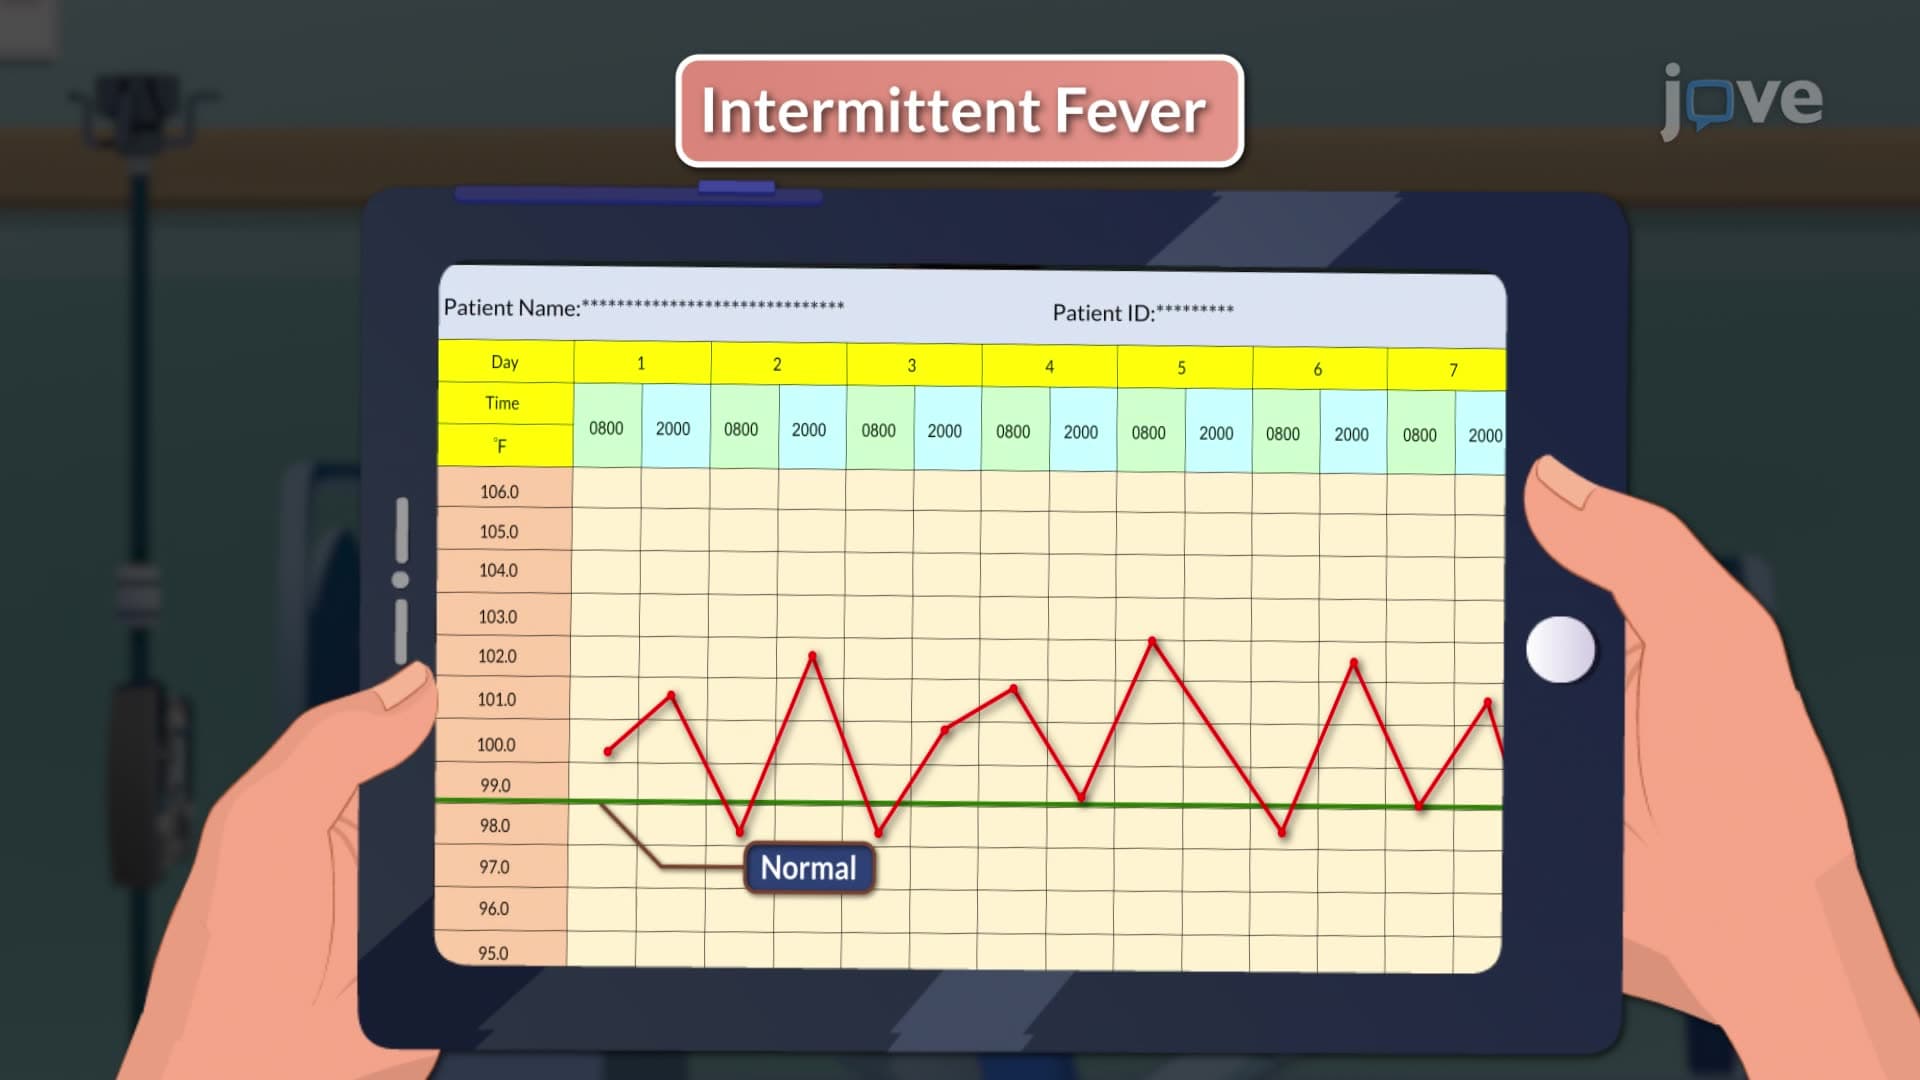
Patterns of Fever
 01:14
Assessing Body Temperature - Axilla
Step 1: Perform hand hygiene and put on clean gloves to maintain infection control and prevent cross-contamination.
Step 2: Prepare the patient by explaining the procedure to ensure understanding and cooperation. Ensure privacy, expose the axilla, and inform the patient that minimal movement is crucial for an accurate reading.
Step 3: Adjust the patient’s clothing to expose only the axilla. It minimizes...