Related Experiment Video
Updated: May 20, 2026

Hippocampal Insulin Microinjection and In vivo Microdialysis During Spatial Memory Testing
Published on: January 11, 2013
Fasting plasma insulin and the default mode network in women at risk for Alzheimer's disease
Heather Kenna1, Fumiko Hoeft, Ryan Kelley
1Stanford Center for Neurosciences in Women's Health, Department of Psychiatry and Behavioral Sciences, Stanford University, Stanford, CA 95305-5723, USA.

Abstract:
Brain imaging studies in Alzheimer's disease research have demonstrated structural and functional perturbations in the hippocampus and default mode network (DMN). Additional evidence suggests risk for pathological brain aging in association with insulin resistance (IR). This study piloted investigation of associations of IR with DMN-hippocampal functional connectivity among postmenopausal women at risk for Alzheimer's disease. Twenty middle-aged women underwent resting state functional magnetic resonance imaging. Subjects were dichotomized relative to fasting plasma insulin levels (i.e., > 8 μIU/mL [n = 10] and < 8 μIU/mL [n = 10]), and functional connectivity analysis contrasted their respective blood oxygen level-dependent signal correlation between DMN and hippocampal regions. Higher-insulin women had significantly reduced positive associations between the medial prefrontal cortex and bilateral parahippocampal regions extending to the right hippocampus, and conversely, between the left and right hippocampus and medial prefrontal cortex. Neuropsychological data (all within normal ranges) also showed significant differences with respect to executive functioning and global intelligence. The results provide further evidence of deleterious effects of IR on the hippocampus and cognition. Further imaging studies of the IR-related perturbations in DMN-hippocampal functional connectivity are needed.


Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:15
Hypoglycemia and Glucagon
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:29
Hyperglycemia
 01:23
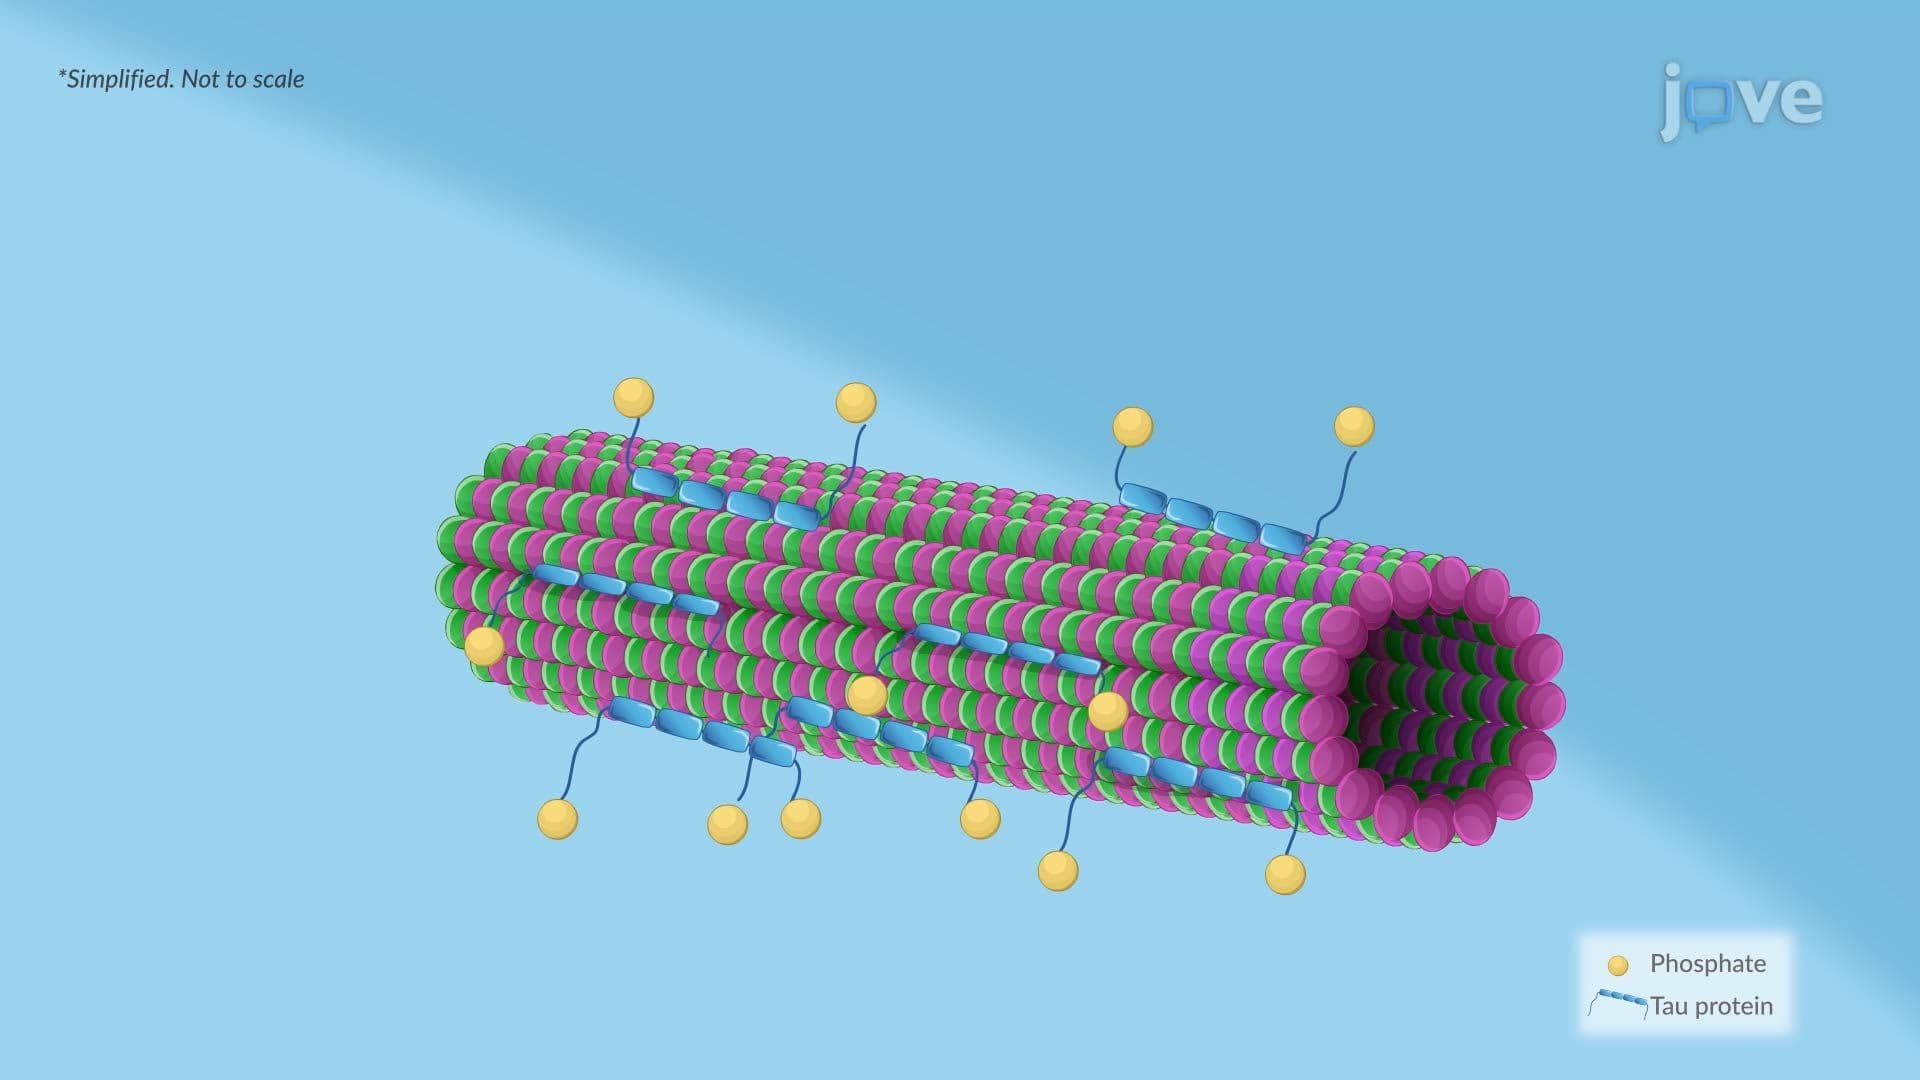
Alzheimer Disease ll: Pathophysiology
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...