Related Experiment Video
Updated: May 20, 2026


Assessment of Ex Vivo Murine Biventricular Function in a Langendorff Model
Published on: December 23, 2022
[Study on the changes of cardiac reserve function during normal vaginal delivery]
Yan-wei Lin1, Yong Shao, Jian-hua Zhang
1Department of Obstetrics and Gynecology, Chongqing Medical University, Chongqing, China.

Objective:
To investigate the trend of cardiac reserve function during the normal labor.
Methods:
Sixty-three cases were chosen randomly from hospitalized maternal women in the First Affiliated Hospital of Chongqing Medical University from 2010 June to December (six months). The digital technique of heart sound signal processing was used to analyze cardiac reserve function parameters including the heart rate (HR), the ratio of the amplitude of the first heart sound to the second heart sound (S1/S2) and the ratio of diastolic to systolic duration (D/S) of pregnant women.
Results:
(1) Comparisons of cardiac reserve function between uterine contractions and relaxations during labor: 1) Latent phase of labor (cervix dilation < 3 cm):HR was (87.3 ± 14.0) beats/min in uterine contractions and (82.8 ± 12.5) beats/min in uterine relaxations, the ratio of D/S was 1.14 ± 0.27 in uterine contractions and 1.21 ± 0.22 in uterine relaxations, the comparisons of the above two were statistically significant, P < 0.05; But the ratio of S1/S2 was 2.19 ± 0.82 in uterine contractions and 2.28 ± 0.81 in uterine relaxations, the comparison was not statistically significant, P > 0.05. 2) During early active stage of labor (cervix dilation 3 - 6 cm):HR was (89.3 ± 15.4) beats/min in uterine contractions and (83.1 ± 13.5) beats/min in uterine relaxations, the ratio of D/S was 1.09 ± 0.30 in uterine contractions and 1.20 ± 0.27 in uterine relaxations, the comparisons of the above two were statistically significant, (P < 0.05); But the ratio of S1/S2 was 2.42 ± 1.08 in uterine contractions and 2.29 ± 0.83 in uterine relaxations, the comparison was not statistically significant (P > 0.05); 3) During late active stage of labor (cervix dilation 6 - 10 cm), HR was (95.4 ± 18.7) beats/min in uterine contractions and (86.2 ± 15.6) beats/min in uterine relaxations, the ratio of D/S was 1.01 ± 0.25 in uterine contractions and 1.18 ± 0.25 in uterine relaxations, the comparisons of the above two were statistically significant, (P < 0.05); But the ratio of S1/S2 was 2.61 ± 1.26 in uterine contractions and 2.67 ± 1.19 in uterine relaxations, the comparison was not statistically significant (P > 0.05). 4) The second stage of labor (cervical dilation ≥ 10 cm):HR was (109.4 ± 19.7) beats/min in uterine contractions and (93.5 ± 16.7) beats/min in uterine relaxations, the ratio of D/S was 0.89 ± 0.23 in uterine contractions and 1.14 ± 0.26 in uterine relaxations, the ratio of S1/S2 was 3.66 ± 1.37 in uterine contractions and (2.81 ± 1.07) in uterine relaxations, the comparisons of all were statistically significant (P < 0.05). (2) Comparison of cardiac reserve function in uterine relaxations of each stage of labor: 1) Maternal heart rate gradually increased from latent stage of labor to the second stage of labor, and decreased postpartum, the comparison was statistically significant (P < 0.05); 2) The ratio of S1/S2 of maternal gradually increased from latent stage of labor to the second stage of labor, and decreased postpartum, the comparison was statistically significant (P < 0.05); 3) The ratio of D/S gradually decreased from latency to the second stage of labor, and increased postpartum, the comparison was statistically significant (P < 0.05). (3) Comparison of cardiac reserve function in uterine contractions of each stage of labor: 1) Maternal heart rate gradually decreased from latent stage of labor to the second stage of labor, the comparison was statistically significant (P < 0.05); 2) The ratio of S1/S2 of maternal gradually increased from latent stage of labor to the second stage of labor, the comparison was statistically significant (P < 0.05); 3) The ratio of D/S gradually decreased from latency to the second stage of labor, the comparison was statistically significant (P < 0.05).
Conclusions:
The maternal cardiac reserve function decreased in uterine contractions than relaxation during labor; With the progress of labor, the maternal cardiac reserve function declined, especially in the second stage of labor, and recovered in postpartum stage.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
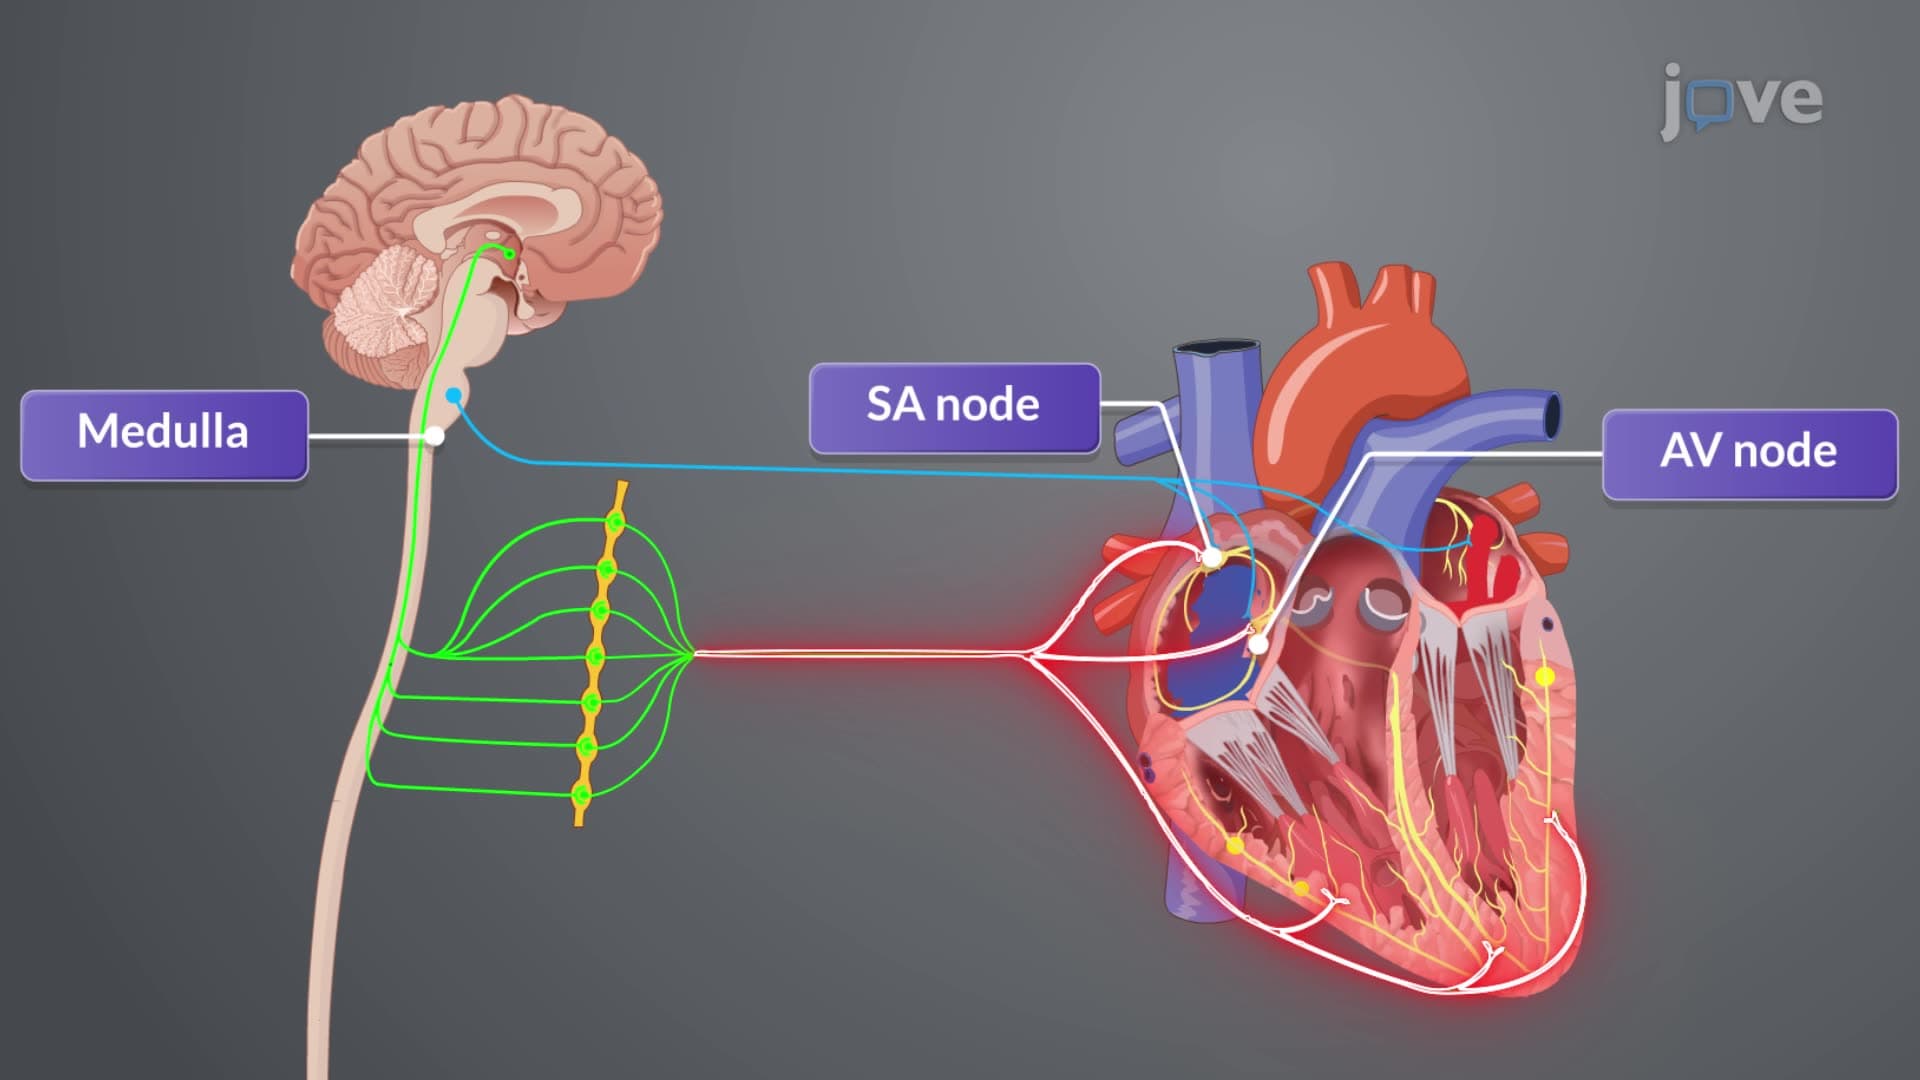
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...