Related Experiment Video
Updated: May 20, 2026
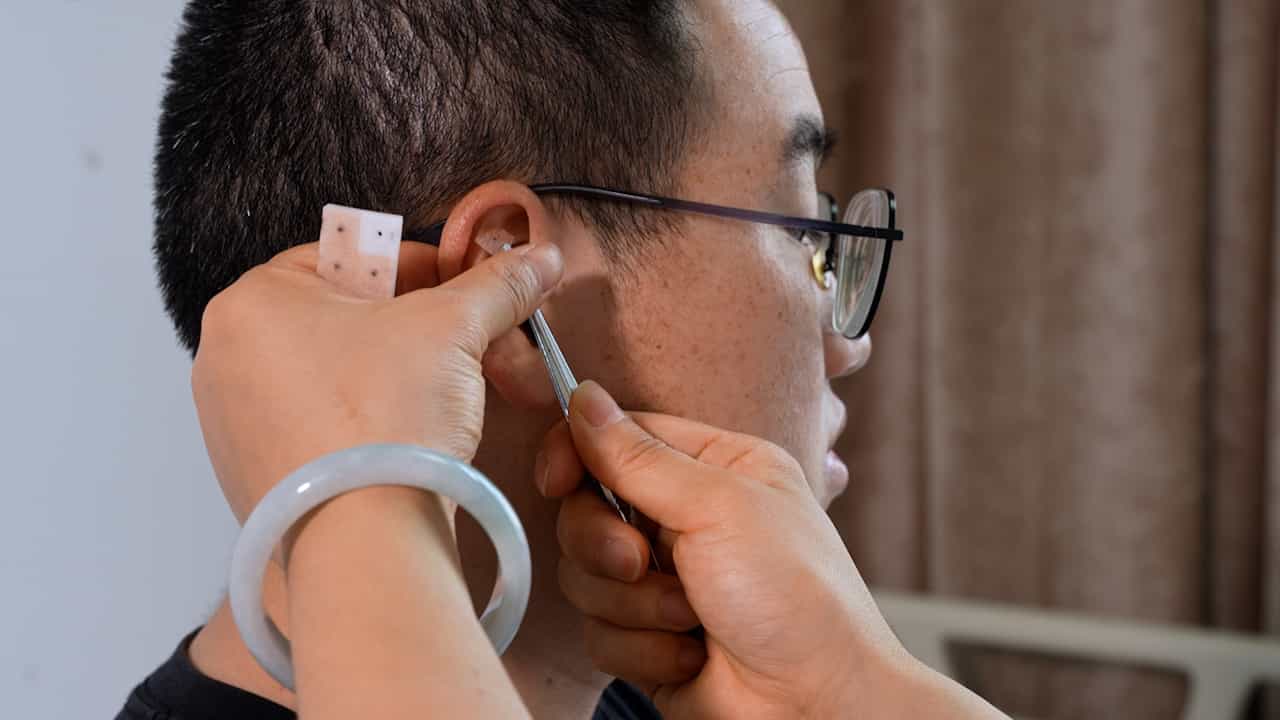

Auricular Acupressure as an Adjuvant Treatment for Wheezing in Stable Chronic Obstructive Pulmonary Disease
Published on: May 10, 2024
Chapter 11: the infant and toddler with wheezing

Insights
Recurrent wheezing in young children can be transient or persistent. While some infants outgrow wheezing, others may develop long-term respiratory issues, highlighting the need for early identification and management.
Area of Science:
- Pediatrics
- Pulmonology
- Immunology
Background:
- Recurrent wheezing affects a significant portion of young children, often triggered by viral infections or bacterial colonization.
- Wheezing phenotypes in early childhood include transient early wheezers, nonatopic wheezers, and atopic wheezers, each with distinct clinical trajectories.
- Understanding these phenotypes is crucial for predicting long-term respiratory health and guiding interventions.
Purpose of the Study:
- To characterize the different phenotypes of recurrent wheezing in infants and toddlers.
- To investigate the association between wheezing phenotypes, lung function, and bronchial hyperreactivity.
- To explore the long-term outcomes of early childhood wheezing.
Main Methods:
- Classification of wheezing phenotypes based on age of onset, duration, and associated factors.
- Assessment of lung function in children with different wheezing phenotypes.
- Evaluation of bronchial hyperreactivity using methacholine challenge tests.
Main Results:
- Transient early wheezers (60%) show reduced lung function by age 6, despite symptom resolution.
- "Nonatopic wheezers" (20%) have persistent but less frequent symptoms and slightly reduced lung function without bronchial hyperreactivity.
- "Atopic wheezers" (20%) present with normal infancy lung function but develop reduced lung function and bronchial hyperreactivity by age 6.
Conclusions:
- Early childhood wheezing is heterogeneous, with distinct phenotypes having different prognoses.
- Atopic wheezing is associated with the development of reduced lung function and bronchial hyperreactivity.
- Long-term respiratory health in children with recurrent wheezing depends on the underlying phenotype.
Abstract:
Recurrent wheezing is common in young infants and toddlers with 27% of all children having at least one wheezing episode by the age of 9 years. The initial wheezing episodes in young children often are linked to respiratory infections due to viral pathogens such as respiratory syncytial virus, rhinovirus, human metapneumovirus, and influenza virus. Bacterial colonization of the neonatal airway also may be significant in the late development of recurrent wheeze and asthma. Some 60% of children who wheeze in the first 3 years of life will have resolution of wheezing by age 6 years ("transient early wheezers"). Children who are "transient early wheezers" have reduced lung function, which remains low at age 6 years, although wheezing has ceased when compared with children who have never wheezed. In contrast, "nonatopic wheezers" represent 20% of wheezing toddlers <3 years of age. These children have more frequent symptoms during the 1st year of life and may continue to wheeze through childhood, but, typically, episodes become less frequent by early adolescence. Lung function in "nonatopic wheezers" is slightly lower than in control subjects from birth to 11 years of age, but they do not have bronchial hyperreactivity on methacholine challenge. The third phenotype refers to "atopic wheezing" or wheezing associated with IgE sensitization. This phenotype accounts for the last 20% of wheezing children <3 years of age. These "atopic wheezers" have normal lung function in infancy; however, lung function is reduced by age 6 years and bronchial hyperreactivity typically is observed.
Related Concept Videos
 01:28
Asthma I: Introduction
 01:17
Pulmonary Cycle: Exhalation
 01:29
Asthma-I: Introduction
 01:13
Asthma III: Clinical Manifestations
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma