Related Experiment Video
Updated: May 20, 2026

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Pelvic morphology differs in rotation and obliquity between developmental dysplasia of the hip and retroversion
Moritz Tannast1, Peter Pfannebecker, Joseph M Schwab
1Department of Orthopaedic Surgery, Murtenstrasse, Inselspital, University of Bern, 3010 Bern, Switzerland. moritz.tannast@insel.ch

Background:
Developmental dysplasia of the hip (DDH) and acetabular retroversion represent distinct acetabular pathomorphologies. Both are associated with alterations in pelvic morphology. In cases where direct radiographic assessment of the acetabulum is difficult or impossible or in mixed cases of DDH and retroversion, additional indirect pelvimetric parameters would help identify the major underlying structural abnormality.
Questions/Purposes:
We asked: How does DDH and retroversion differ with respect to rotation and coronal obliquity as measured by the pelvic width index, anterior inferior iliac spine (AIIS) sign, ilioischial angle, and obturator index? And what is the predictive value of each variable in detecting acetabular retroversion?
Methods:
We reviewed AP pelvis radiographs for 51 dysplastic and 51 retroverted hips. Dysplasia was diagnosed based on a lateral center-edge angle of less than 20° and an acetabular index of greater than 14°. Retroversion was diagnosed based on a lateral center-edge angle of greater than 25° and concomitant presence of the crossover/ischial spine/posterior wall signs. We calculated sensitivity, specificity, and area under the receiver operating characteristic (ROC) curve for each variable used to diagnose acetabular retroversion.
Results:
We found a lower pelvic width index, higher prevalence of the AIIS sign, higher ilioischial angle, and lower obturator index in acetabular retroversion. The entire innominate bone is internally rotated in DDH and externally rotated in retroversion. The areas under the ROC curve were 0.969 (pelvic width index), 0.776 (AIIS sign), 0.971 (ilioischial angle), and 0.925 (obturator index).
Conclusions:
Pelvic morphology is associated with acetabular pathomorphology. Our measurements, except the AIIS sign, are indirect indicators of acetabular retroversion. The data suggest they can be used when the acetabular rim is not clearly visible and retroversion is not obvious.
Level Of Evidence:
Level III, diagnostic study. See Guidelines for Authors for a complete description of levels of evidence.

Related Concept Videos
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four quadrants...
 01:16
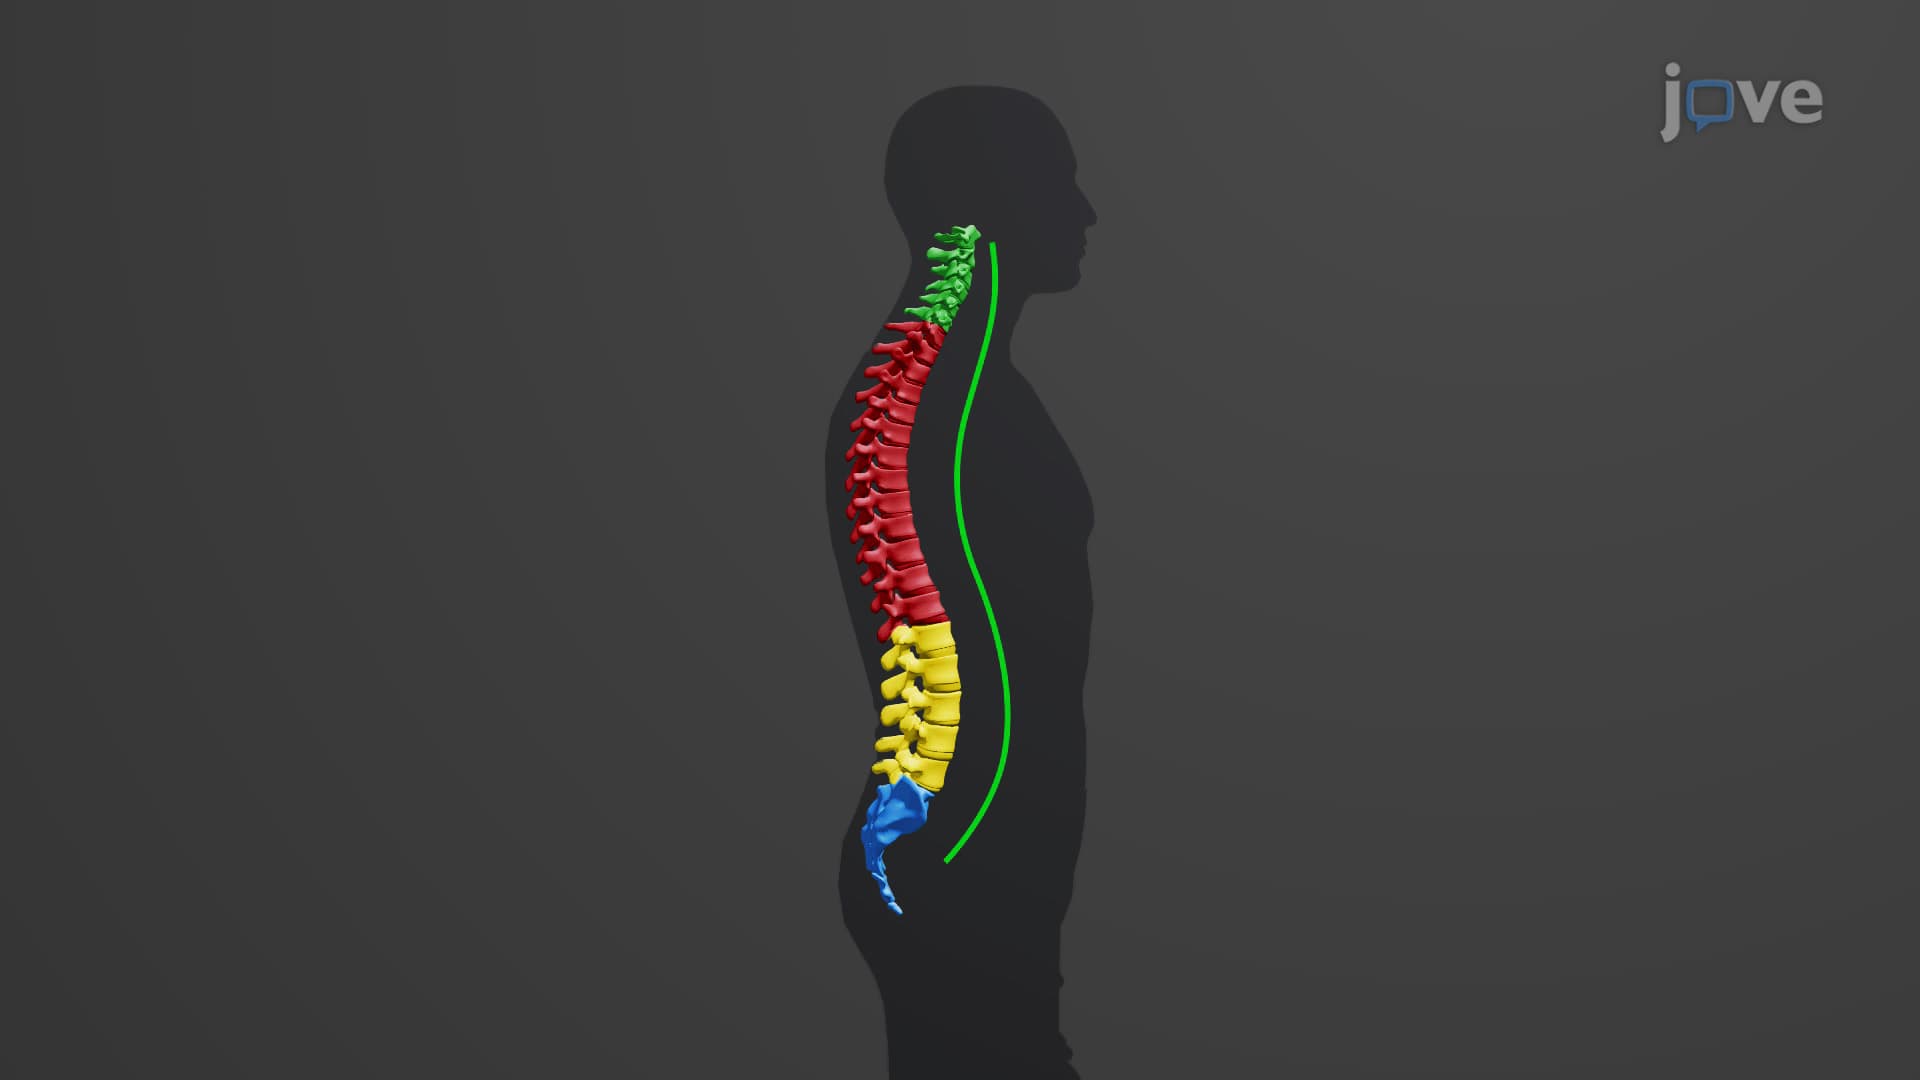
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
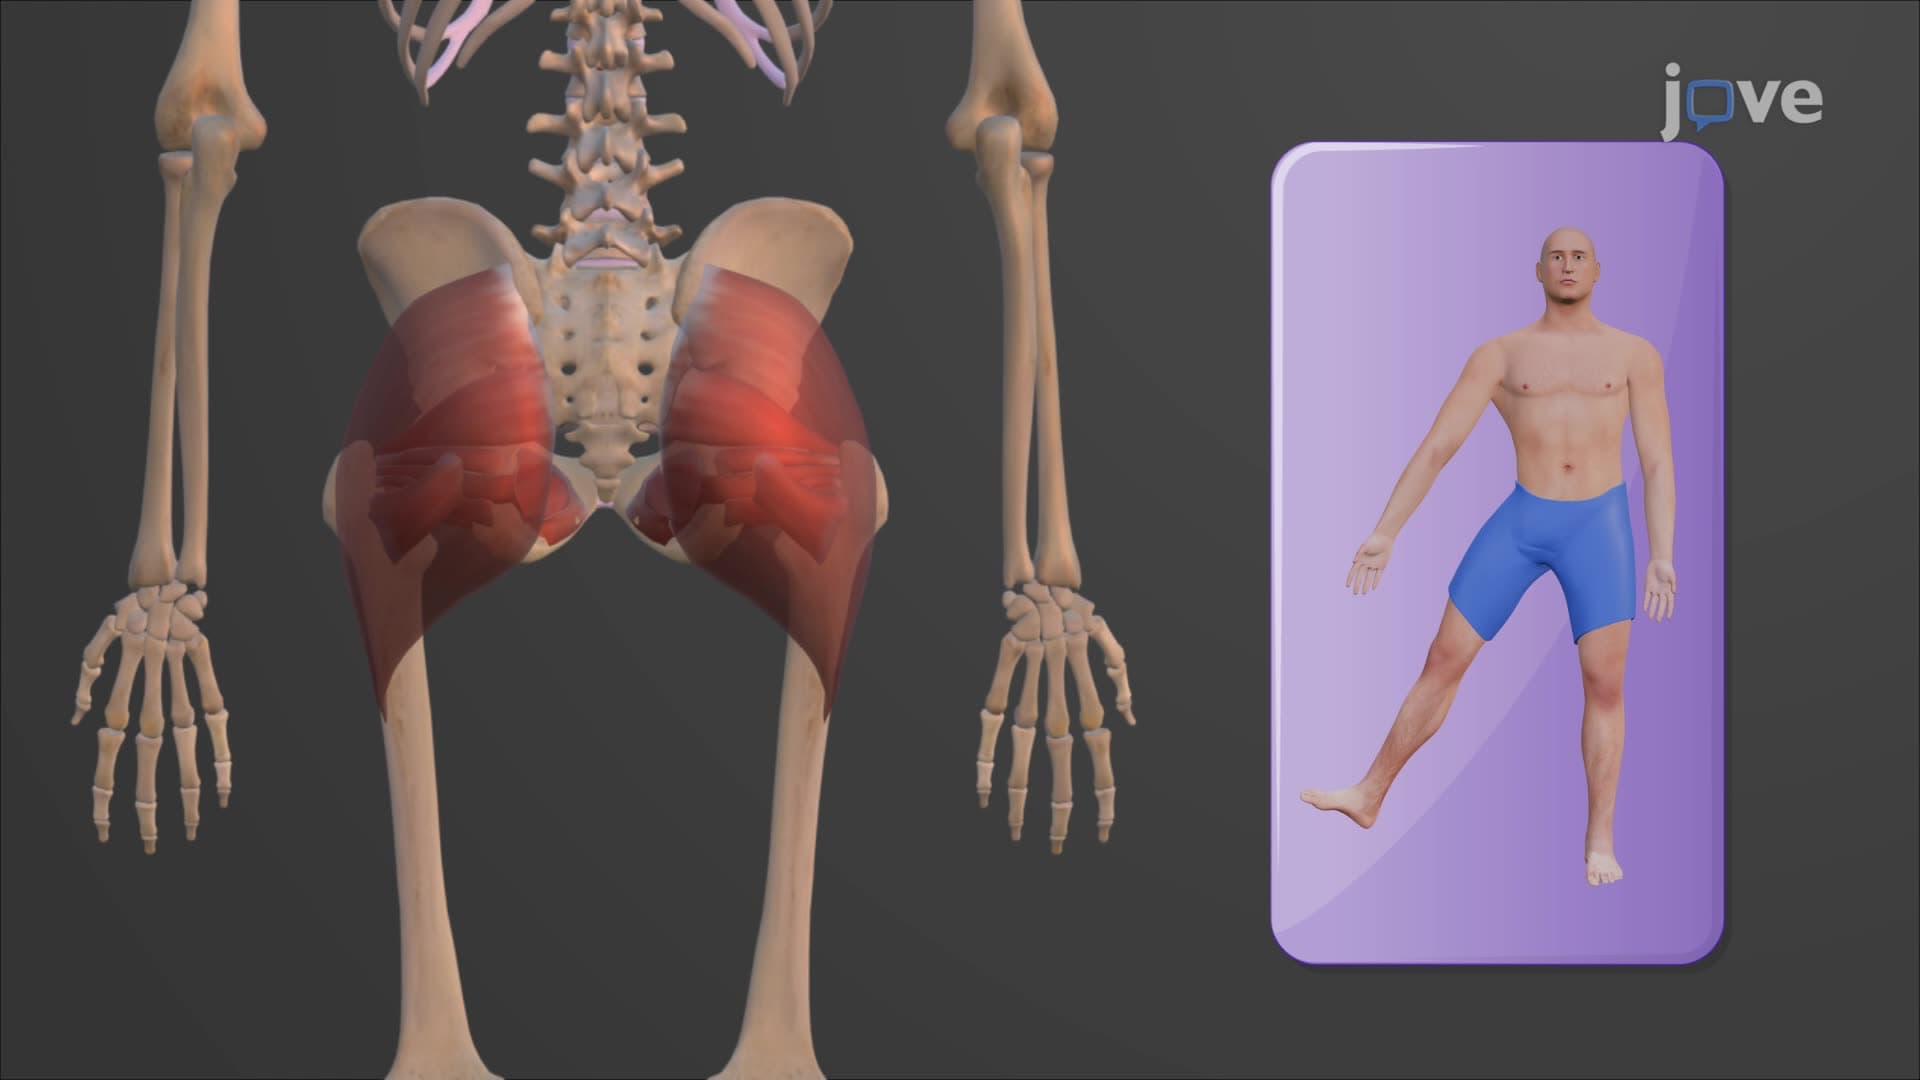 01:20
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar fascia...
 01:16
Bones of the Lower Limb: Femur and Patella