Related Experiment Videos
Concomitant use of beta-1 adrenoreceptor blocker and norepinephrine in patients with septic shock
Martin Balik1, Jan Rulisek, Pavel Leden
1Department of Anaesthesiology and Intensive Care, First Faculty of Medicine, Charles University in Prague and General University Hospital in Prague, U Nemocnice 2, Prague 2, 120 00, Prague, Czech Republic. martin.balik@post.cz

Background:
Betablockade has been shown to have cardioprotective effects in patients under perioperative stress. Besides animal model of septic shock and a small cohort of septic patients, these benefits have not been studied in septic shock patients who require norepinephrine administration.
Methods:
After correction of preload, an esmolol bolus (0.2-0.5 mg/kg) followed by continuous 24 h infusion was administered in septic patients with sinus or supraventricular tachycardia (HR > 120/min). Exclusion criteria were severe LV systolic dysfunction, atrioventricular blockade and norepinephrine infusion at rates over 0.5 mg/kg/min. Monitoring with echocardiography and pulmonary artery catheter before, at 2, 6, 12, 24 h following the start and 6 h after ceasing of the esmolol drip. Patients were maintained normovolemic throughout the study and adjustments of concomitant norepinephrine infusion rates were made as required.
Results:
Ten septic patients (mean age 54.4 ± 18.7), APACHE II 21.5 ± 6.2, CRP 275 ± 78 mg/l, procalcitonin 14.5 ± 10.1 mg/l, were given esmolol drip of 212.5 ± 63.5 mg/h at start to 272.5 ± 89.5 mg/h at 24 h. Heart rate decreased from mean 142 ± 11/min to 112 ± 9/min (p < 0.001) with parallel insignificant reduction of cardiac index (4.94 ± 0.76 to 4.35 ± 0.72 l/min/m(2)). Stroke volume insignificantly increased from 67.1 ± 16.3 ml to 72.9 ± 15.3 ml. No parallel change of pulmonary artery wedge pressure was observed (15.9 ± 3.2 to 15.0 ± 2.4 mmHg) as well as no significant changes of norepinephrine infusion (0.13 ± 0.17 to 0.17 ± 0.19 mg/kg/min), DO(2), VO(2), OER or arterial lactate.
Conclusions:
Saving the heart 30 beats/min did not demonstrate adverse impact on global haemodynamics in rates above 110/min. Using well titratable betablocker seems to be safe and cardioprotective in septic shock patients with high cardiac output.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:22
Heart Failure Drugs: β-Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:21
Drugs Affecting Neurotransmitter Release or Uptake
 01:26
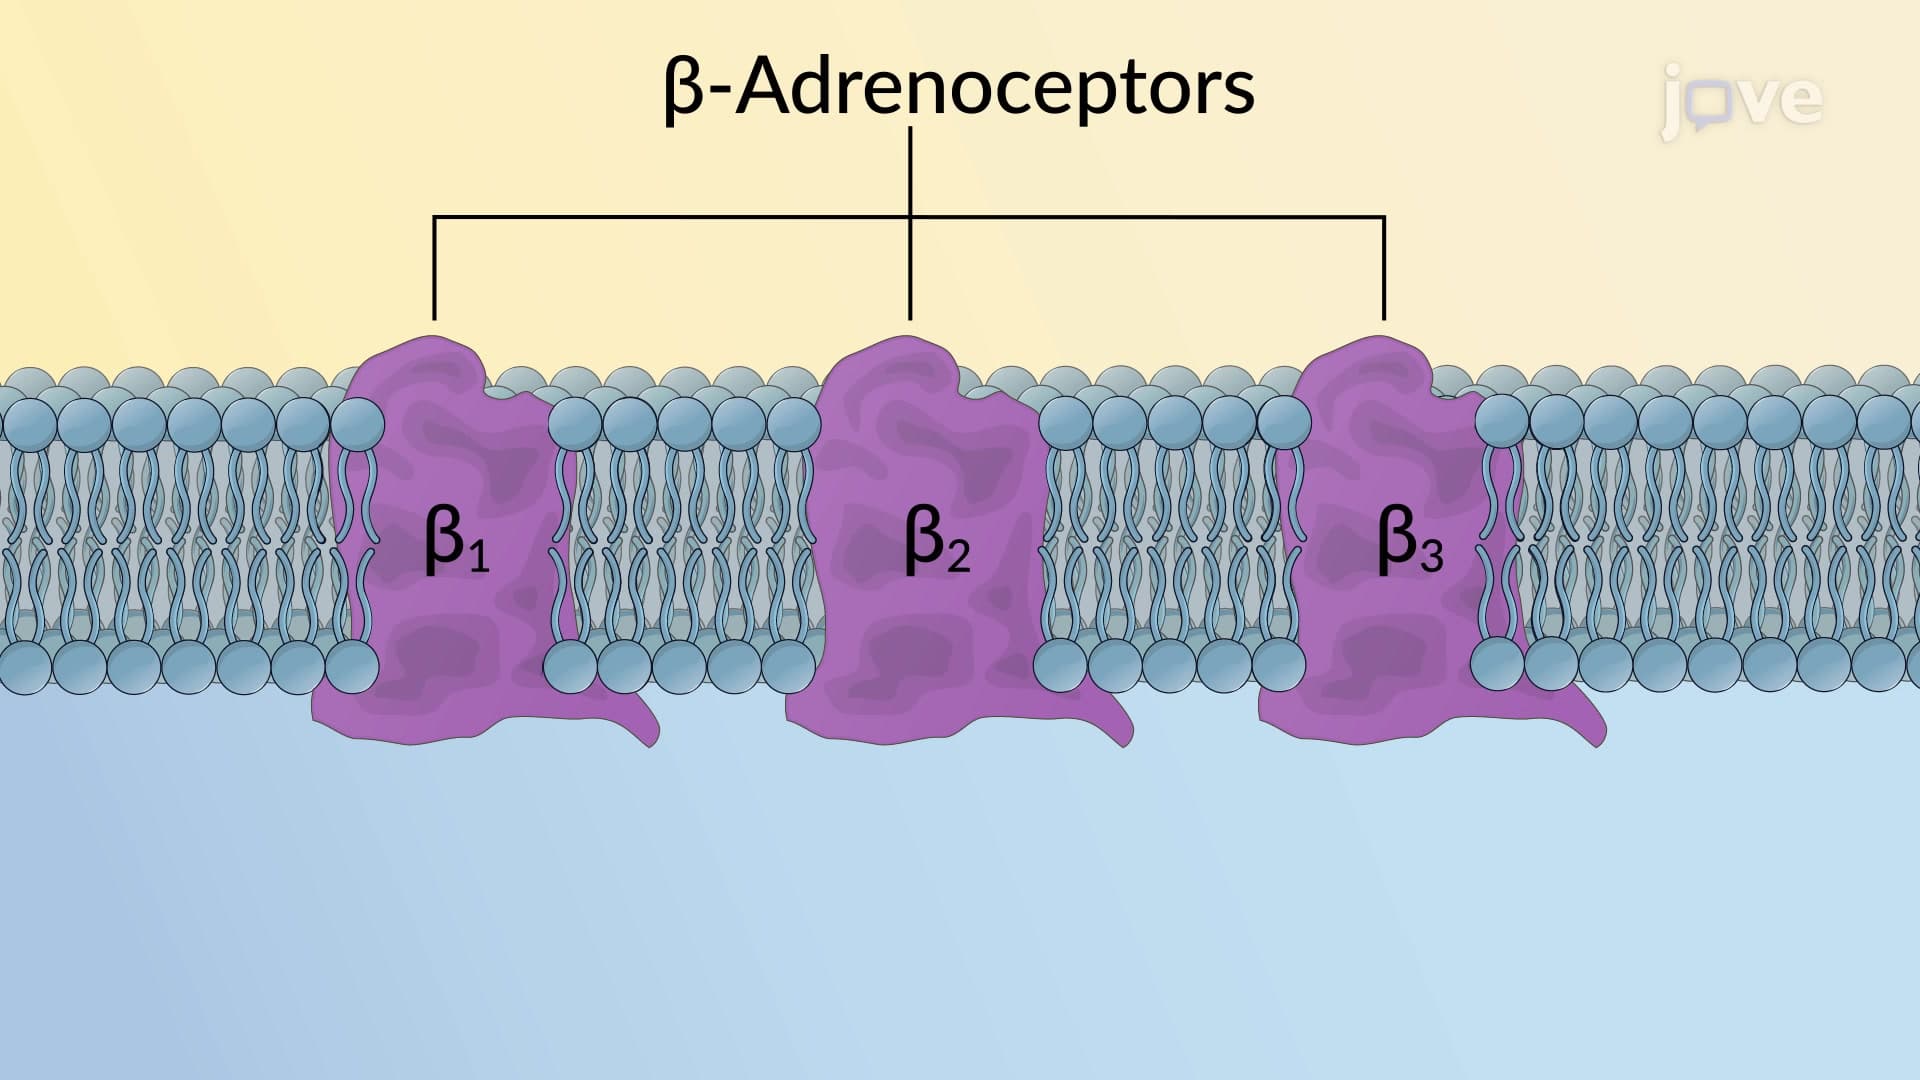
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...