Related Experiment Video
Updated: May 20, 2026
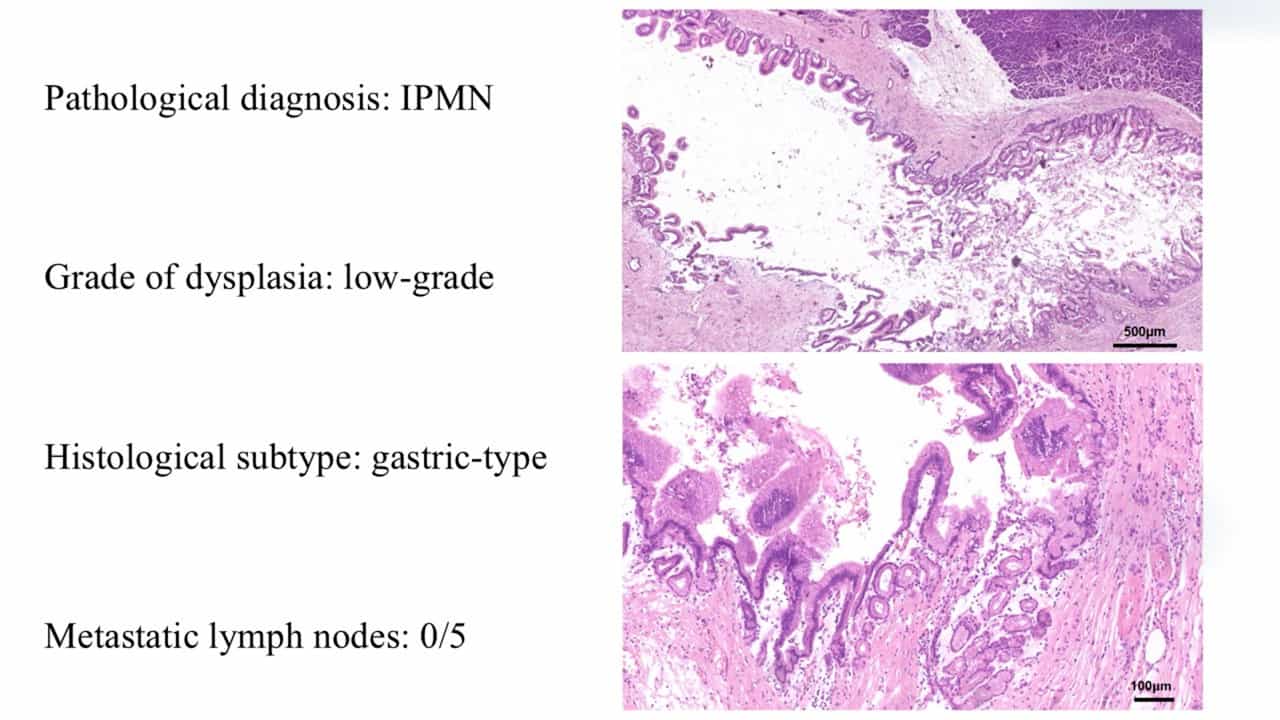

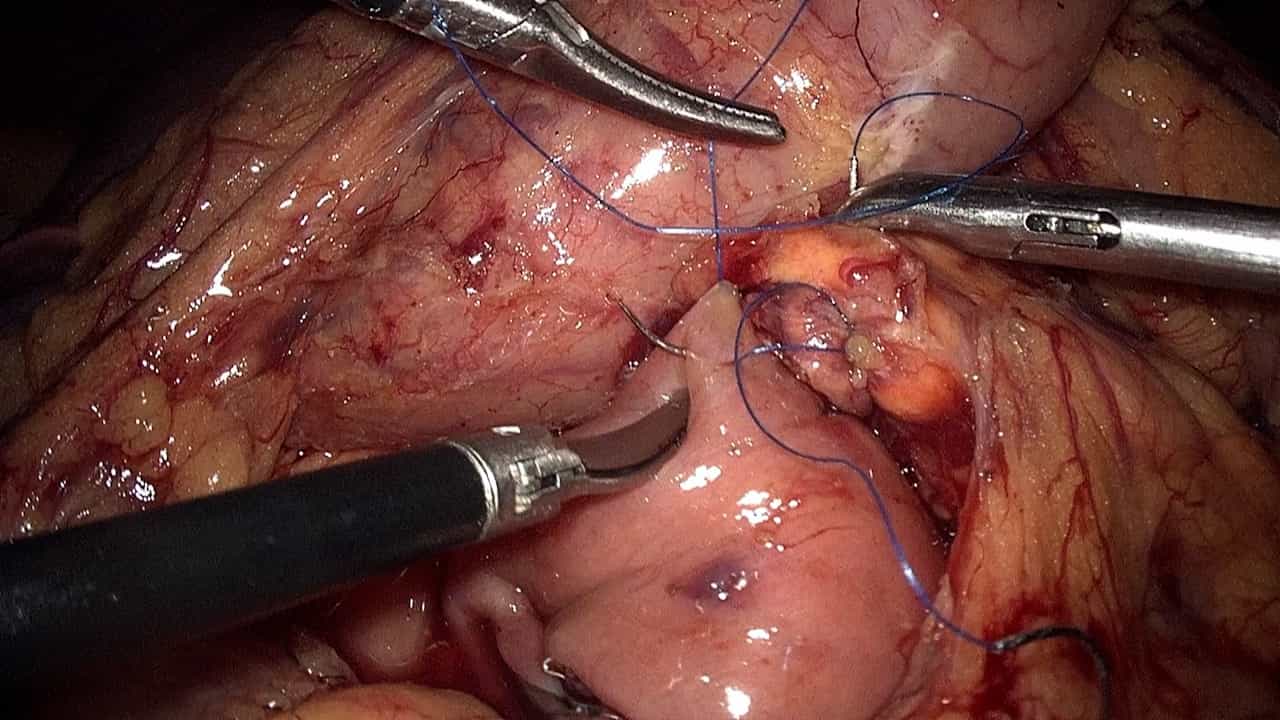
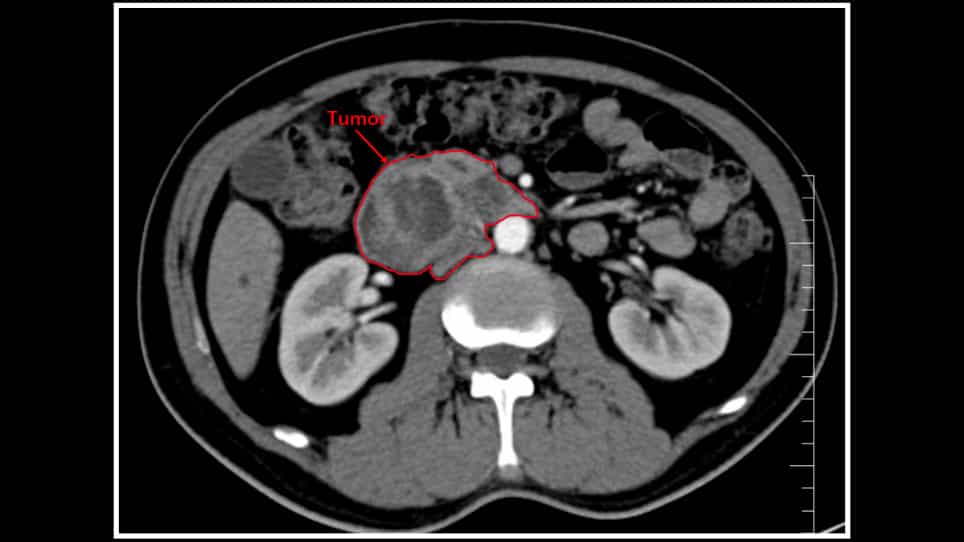
Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
[Strategy in intraductal papillary mucinous neoplasm of the pancreas]
Salvador Navarro Colás1, Eva C Vaquero Raya
1Servicio de Gastroenterología, Institut de Malalties Digestives i Metabòliques, Hospital Clínic, Institut d'Investigació Biomèdica August Pí i Sunyer (IDIBAPS), Centro de Investigación Biomédica en Red de Enfermedades Hepáticas y Digestivas (CIBERehd), Universidad de Barcelona, Barcelona, España. snavarro@clinic.ub.es

Abstract:
Intraductal papillary mucinous neoplasm (IPMN) is a premalignant pancreatic entity characterized by papillary growth of the ductal epithelium with rich mucin production and cystic dilatation of the main pancreatic duct and/or its branches. These neoplasms are often multifocal. Preoperative distinction between benign and malignant lesions is important to select the most appropriate treatment and to improve prognosis. Early surgical resection is the treatment of choice to avoid malignant transformation when predictive factors for malignancy are present. These factors include localization, cyst greater than 3cm, nodules in the cystic wall, atypias in the cyst fluid and the presence of symptoms. The extent of resection required for adequate treatment of IPMN of the pancreas is still controversial. Patients who retain a portion of their pancreas following resection of an IPMN need to be followed up with periodic imaging to detect recurrences, signs indicating a risk of malignant transformation, and metachronous lesions. The existence of possible synchronous or metachronous lesions in other organs should also be investigated.