Related Experiment Video
Updated: May 20, 2026
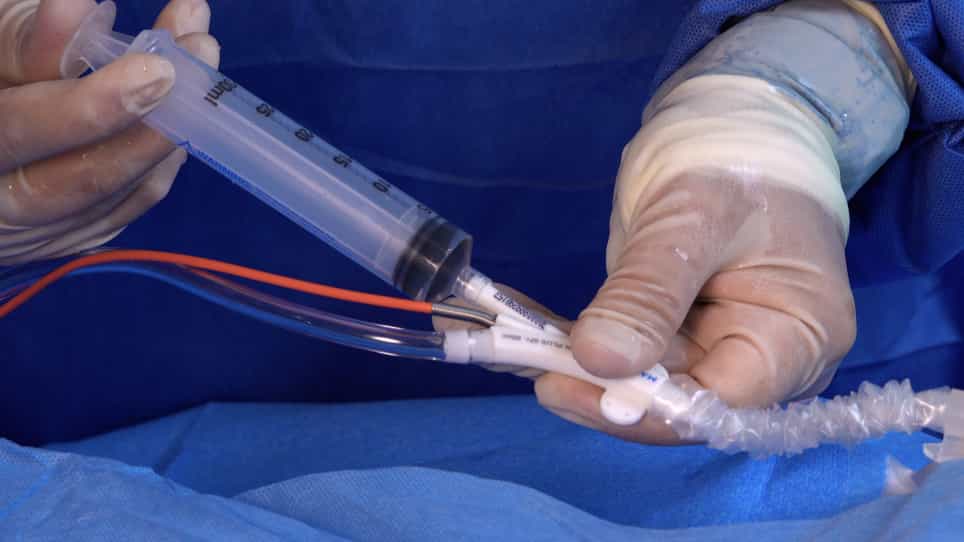
The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Beta blocker use after acute myocardial infarction in the patient with normal systolic function: when is it "ok" to
Anna Kezerashvili1, Kevin Marzo, Joshua De Leon
1Department of Medicine, Cardiology Division, Winthrop University Hospital, Mineola, NY, USA. anya@lucenko.com

Insights
Beta-blockers are recommended after acute myocardial infarction (AMI), but evidence for long-term use in low-risk patients with normal heart function is limited. This review examines optimal duration and patient subgroups benefiting from beta-blocker therapy post-AMI.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Beta-blockers (BB) have been a cornerstone therapy for acute myocardial infarction (AMI) for decades.
- Current guidelines recommend BB use post-AMI, but the evidence supporting long-term treatment in specific patient groups is debated.
Purpose of the Study:
- To review the evidence base for beta-blocker use after acute myocardial infarction.
- To clarify recommendations on the duration of beta-blocker therapy in patients with preserved left ventricular ejection fraction (LVEF) post-AMI.
- To identify patient subgroups who benefit most from beta-blockers after AMI.
Main Methods:
- Review of key clinical trials and guidelines concerning beta-blocker use post-AMI.
- Analysis of data regarding treatment duration and efficacy in patients with normal LVEF.
- Examination of subgroup analyses from relevant studies.
Main Results:
- The evidence for routine long-term beta-blocker use post-AMI, particularly in low-risk patients with preserved LVEF, is based on older trials and extrapolations.
- ACC/AHA guidelines have downgraded recommendations for BB use in low-risk patients.
- Limited data exists on optimal duration and specific benefit in subgroups without angina, hypertension, or dysrhythmia.
Conclusions:
- The optimal duration of beta-blocker therapy post-AMI in patients with preserved LVEF and without specific indications remains unclear.
- Further research is needed to define the precise role and duration of beta-blocker use for secondary prevention in diverse post-AMI populations.
- Current recommendations may need refinement based on contemporary evidence and patient-specific factors.
Abstract:
Beta-Blockers [BB] have been used extensively in the last 40 years after acute myocardial infarction [AMI] as part of therapy and in secondary prevention. The evidence for "routine" therapy with beta-blocker use post AMI rests largely on results of trials conducted over 25 years ago. However, there remains no clear recommendation regarding the appropriate duration of treatment with BBs in post AMI patients with normal left ventricular ejection fraction [LVEF] who are not experiencing angina, or who require BB for hypertension or dysrhythmia. Based on the latest ACC/AHA guidelines, BBs are recommended for early use in the setting of AMI, except in patients who are at low risk and then indefinitely as secondary prevention after AMI. This recommendation was downgraded to class IIa in low risk patients and the updated 2007 ACC/AHA guidelines suggest that the rationale for BB for secondary prevention is from limited data derived from extrapolations of chronic angina and heart failure trials. In this review, we examine the key trials that have shaped the current guidelines and recommendations. In addition, we attempt to answer the question of the duration of BB use in patients with preserved LVEF after acute MI, as well as which subgroups of patients benefits most from post AMI use of beta blockers.
Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:30
Heart Failure V: Medical Management
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...