Lisinopril pharmacokinetics and erythropoietin requirement in haemodialysis patients
Related Experiment Video
Updated: May 20, 2026
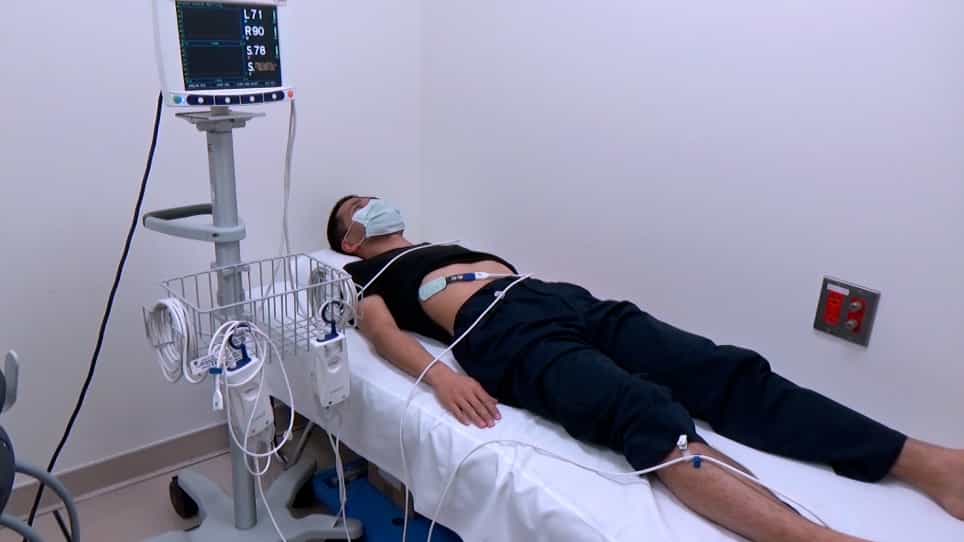
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Wolfgang Winnicki1, Anna Prehslauer, Josef Kletzmayr
1Division of Nephrology and Dialysis, Department of Medicine III, Medical University of Vienna, Vienna, Austria.

Background:
There is ongoing controversy whether angiotensin-converting enzyme inhibitors (ACE-I) contribute to anaemia by causing hyporesponsiveness to erythropoiesis-stimulating agents (ESA). However, it is unknown whether or not plasma levels or area under the curve (AUC) of ACE-I are associated with responsiveness to ESA therapy.
Materials And Methods:
We examined the association between lisinopril AUC, lisinopril plasma levels and ESA requirements that was assessed using an ESA index [(ESA IU/week/body weight kg)/(haemoglobin g/dL)]. After screening 184 haemodialysis patients, 14 fulfilled the inclusion criteria, mainly long-term use of oral lisinopril in the upper end of dosage range for this population with stable haemoglobin levels and intravenous ESA therapy. Lisinopril plasma levels were measured at eight different time points (predialysis, immediate post-dialysis and hourly for 6h thereafter; AUC1), and the seven post-dialysis lisinopril plasma levels were used for calculation of AUC2.
Results:
The mean ESA index of all patients was 27·90±25·84 (IU/week/kg)/(g/dL). Average lisinopril AUC1 was 1212·48±1209·75 [mg*h/L], whereas AUC2 averaged 947·67±977·07 [mg*h/L]. Two patients (14%) had no detectable lisinopril plasma levels, indicating their noncompliance. There was no association between ESA index and AUC or plasma levels of lisinopril at any time point for all 14 or for the 12 compliant patients.
Conclusions:
Our study shows that long-term, high-dose lisinopril therapy has no effect on ESA responsiveness. Thus, avoidance or a dose reduction of ACE-I in dialysis patients will not necessarily lead to reduced ESA requirements and costs.
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Hemodialysis III: Nursing Management
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...