Related Experiment Video
Updated: May 20, 2026


Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
Diastolic dysfunction, prolonged QTc interval and pericardial effusion as predictors of mortality in acute
Nikhil Nadkarni1, Deepak Kumar Bhasin, Surinder Singh Rana
1Departments of Gastroenterology, Post Graduate Institute of Medical Education and Research, Chandigarh, India.

Background And Aim:
The cardiac changes in acute pancreatitis have been earlier studied but the data on their prognostic significance is limited. This study was done to determine electrocardiographic (ECG) and echocardiographic changes in acute pancreatitis and determine their prognostic significance.
Methods:
Fifty-two consecutive patients (mean age 36.5 ± 11 years (44 males)) with acute pancreatitis and without prior cardiovascular comorbidites were prospectively enrolled and subjected to clinical, laboratory and radiological investigation. ECG and echocardiography was done at admission and during follow up.
Results:
Seventeen patients (32.7%) had mild pancreatitis and 35 (67.3%) patients had severe pancreatitis. Sinus tachycardia was the most common ECG abnormality. QTc prolongation was seen in 30/52 (57.7%) patients. On echocardiography, no patient had systolic dysfunction but 31/52 (59.6%) patients had diastolic dysfunction. All 22 patients with QTc interval < 440 ms survived compared with 8/30 patients with QTc interval ≥ 440 ms who died (P = 0.01). All eight patients who died had evidence of diastolic dysfunction (100%). None of the patients without diastolic dysfunction succumbed to illness (P = 0.02). Pericardial effusion was present in 6/52 (11.5%) patients. Of the eight patients who died, pericardial effusion was present in three (37.5%) patients and this frequency was significantly higher than that in patients who recovered (3/44 [6.8%]; P = 0.04).
Conclusion:
Electrocardiographic and echocardiographic changes are seen in more than 50% of patients with acute pancreatitis. Prolonged QTc interval, pericardial effusion and diastolic dysfunction are associated with higher mortality.

Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
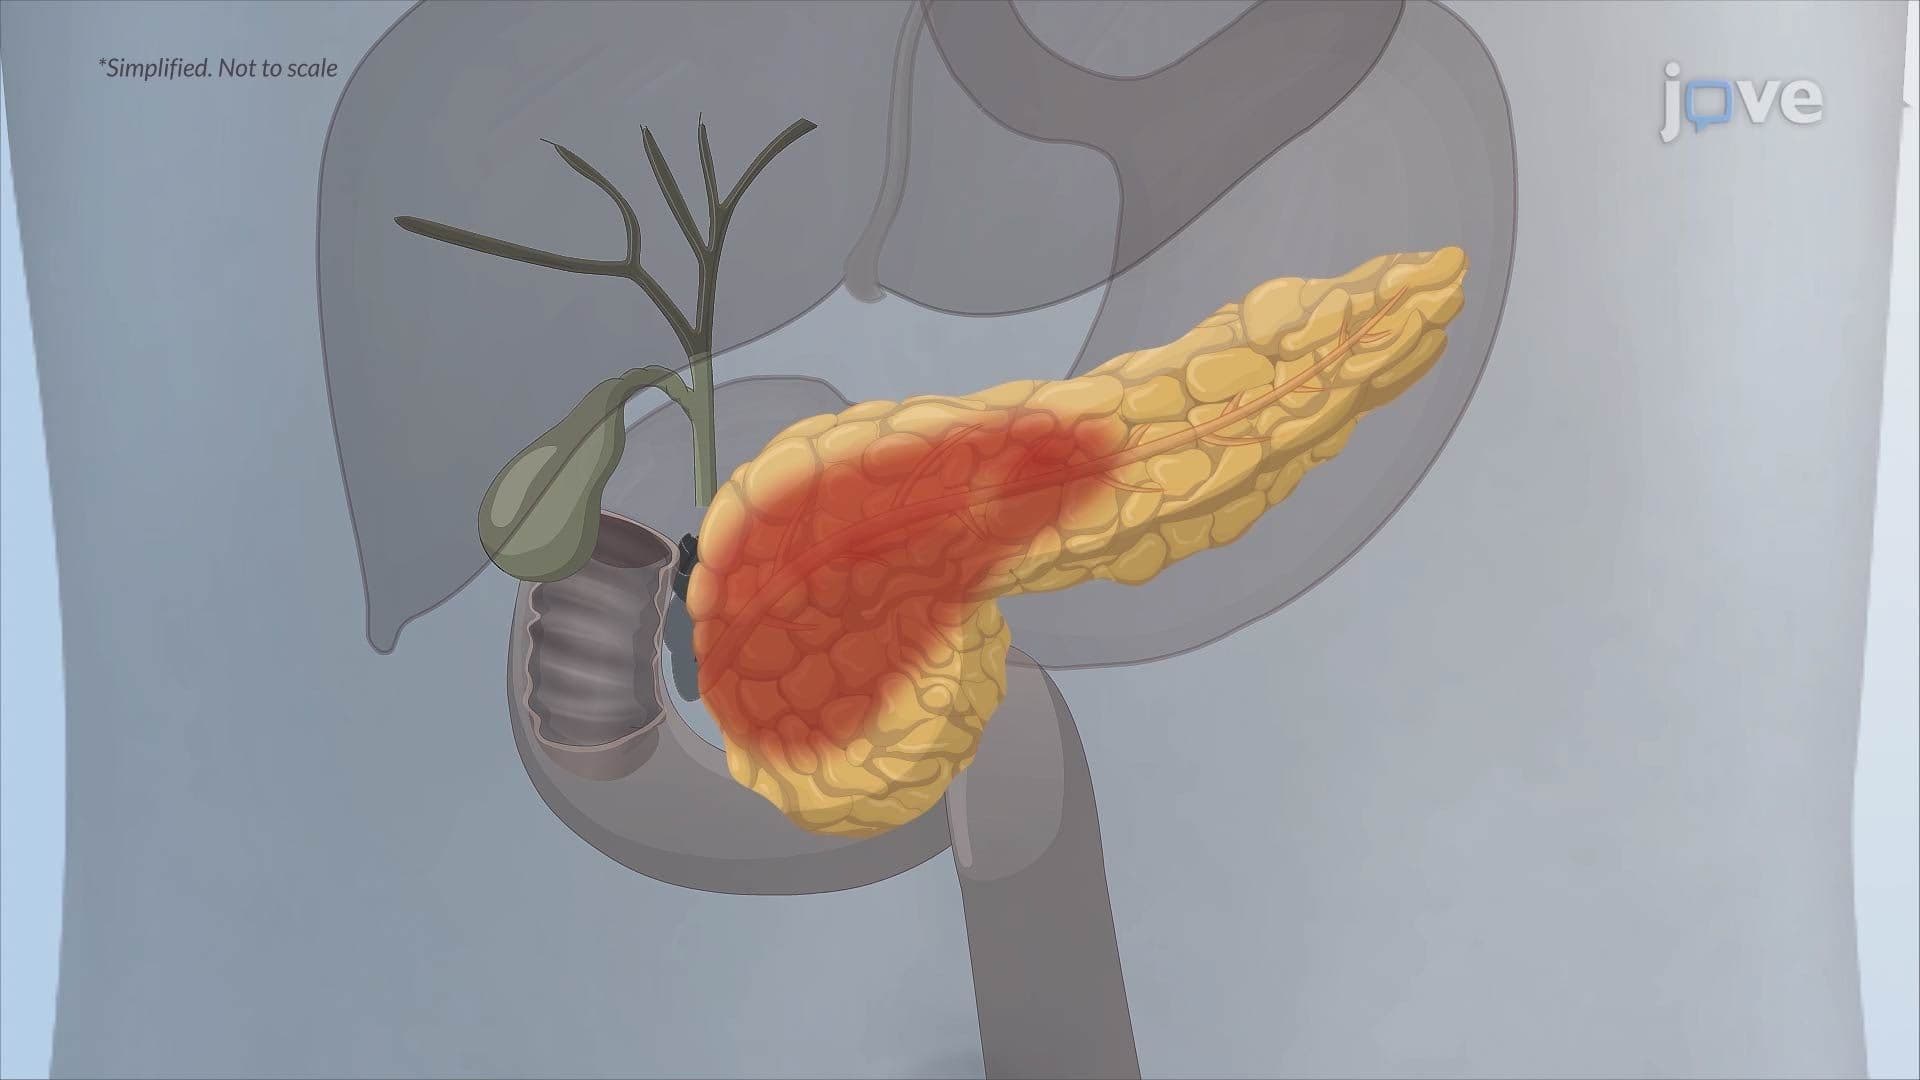
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...