Related Experiment Video
Updated: Oct 14, 2026
Microvascular Decompression: Salient Surgical Principles and Technical Nuances
Published on: July 5, 2011
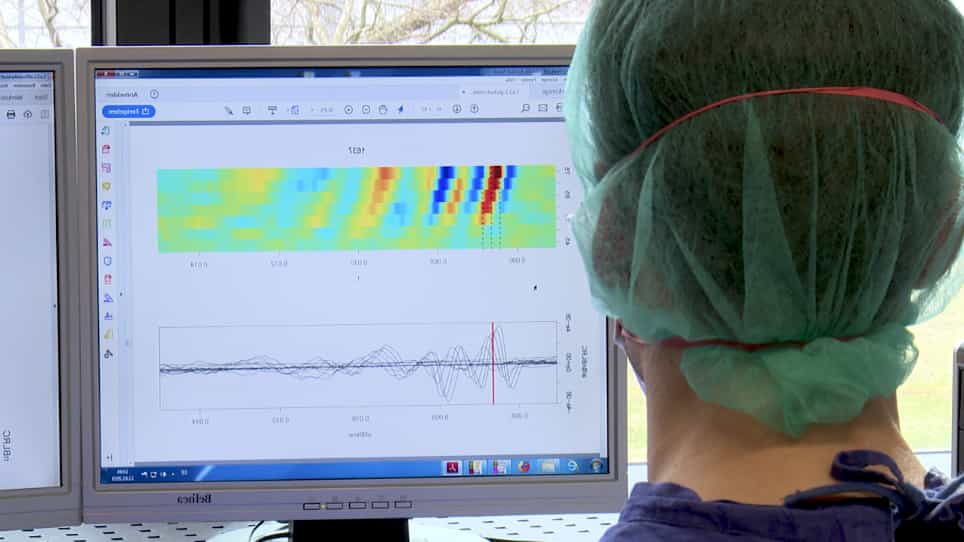
[Monitoring of auditory brainstem response (ABR) during microvascular decompression (MVD): results in 400 cases]
T Kakizawa1, T Shimizu, T Fukushima
1Kanto Neurosurgical Hospital, Kumagaya, Japan.

Abstract:
In recent years, microvascular decompression (MVD) has been well established as a definitive surgical procedure in the management of hemifacial spasm (HFS) and trigeminal neuralgia (TN). With careful microsurgical technique, MVD can be performed accurately without significant morbidity. However, some incidence of postoperative hearing disturbance has been reported as one the annoying complications. In order to avoid complications of the 8th nerve, we have been using intraoperative monitoring of auditory brainstem response (ABR) for the past 5 years. This report presents the results of ABR monitoring in our personal series of 400 MVD cases. Our clinical results consist of 225 HFS and 175 TN, who underwent recording of ABR before, during and after MVD, including audiometry before and after the operation. There are 107 males and 293 females with the age ranging between 22 and 79, averaging 55 years old. Under routine general endotracheal anesthesia, the patient was placed in a lateral position and a small retromastoid opening was made. Pieces of teflon tape and fibrin glue was used to transpose, reposition and fixate the offending vessels. We used CADWELL 5200 and recorded ABR with needle electrode and click sound averaging 1500 times. ABR recordings were performed on admission, at the beginning of the operation, during nerve decompression and wound closure and at the time of discharge. The interpeak latency of waves I-V and the wave V amplitude during nerve decompression or wound closure were compared with those on admission.(ABSTRACT TRUNCATED AT 250 WORDS)