Renal tubular acidosis type IV in hyperkalaemic patients--a fairy tale or reality?
Related Experiment Video
Updated: May 19, 2026

Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Christian S Haas1, Inga Pohlenz, Ulrich Lindner
1Department of Medicine I, University of Luebeck, Ratzeburger Allee 160, Luebeck, Germany. cs_haas@yahoo.com

Objective:
Hyperkalaemia is a common feature in hospitalized patients and often attributed to drugs antagonizing the renin-angiotensin-aldosterone system (RAAS) and/or acute kidney injury (AKI), despite significantly preserved glomerular filtration rate (GFR). The objective of this study was to determine the prevalence and role of renal tubular acidosis type IV (RTA IV) in the development of significant hyperkalaemia.
Design:
A single-centre retrospective study.
Patients:
Patients admitted to a University Hospital over 12 months.
Measurements:
Patients with a potassium value > 6·0 mm were identified. Clinical and laboratory data were revisited, and patients with a normal anion gap metabolic acidosis were evaluated for the existence of RTA IV.
Results:
A total of 57 patients having significant hyperkalaemia (>6·0 mm) were identified. Twelve patients had end-stage renal disease, while 21 patients had solely AKI or progressive chronic renal failure. RTA IV was present in 24 patients (42%), of whom 71% had pre-existing renal insufficiency because of diabetic nephropathy or tubulointerstitial nephritis. All hyperkalaemic patients with urinary/serum electrolytes suggestive of RTA IV had evidence of AKI, but creatinine levels were significantly lower (P < 0·05), while the number of drugs antagonizing the RAAS was comparable.
Conclusion:
We demonstrated that RTA IV (i) is very common in patients with hyperkalaemia; (ii) should always be suspected in hyperkalaemic patients with only moderately impaired GFR; and (iii) may result in significant hyperkalaemia in the presence of both AKI and drugs antagonizing the RAAS.

Related Concept Videos
 01:29
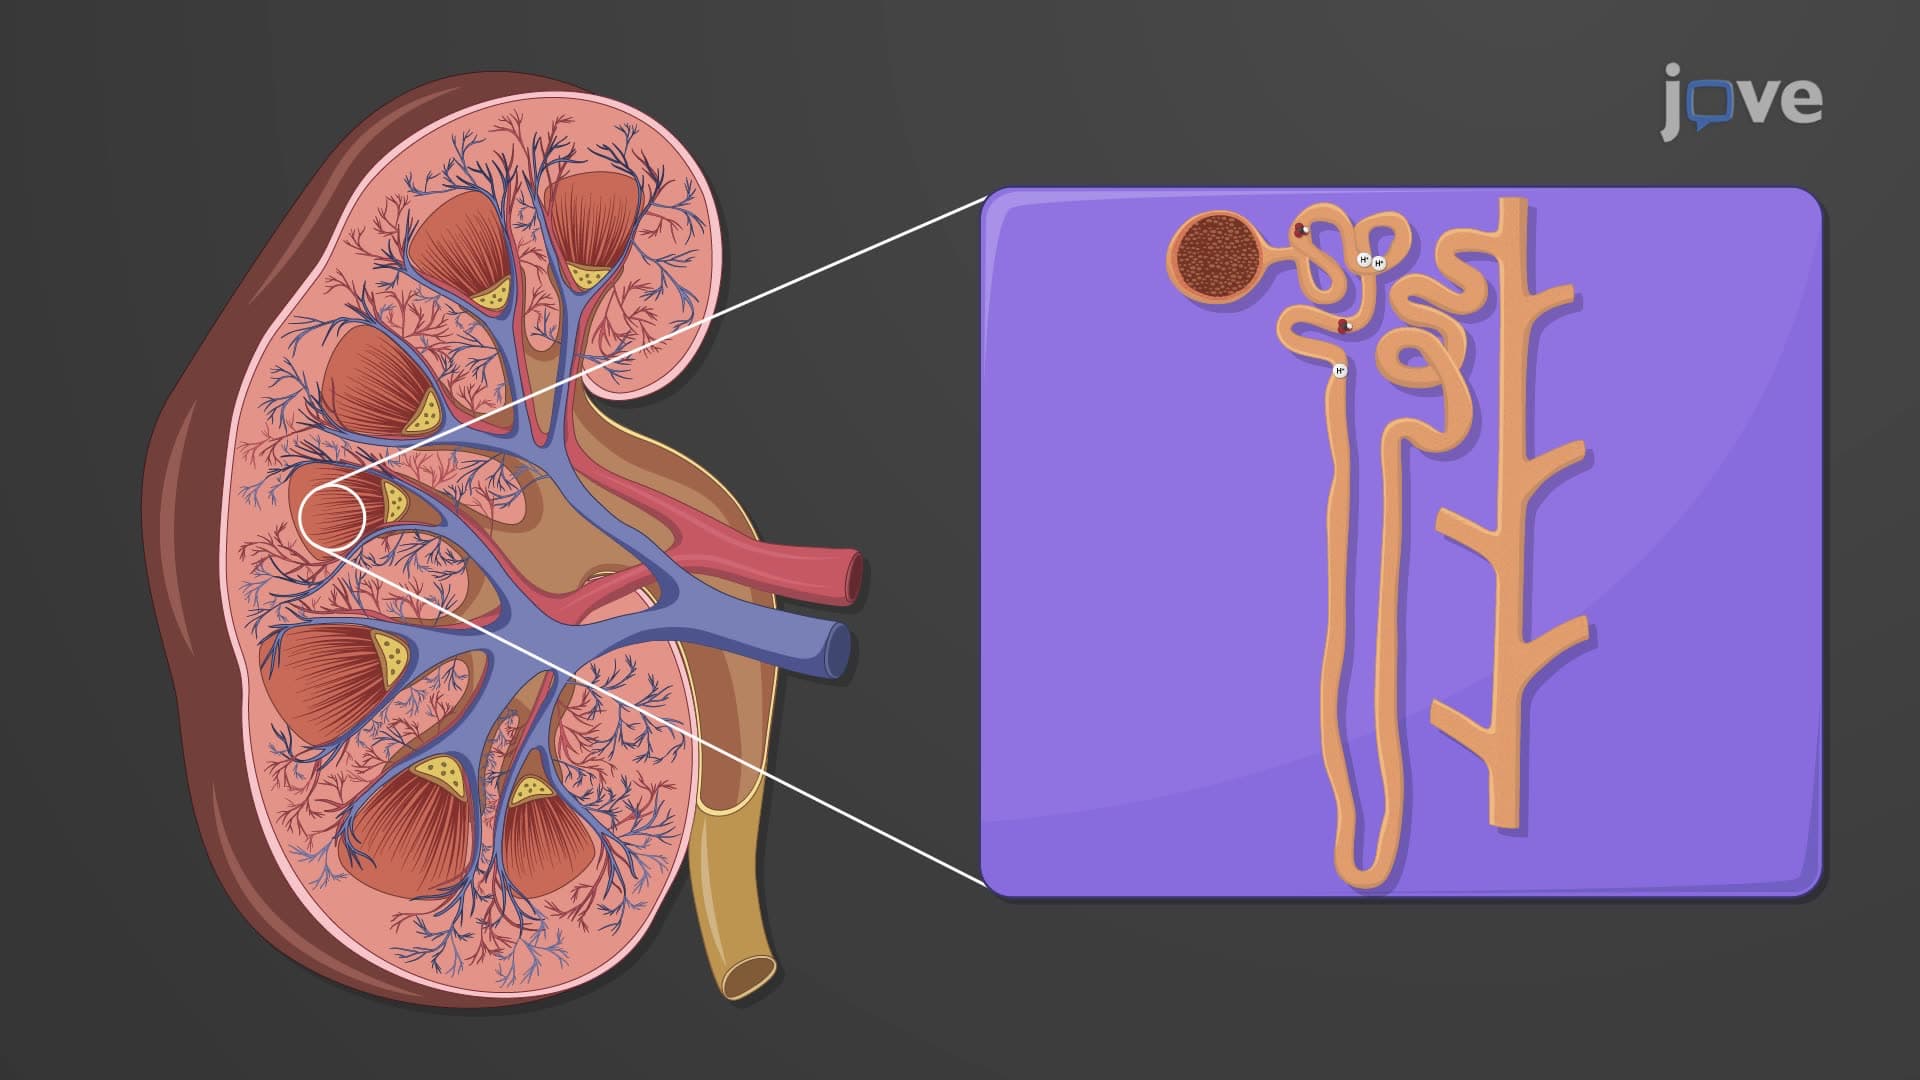
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:22
Diabetic Ketoacidosis ll: Pathophysiology
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:25
Diabetic Ketoacidosis l: Introduction