Related Experiment Video
Updated: May 19, 2026


Electromyometrial Imaging of Uterine Contractions in Pregnant Women
Published on: May 26, 2023
Antispasmodics for labour
Anke C Rohwer1, Oswell Khondowe, Taryn Young
1Centre for Evidence-based Health Care, Faculty of Medicine and Health Sciences, Stellenbosch University, Tygerberg, South Africa. arohwer@sun.ac.za.

Background:
Prolonged labour can lead to increased maternal and neonatal mortality and morbidity due to increased risks of maternal exhaustion, postpartum haemorrhage and sepsis, fetal distress and asphyxia and requires early detection and appropriate clinical response. The risks for complications of prolonged labour are much greater in poor resource settings. Active management of labour versus physiological, expectant management, has shown to decrease the occurrence of prolonged labour. Administering antispasmodics during labour could also lead to faster and more effective dilatation of the cervix. Interventions to shorten labour, such as antispasmodics, can be used as a preventative or a treatment strategy in order to decrease the incidence of prolonged labour. As the evidence to support this is still largely anecdotal around the world, there is a need to systematically review the available evidence to obtain a valid answer.
Objectives:
To assess the effects of antispasmodics on labour in term pregnancies.
Search Methods:
We searched the Cochrane Pregnancy and Childbirth Group's Trials Register (2 September 2011), the ProQuest dissertation and thesis database, the dissertation database of the University of Stellenbosch (2 September 2011), Google Scholar (2 September 2011) and reference lists of articles. We also contacted pharmaceutical companies and experts in the field. We did not apply language restrictions.
Selection Criteria:
Randomised controlled trials comparing antispasmodics with placebo or no medication in women with term pregnancies.
Data Collection And Analysis:
Two review authors independently screened abstracts and selected studies for inclusion, assessed risk of bias and extracted data. Data were checked for accuracy. We contacted trial authors when data were missing.
Main Results:
Nineteen trials (n = 2798) were included in the review. Fifteen trials (n = 2129) were included in the meta-analysis. Antispasmodics used included valethamate bromide, hyoscine butyl-bromide, drotaverine hydrochloride, rociverine and camylofin dihydrochloride. Most studies included antispasmodics as part of their package of active management of labour. Overall, the quality of studies was poor, as only four trials were assessed as low risk of bias. Eleven trials (n = 1507) reported on the duration of first stage of labour, which was significantly reduced by an average of 65.80 minutes when antispasmodics were administered (mean difference (MD) -65.80 minutes; 95% confidence Interval (CI) -92.32 to -39.28). Seven studies (n = 797) reported on the total duration of labour, which was significantly reduced by an average of 85.51 minutes (MD -85.51 minutes; 95% CI -121.81 to -49.20). Five studies (n = 632) had data for the outcome: rate of cervical dilatation. Administration of antispasmodics significantly increased the rate of cervical dilatation by an average of 0.55 cm/h (MD 0.55 cm/h; 95% CI 0.22 to 0.87). Antispasmodics did not affect the duration of second and third stage of labour. The rate of normal vertex deliveries was not affected either. Only one study explored pain relief following administration of antispasmodics and no conclusions can be drawn on this outcome. There was significant heterogeneity for most outcomes and therefore, we undertook random-effects meta-analysis. Subgroup analysis was undertaken to explore heterogeneity, but remained largely unexplained. Maternal and neonatal adverse events were reported inconsistently. The main maternal adverse event reported was tachycardia. No serious neonatal adverse events were reported.
Authors' Conclusions:
There is low quality evidence that antispasmodics reduce the duration of first stage of labour and increase the cervical dilatation rate. There is very low quality evidence that antispasmodics reduce the total duration of labour. There is moderate quality evidence that antispasmodics do not affect the rate of normal vertex deliveries. There is insufficient evidence to make any conclusions regarding the safety of these drugs for both mother and baby. Large, rigorous randomised controlled trials are needed to evaluate the effect of antispasmodics on prolonged labour and to evaluate their effect on labour in a context of expectant management of labour.
Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also promote...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
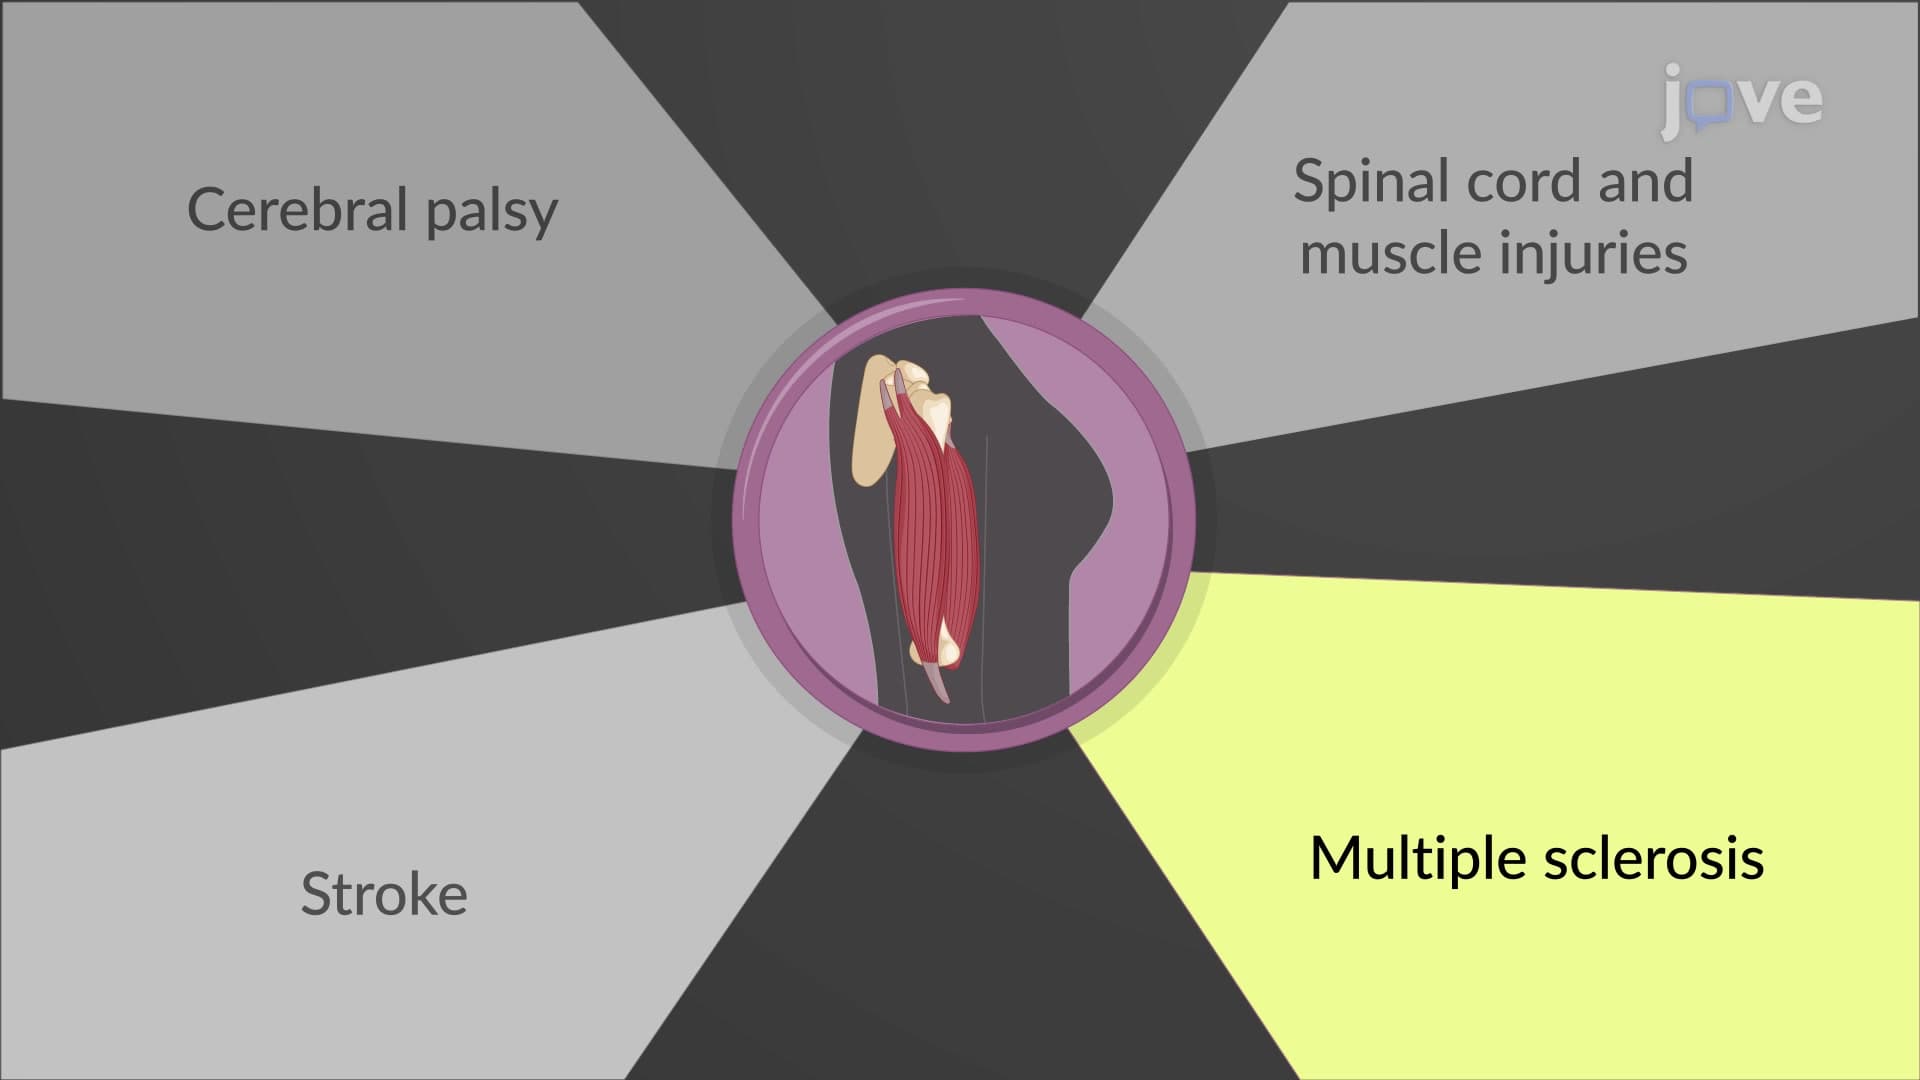
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic drugs,...
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...