Related Experiment Video
Updated: May 19, 2026


Microsatellite DNA Genotyping and Flow Cytometry Ploidy Analyses of Formalin-fixed Paraffin-embedded Hydatidiform Molar Tissues
Published on: October 20, 2019
Complete hydatidiform mole coexisting with a live fetus
1Department of Obstetrics and Gynecology, Faculty of Medicine, Karadeniz Technical University, Trabzon, Turkey. mesutunsal@gmail.com

The co-existence of a hydatidiform mole with a living fetus is a rare phenomenon. The condition is a dilemma with respect to the diagnosis and management of associated maternal (a risk of maternal complications, such as preeclampsia, hyperthyrodism, and a risk of malignancy) and fetal (elevated risk of spontaneous abortion, neonatal thyrotoxicosis) complications. A 27-year-old woman was referred to our hospital with a diagnosis of hydatidiform mole and live fetus. The pregnancy was unremarkable except for the complaints of excessive nausea and vomiting. Successive ultrasound examinations demonstrated a normally growing live fetus (14 weeks) alongside a normal placenta and an additional intrauterine echogenic mass with features of hydatidiform mole. Genetic amniocentesis at 18 weeks' of gestation showed normal diploid fetal karyotype. At 20 weeks of pregnancy, a control prenatal visit revealed intrauterine fetal death. The follow-up period for two years was unremarkable. In the case of a normal fetal karyotype and the absence of serious signs of maternal pathology, waiting until fetal viability is achieved can justifiably be proposed, however there is still a risk of prenatal complications such as intrauterine death.
The co-existence of a hydatidiform mole with a living fetus is a rare phenomenon. The condition is a dilemma with respect to the diagnosis and management of associated maternal (a risk of maternal complications, such as preeclampsia, hyperthyrodism, and a risk of malignancy) and fetal (elevated risk of spontaneous abortion, neonatal thyrotoxicosis) complications. A 27-year-old woman was referred to our hospital with a diagnosis of hydatidiform mole and live fetus. The pregnancy was unremarkable except for the complaints of excessive nausea and vomiting. Successive ultrasound examinations demonstrated a normally growing live fetus (14 weeks) alongside a normal placenta and an additional intrauterine echogenic mass with features of hydatidiform mole. Genetic amniocentesis at 18 weeks' of gestation showed normal diploid fetal karyotype. At 20 weeks of pregnancy, a control prenatal visit revealed intrauterine fetal death. The follow-up period for two years was unremarkable. In the case of a normal fetal karyotype and the absence of serious signs of maternal pathology, waiting until fetal viability is achieved can justifiably be proposed, however there is still a risk of prenatal complications such as intrauterine death.

Related Concept Videos
 01:18
Uterus and Cervix
The uterus is securely anchored within the pelvic cavity by paired broad ligaments on either side. It is further stabilized by three pairs of...
 01:27
Cytomegalovirus Disease
 01:16
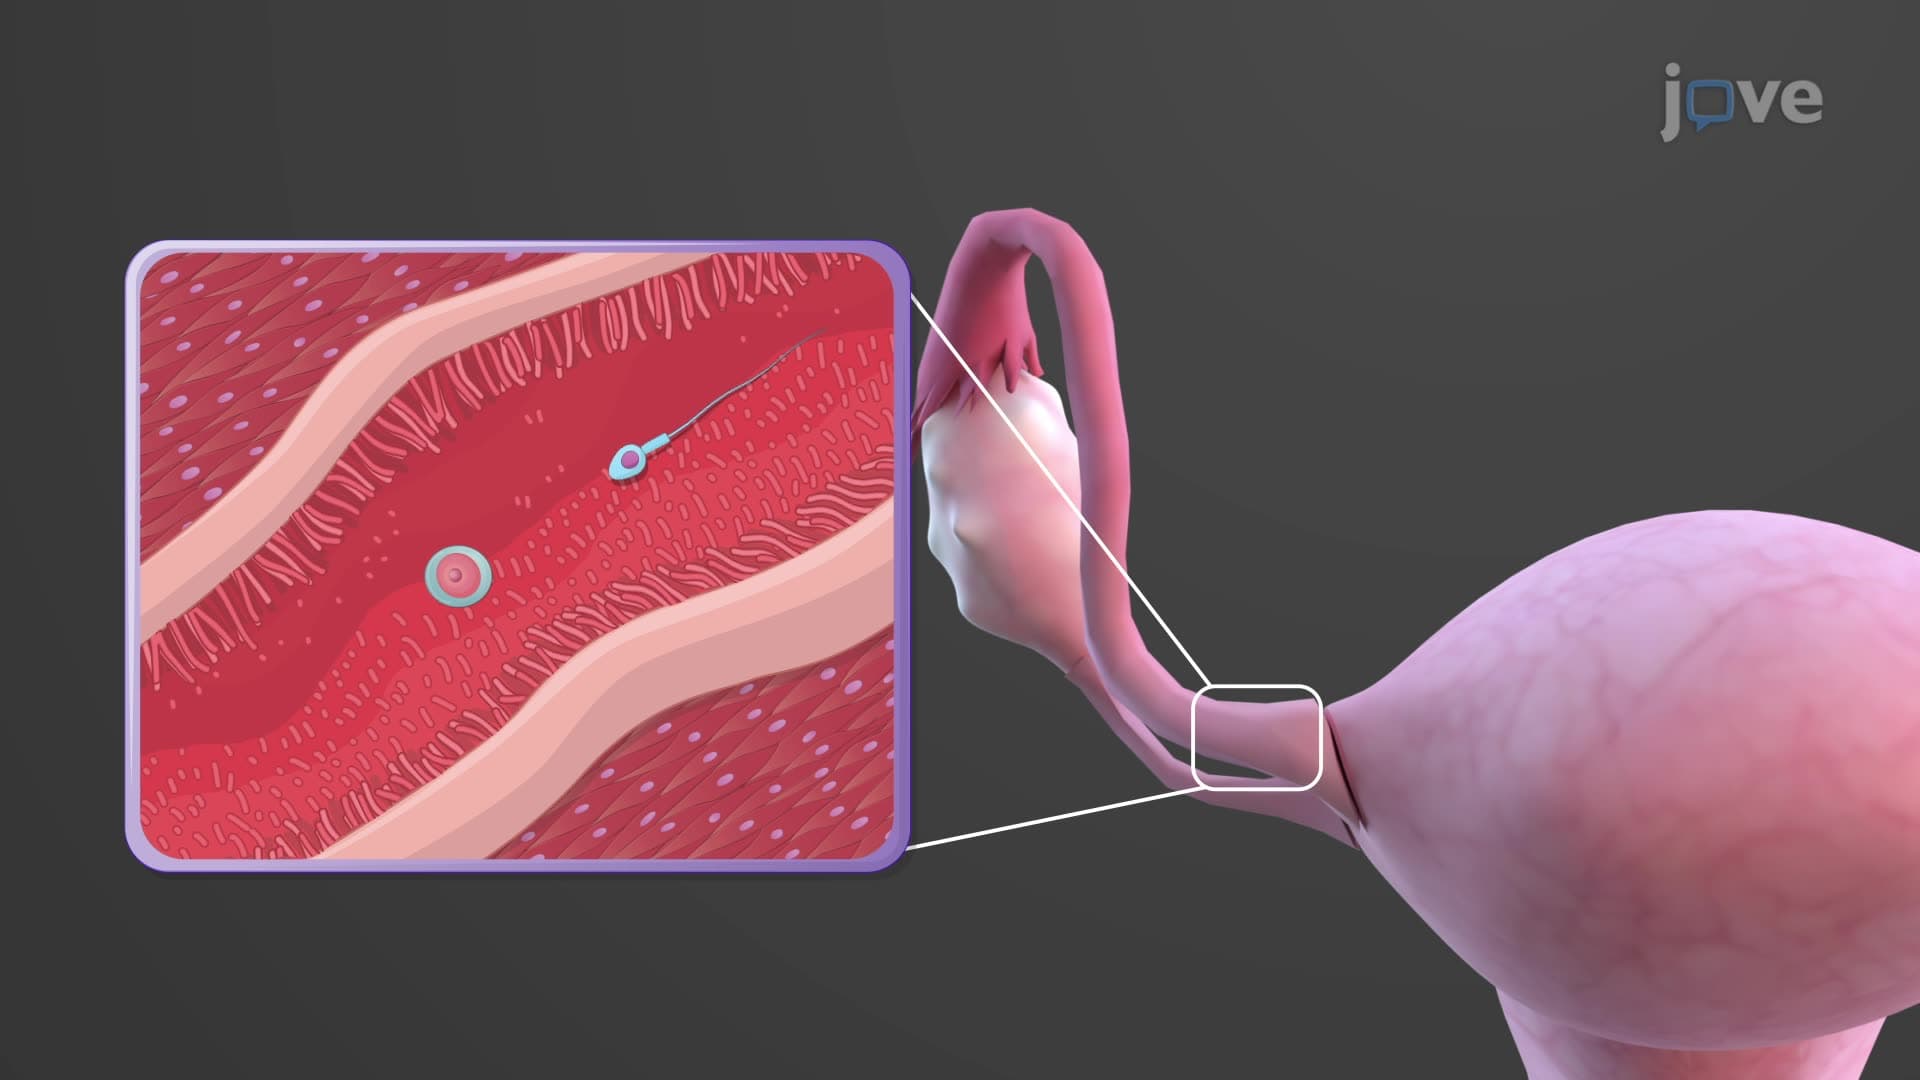
Uterine Tubes
 01:07
Teratogenicity
 01:33
Cleavage and Blastulation