Related Experiment Video
Updated: May 19, 2026
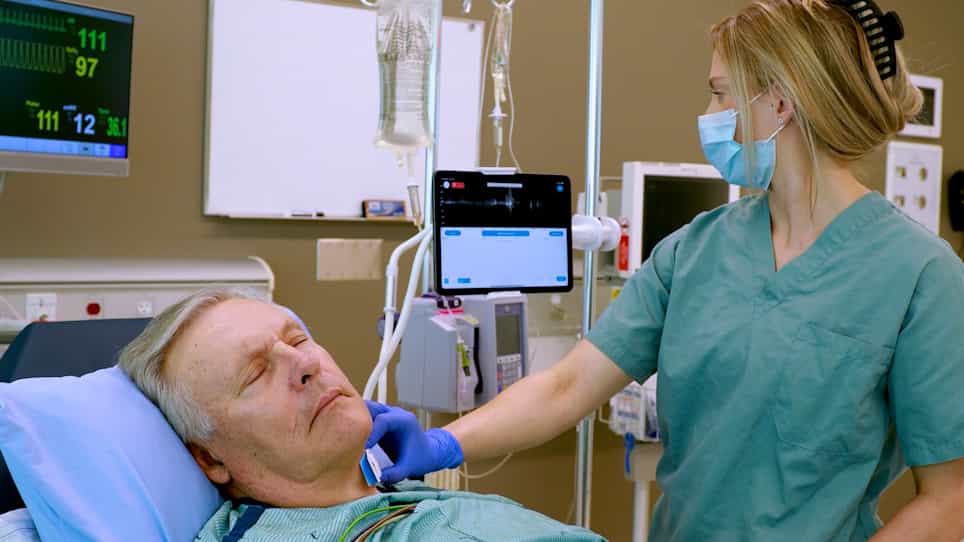

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Stroke volume variation as a predictor of fluid responsiveness in patients undergoing airway pressure release
K Suehiro1, H Rinka, J Ishikawa
1Emergency and Critical Care Medical Center, Osaka City General Hospital, Department of Anesthesiology, Osaka City University Graduate School of Medicine, Osaka, Japan. suehirokoichi@yahoo.co.jp

Abstract:
We investigated the effectiveness of stroke volume variation (SVV) shown by the Vigileo-FloTrac™ system (Edwards Lifesciences, Irvine, CA) to predict fluid responsiveness in patients undergoing airway pressure release ventilation (APRV). All 80 patients mechanically ventilated in the intensive care unit of our hospital from April to November 2010 were included in this study. After starting APRV, Ringer's lactate solution was administered for 30 minutes. Haemodynamic variables including heart rate, mean arterial pressure, cardiac index (CI), stroke volume index (SVI) and SVV were measured before and after volume loading. SVV before volume loading was significantly correlated with absolute change in SVV (ΔSVV) and percentage change in stroke volume index (ΔSVI) after volume loading (ΔSVV: P<0.05, r2=0.534; ΔSVI: P<0.05, r2=0.217). Of the 80 patients, 38 (47.5%) were responders to intravascular volume expansion (increase in CI≥15%) and 42 (52.5%) were non-responders (increase in CI<15%). Receiver operating characteristic (ROC) curves were generated for SVV and central venous pressure by varying the discriminating threshold of the variable and areas under the ROC curves were calculated. The areas under the ROC curves were 0.793 for SVV (95% confidence interval: 0.709-0.877) and 0.442 for central venous pressure (95% confidence interval: 0.336-0.549), which were significantly different (P<0.05). The optimal threshold value of SVV to discriminate between responders and nonresponders was 14% (sensitivity: 78.9%; specificity: 64.3%). We found that SVV was able to predict fluid responsiveness in patients undergoing APRV with acceptable levels of sensitivity and specificity.
Related Concept Videos
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: