Related Experiment Video
Updated: May 19, 2026


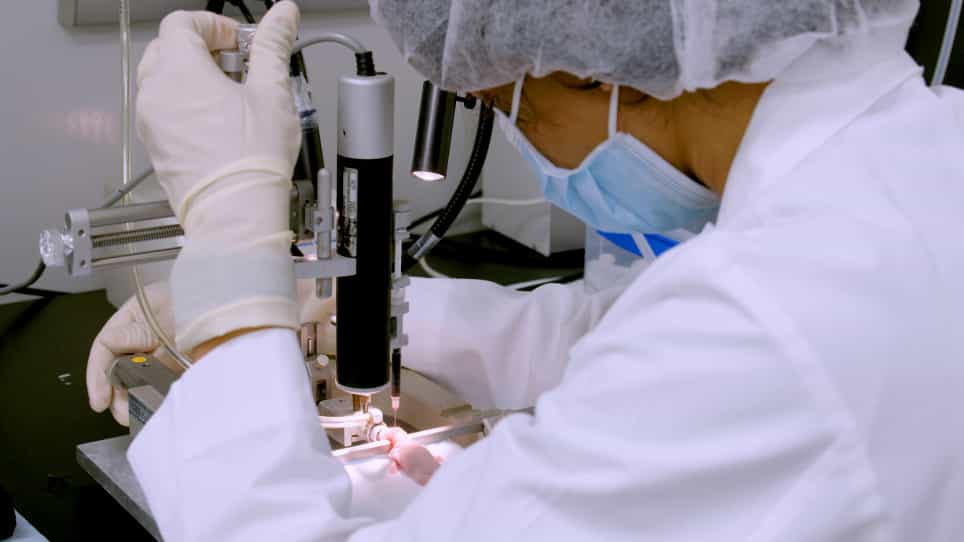
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Reduced ventricular shunt rate in very preterm infants with severe intraventricular hemorrhage: an institutional
Nima Alan1, Sunil Manjila, Nori Minich
1Division of Pediatric Neurosurgery, Rainbow Babies & Children’s Hospital,University Hospitals Case Medical Center Neurological Institute, Case Western Reserve University School of Medicine, Cleveland, Ohio, USA.

Insights
Survival for extremely premature infants with severe intraventricular hemorrhage (IVH) has improved. Surgical intervention for hydrocephalus in these infants has significantly decreased over 12 years due to better neonatal care.
Area of Science:
- Neonatalogy
- Pediatric Neurosurgery
- Developmental Pediatrics
Background:
- Extremely low gestational age newborns (ELGANs) face significant risks, including intraventricular hemorrhage (IVH), despite improved survival rates.
- Severe IVH can lead to hydrocephalus, often requiring surgical intervention like ventriculoperitoneal (VP) shunts.
- Understanding the long-term outcomes and shunt requirements in ELGANs with severe IVH is crucial for optimizing care.
Purpose of the Study:
- To review outcomes for ELGANs with severe IVH over a 12-year period.
- To determine the natural history of severe IVH in ELGANs.
- To analyze the frequency and trends of ventriculoperitoneal (VP) shunt placement in this vulnerable population.
Main Methods:
- Retrospective review of a cohort of ELGANs admitted between 1997 and 2008.
- Data sourced from neonatal intensive care unit (NICU) databases, neurosurgery logs, and medical records.
- Statistical analysis (Pearson chi-square test) to compare outcomes between two 5-year periods (1997-2001 and 2004-2008).
Main Results:
- 111 out of 1335 ELGANs (8.3%) experienced severe IVH.
- Incidence of severe IVH, survival rates, and risk factors remained stable.
- A significant reduction in the requirement for temporary ventriculosubgaleal (VSG) shunts and permanent VP shunts was observed in the later period (2004-2008) compared to the earlier period (1997-2001).
- Complication rates for VSG shunts were 20% (12% infection, 8% malfunction).
- 16% of all ELGANs with severe IVH ultimately required permanent shunt insertion, with 35% of those needing revision within the first year.
Conclusions:
- There has been a marked decrease in the need for surgical intervention for hydrocephalus in ELGANs with severe IVH over the past 12 years.
- Improved neonatal medical care, including reduced infection and bronchopulmonary dysplasia, may contribute to this reduction.
- Further multicenter prospective trials are needed to elucidate the influence of perinatal factors on the requirement for ventricular shunting.
Object:
Although survival for extremely low gestational age newborns (ELGANs) has improved in the past 3 decades, these infants remain prone to complications of prematurity, including intraventricular hemorrhage (IVH). The authors reviewed the outcomes for an entire cohort of ELGANs who suffered severe IVH at their institution during the past 12 years to gain a better understanding of the natural history of IVH and frequency of ventriculoperitoneal (VP) shunt placement in this population.
Methods:
Data from the neonatal ICU (NICU) database, neurosurgery operative log, and medical records were used to identify and follow up all ELGANs who suffered a severe IVH between 1997 and 2008. Trends between Period 1 (1997-2001) and Period 2 (2004-2008) were analyzed using the Pearson chi-square test.
Results:
Between 1997 and 2008, 1335 ELGANs were admitted to the NICU at the authors' institution within 3 days of birth, and 111 (8.3%) of these infants suffered a severe IVH. Survival to 2 years, incidence of severe IVH, neonatal risk factors (gestational age, birth weight, and incidence of necrotizing enterocolitis), ventriculomegaly on cranial ultrasonography, and use of serial lumbar punctures for symptomatic hydrocephalus were all stable. Infants from period 2 had a significantly lower incidence of bronchopulmonary dysplasia and sepsis than infants from Period 1 (both p < 0.001). All ELGANs with severe IVH and ventriculomegaly underwent long-term follow-up to identify shunt status at late follow-up. Twenty-two ELGANs (20%) with severe IVH required a temporary ventriculosubgaleal (VSG) shunt. Three infants with VSG shunts showed spontaneous hydrocephalus resolution, and 2 infants died of unrelated causes during the neonatal admission. The temporary VSG shunt complication rate was 20% (12% infection and 8% malfunction). Sixteen percent of all ELGANs (18 of 111) with severe IVH eventually required permanent ventricular shunt insertion. Six (35%) of 17 infants with a permanent VP shunt required at least 1 permanent shunt revision during the 1st year. The proportion of ELGANs with severe IVH who required a temporary VSG (35%) or permanent VP shunt (30%) during Period 1 decreased by more than 60% in Period 2 (10% [p = 0.005] and 8.3% [p = 0.009], respectively).
Conclusions:
The authors report for the first time a marked reduction over the past 12 years in the proportion of ELGANs with severe IVH who required surgical intervention for hydrocephalus. Using the NICU database, the authors were able to identify and follow all ELGANs with severe IVH and ventriculomegaly. They speculate that the reduction in ventricular shunt rate results from improved neonatal medical care, including reduced infection, improved bronchopulmonary dysplasia, and postnatal steroid avoidance, which may aid innate repair mechanisms. Multicenter prospective trials and detailed analyses of NICU parameters of neonatal well-being are needed to understand how perinatal factors influence the propensity to require ventricular shunting.