Gastrointestinal events with clopidogrel: a nationwide population-based cohort study
Related Experiment Videos
Erik Lerkevang Grove1, Morten Würtz, Peter Schwarz
1Department of Cardiology, Aarhus University Hospital, Skejby, Brendstrupgaardsvej 100, 8200 Aarhus, Denmark. erikgrove@dadlnet.dk

Insights
Clopidogrel use increases the risk of gastrointestinal (GI) complications, including bleeding events. This risk is dose-dependent, necessitating a careful balance between its cardiovascular benefits and potential GI harms.
Area of Science:
- Pharmacovigilance
- Gastroenterology
- Cardiology
Background:
- Clopidogrel is a widely used medication for preventing cardiovascular events.
- However, clopidogrel use has been associated with adverse gastrointestinal (GI) complications, notably bleeding.
Purpose of the Study:
- To investigate the association between clopidogrel treatment and the risk of adverse GI events.
- To assess whether this risk varies with the dosage of clopidogrel.
Main Methods:
- A nationwide population-based cohort study utilizing Danish administrative registries.
- Inclusion of 77,503 clopidogrel users and 232,510 matched controls from 1996 to 2008.
- Follow-up for gastritis, GI ulcer, or bleeding, with adjustments for comorbidity and medication use.
Main Results:
- Clopidogrel use was significantly associated with an increased risk of GI events across all doses, demonstrating a dose-response relationship.
- Adjusted odds ratios for GI events ranged from 1.34 to 1.91, with p-values < 0.01.
- The number needed to harm for 12 months of clopidogrel treatment ranged from 33 to 58 patients, depending on the dose.
Conclusions:
- The cardioprotective benefits of clopidogrel should be carefully considered alongside its elevated risk of GI events.
- The findings highlight the importance of risk-benefit assessment in clopidogrel therapy, particularly concerning GI safety.
Background:
Clopidogrel prevents cardiovascular events, but has been linked with adverse gastrointestinal (GI) complications, particularly bleeding events.
Objective:
We aimed to investigate the risk of adverse GI events in patients treated with clopidogrel.
Design:
A nationwide population-based cohort study based on linkage of three administrative registries in Denmark.
Participants:
All individuals who redeemed at least one prescription of clopidogrel from 1996 to 2008 were included as exposed subjects (n = 77,503). For each exposed subject, three matched controls were randomly selected from the background population (n = 232,510).
Analyses:
Follow-up began on January 1, 1996, and was censored on December 31, 2007, or if patients emigrated or died. The study endpoint was the occurrence of any gastritis, GI ulcer or bleeding. Analyses were adjusted for comorbidity and medication.
Results:
Regardless of dose, adjusted odds ratios associating clopidogrel use with the study endpoint were statistically significant and followed a dose-response pattern. The crude absolute risk of GI events were: never users: 2.2 %; <0.1 defined daily dose (DDD) of clopidogrel per day: 7.1 %; 0.1-0.39 DDD: 6.0 %; 0.4-0.79 DDD: 5.7 %; ≥0.80 DDD: 4.4 %. Adjusted odds ratios were: <0.1 DDD: 1.34, 95 % CI: 1.26-1.42; 0.1-0.39 DDD: 1.58, 95 % CI: 1.48-1.68; 0.4-0.79 DDD: 1.91, 95 % CI: 1.77-2.06; ≥0.80 DDD: 1.77, 95 % CI: 1.66-1.89, all p-values < 0.01. Depending on the dose, numbers needed to harm ranged from 58 to 33 patients receiving 12 months of clopidogrel treatment.
Conclusions:
The well-known cardioprotective effect of clopidogrel must be carefully weighed against an increased risk of GI events.
Related Concept Videos
 01:25
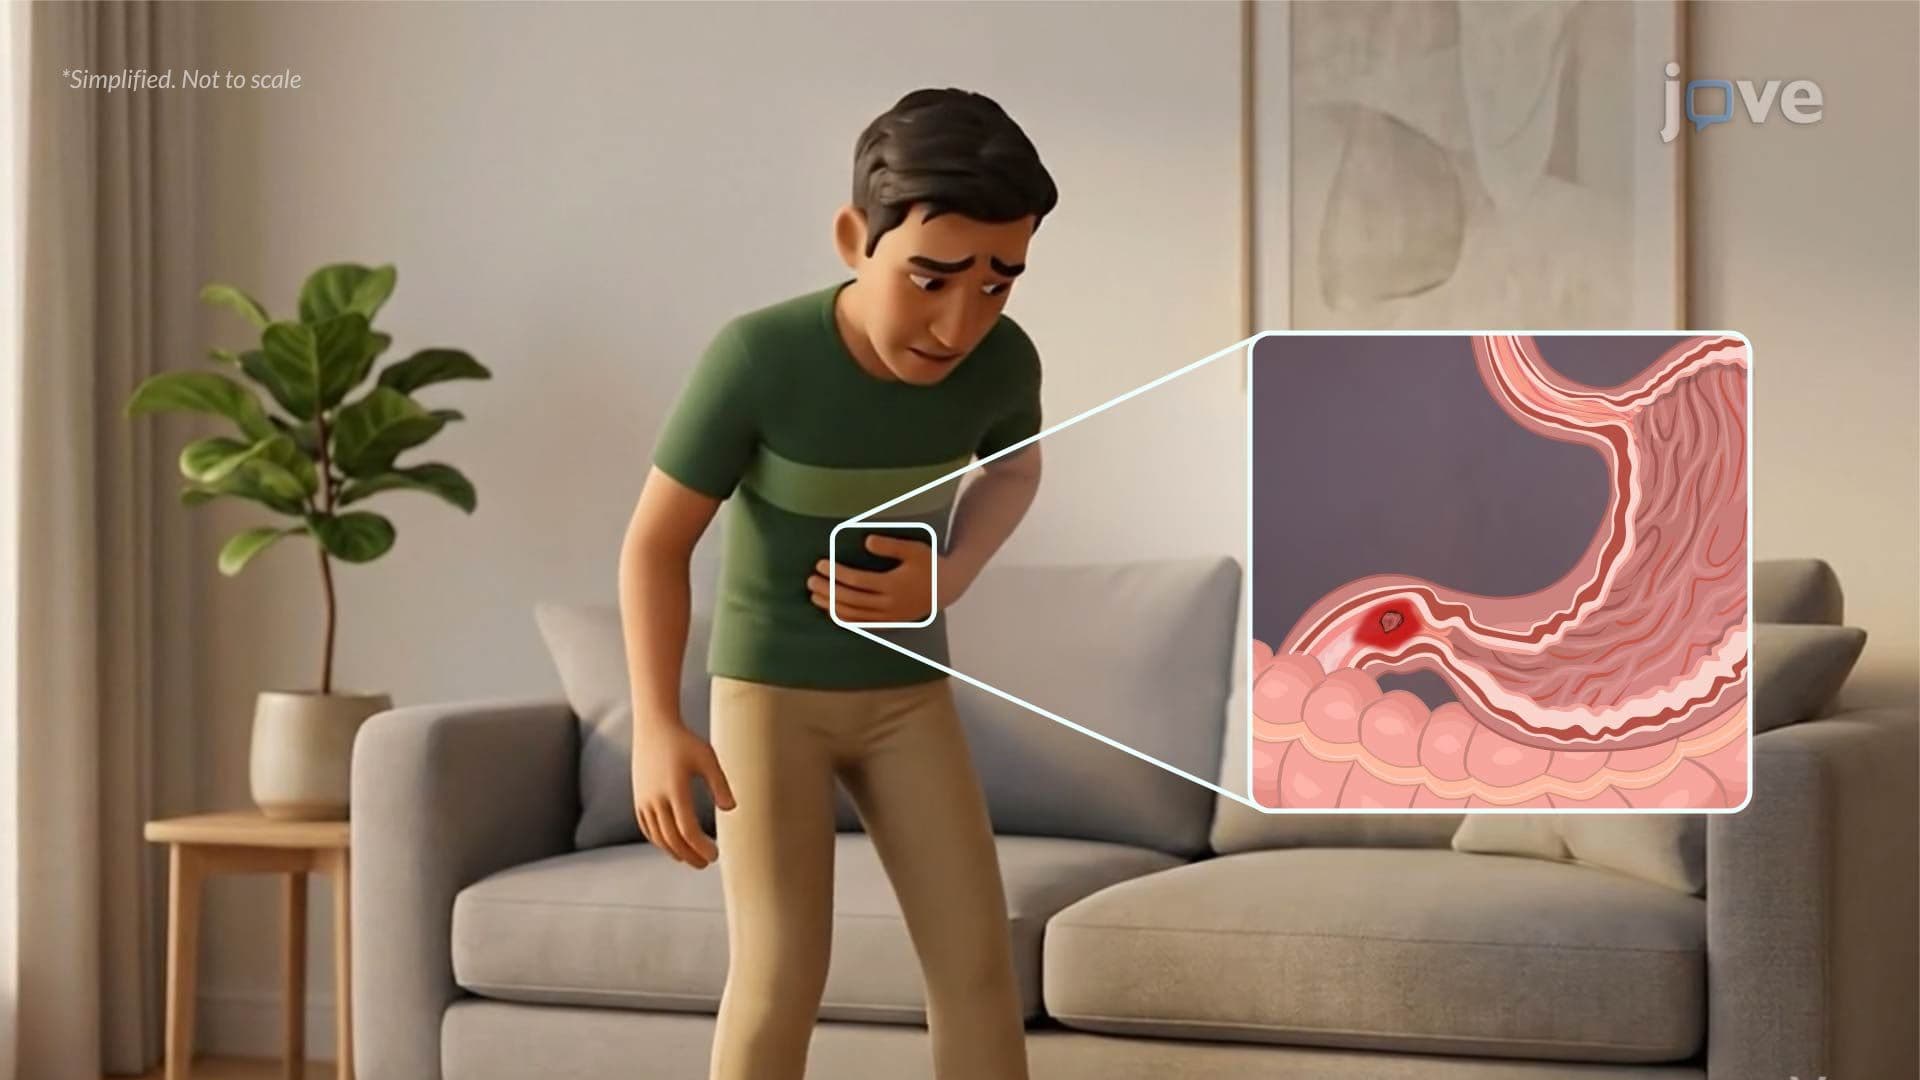
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:25
Peptic Ulcer Disease I: Introduction
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...