Related Experiment Video
Updated: May 18, 2026


Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
New reference equations to improve interpretation of infant lung function
The Thanh Diem Nguyen1, Ah-Fong Hoo, Sooky Lum
1Portex Respiratory Unit, UCL Institute of Child Health and Great Ormond Street Hospital for Children NHS Foundation Trust, London, UK. t.nguyen@ucl.ac.uk

Insights
Infant pulmonary function tests (IPFTs) should not be reported as size-corrected ratios due to growth-related bias. Instead, use established reference equations for accurate interpretation of lung function in infants.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Biostatistics
Background:
- Infant pulmonary function tests (IPFTs) are increasingly used in clinical and research settings.
- Accurate interpretation of IPFT results is crucial for diagnosis and management.
- Standardization of IPFT interpretation is needed to avoid bias.
Purpose of the Study:
- To assess bias from normalizing infant pulmonary function (IPF) by body size ratios.
- To develop reference ranges for tidal breathing, respiratory mechanics (compliance [Crs], resistance [Rrs]), and plethysmographic functional residual capacity (FRCp).
- To establish reference ranges for white infants up to 2 years of age.
Main Methods:
- IPFTs were performed using the Jaeger BabyBody system under standardized protocols.
- Multilevel modeling was employed to create reference equations.
- Equations were adjusted for body size, age, and sex where applicable.
Main Results:
- Lung function-to-body length ratios showed significant changes with growth, making them unsuitable for outcome measures.
- Tidal volume and Crs ratios to body weight were relatively constant, but FRCp ratios were not.
- A strong inverse relationship between lung function/body weight and weight z-score was observed, potentially distorting results in growth-restricted infants.
- Crown-heel length was the most significant predictor of IPF.
Conclusions:
- Discourage the use of size-corrected ratios for reporting IPF; rely on appropriate reference equations.
- The derived reference equations are applicable to white infants and young children up to 2 years old, tested with the specified equipment.
- Further research is needed to confirm applicability to diverse ethnic backgrounds and different testing equipment.
Rationale:
With increasing use of infant pulmonary function tests (IPFTs) in both clinical and research studies, appropriate interpretation of results is essential.
Objectives:
To investigate the potential bias associated with "normalising" IPF by expressing results as a ratio of body size and to develop reference ranges for tidal breathing parameters, passive respiratory mechanics (compliance [Crs] and resistance [Rrs]) and plethysmographic functional residual capacity (FRCp ) for white infants during the first 2 years of life.
Methods:
IPFTs were measured using the Jaeger BabyBody system and standardized protocols. Reference equations, adjusted for body size, age, and sex where appropriate, were created using multilevel modeling.
Results:
The ratio of lung function to body length changes markedly with growth, thereby precluding its use for any outcome. While the ratio of tidal volume and Crs to body weight remained relatively constant with growth, this was not the case for FRCp . Even in healthy infants, a strong inverse relationship was observed between lung function/body weight and weight z-score which could distort interpretation of results in growth-restricted infants with lung disease, such as cystic fibrosis. Reference equations were derived from 153 healthy white infants on 232 test occasions (median age 35.5 weeks [range: 2.6-104.7]). Crown-heel length was the strongest predictor of IPF.
Conclusions:
When reporting IPF, use of size-corrected ratios should be discouraged, with interpretation instead based on appropriate reference equations. The current equations are applicable to white infants and young children up to 2 years of age, studied using the same commercially available equipment. The extent to which these equations are applicable to infants and young children of other ethnic backgrounds or who are tested with different equipment needs to be established.


Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:15
Respiratory Volumes
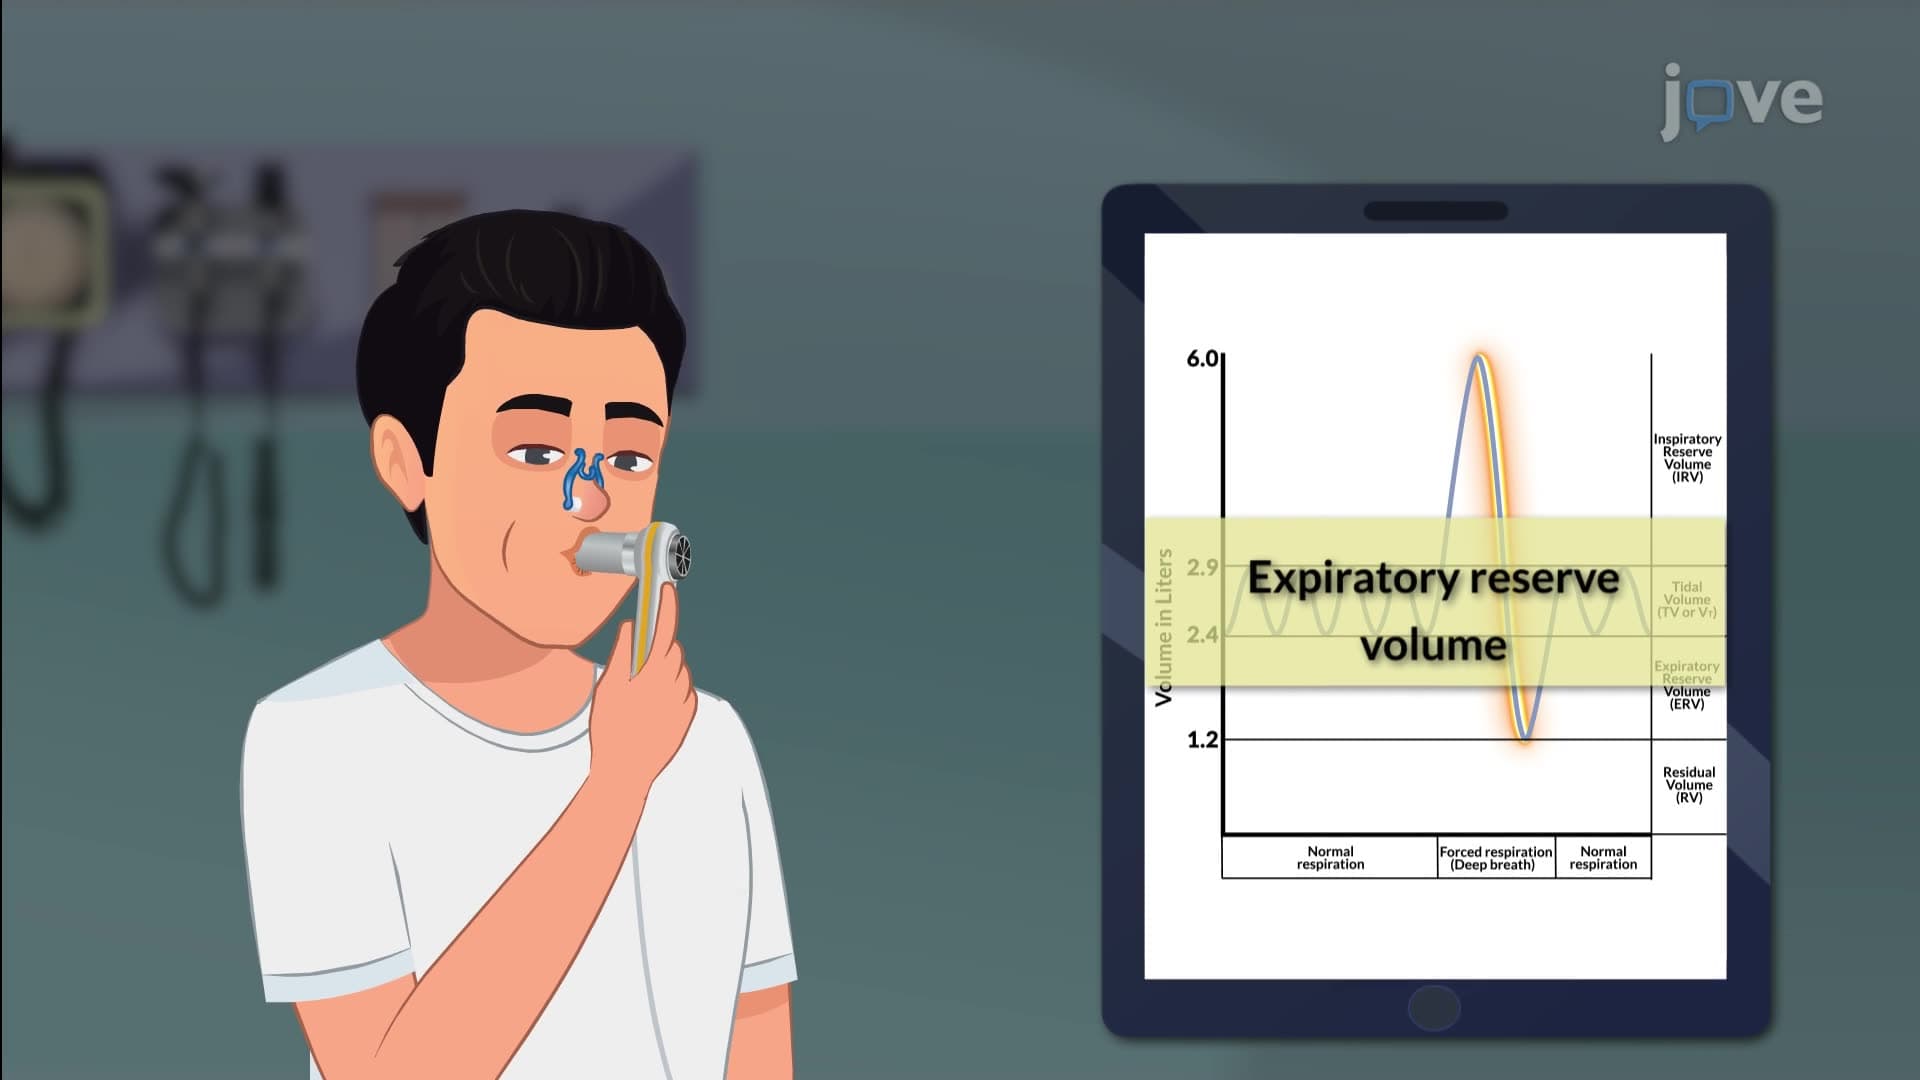
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Respiratory Volumes and Capacities
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: