Related Experiment Video
Updated: May 18, 2026

Anesthesia and Intubation of Preadolescent Mouse Pups for Cardiothoracic Surgery
Published on: June 2, 2022
The effective effect-site propofol concentration for induction and intubation with two pharmacokinetic models in
Ghislaine C Echevarría1, María F Elgueta, María T Donoso
1Departamento de Anestesiología, Escuela de Medicina, Pontificia Universidad Católica de Chile, Santiago, Chile.

Background:
Most pharmacokinetic (PK) models used for propofol administration are based on studies in normal-weight patients. Extrapolation of these models for morbidly obese patients is controversial. Using 2 PK models and a target-controlled infusion system, we determined the predicted propofol effect-site concentration (Ce) needed for induction of anesthesia in morbidly obese subjects using total body weight.
Methods:
Sixty-six morbidly obese subjects from 18 to 50 years of age were randomized to receive propofol to reach and maintain a predetermined propofol Ce, based on the PK models of either Marsh or Schnider. All patients were monitored with a Bispectral Index electroencephalographic monitor. Fentanyl 3 μg/kg total body weight was administered before starting the propofol infusion. After loss of consciousness, vecuronium was administered to facilitate endotracheal intubation. Groups of 6 patients each received propofol at a different, predetermined target propofol Ce. An "effective Ce" (ECe) was defined as the propofol Ce that provided adequate hypnosis (Bispectral Index <60) during the complete induction period (45 seconds after reaching the predetermined target Ce until 5 minutes after tracheal intubation). Heart rate and arterial blood pressure were measured every 1 minute throughout the study period. Probit regression analysis was performed to calculate the effective propofol Ce values to induce hypnosis in 50% (ECe(50)) and 95% (ECe(95)) of patients with 95% confidence intervals (CIs).
Results:
Patient characteristics were similar between models and across the propofol target concentration groups. The ECe(50) of propofol was 3.4 μg/mL (95% CI: 2.9, 3.7 μg/mL) with the Marsh model and 4.5 μg/mL (95% CI: 4.1, 4.8 μg/mL) with the Schnider model (P < 0.001). The ECe(95) values were 4.2 μg/mL (95% CI: 3.8, 6.2 μg/mL) and 5.5 μg/mL (95% CI: 5.0, 7.2 μg/mL) with Marsh and Schnider models, respectively. At the ECe(95), hemodynamic effects were similar with the 2 PK models.
Conclusion:
Different propofol target concentrations for each PK model must be used for induction when using total body weight in morbidly obese patients.
Related Concept Videos
 01:21
Drug Dosing: Obese Patients
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:15
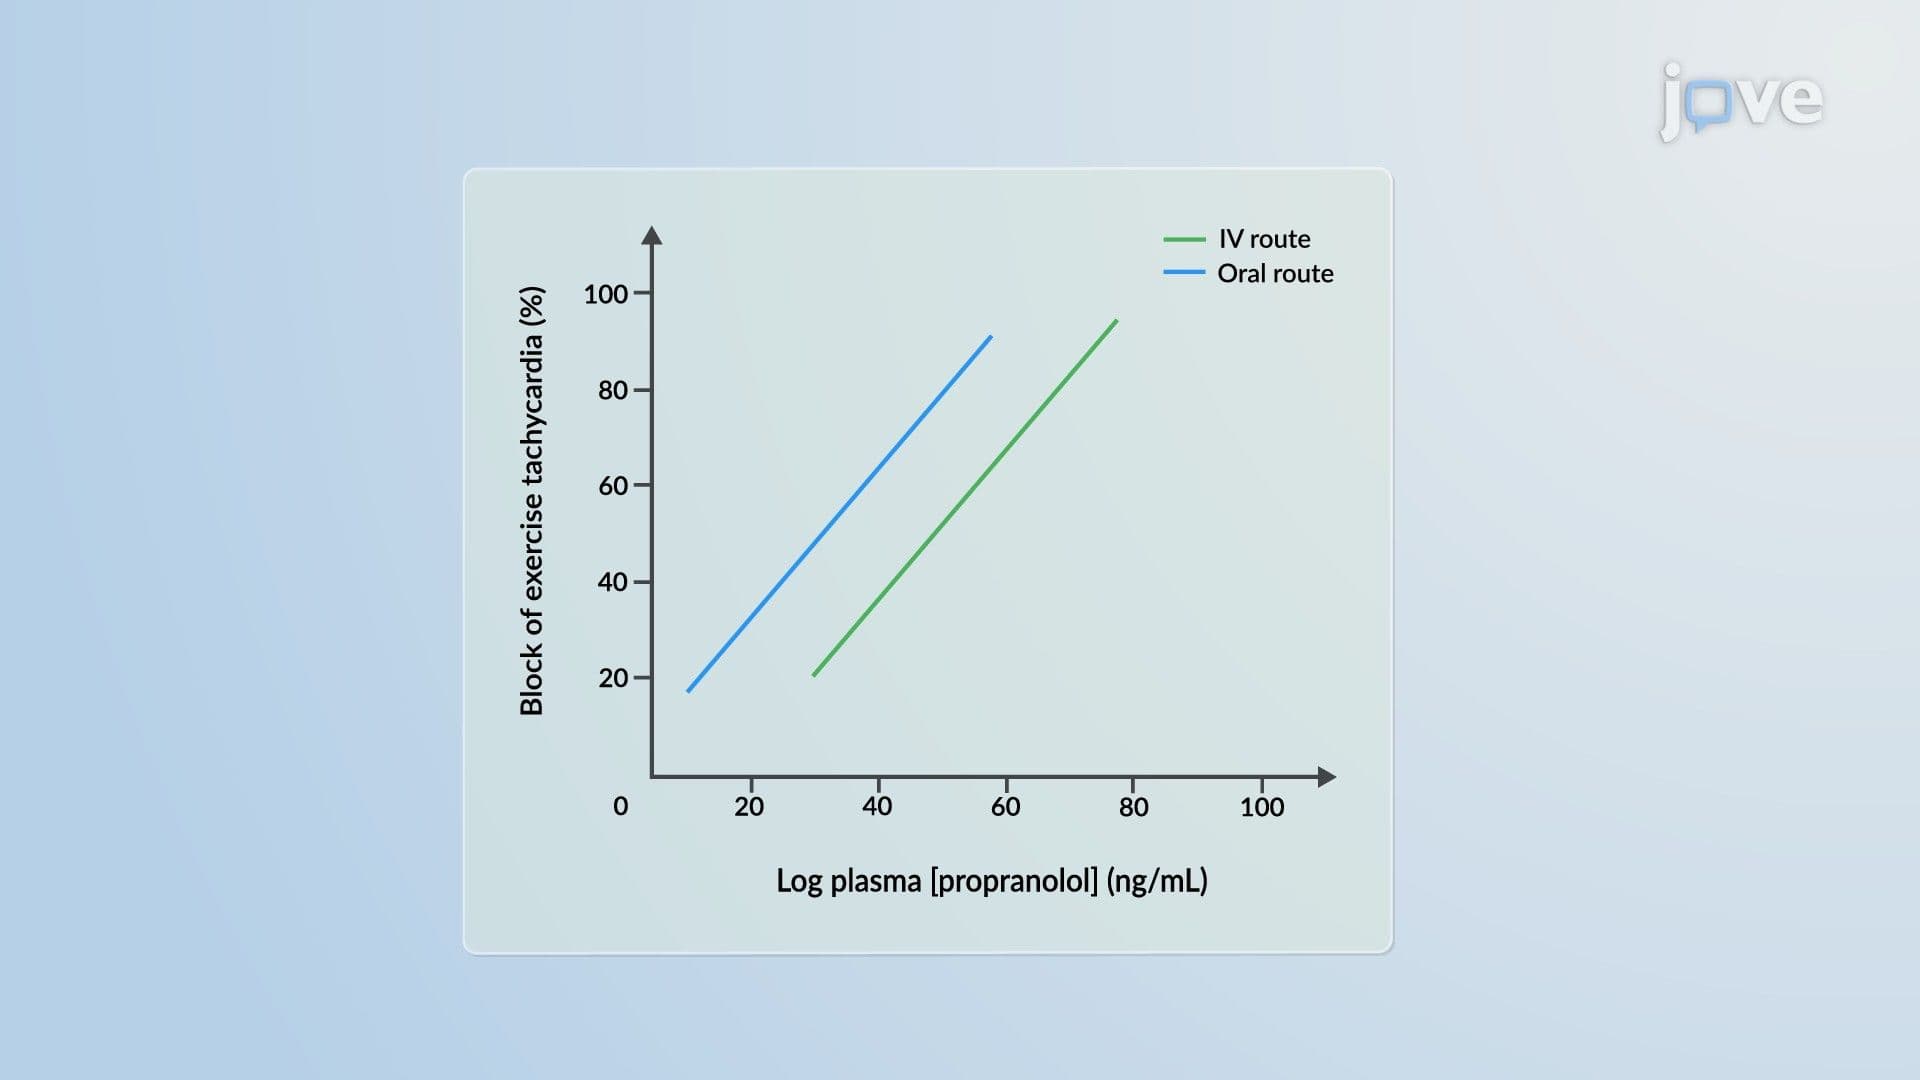
Pharmacodynamic Models: Logarithmic Concentration–Effect Model
 01:29
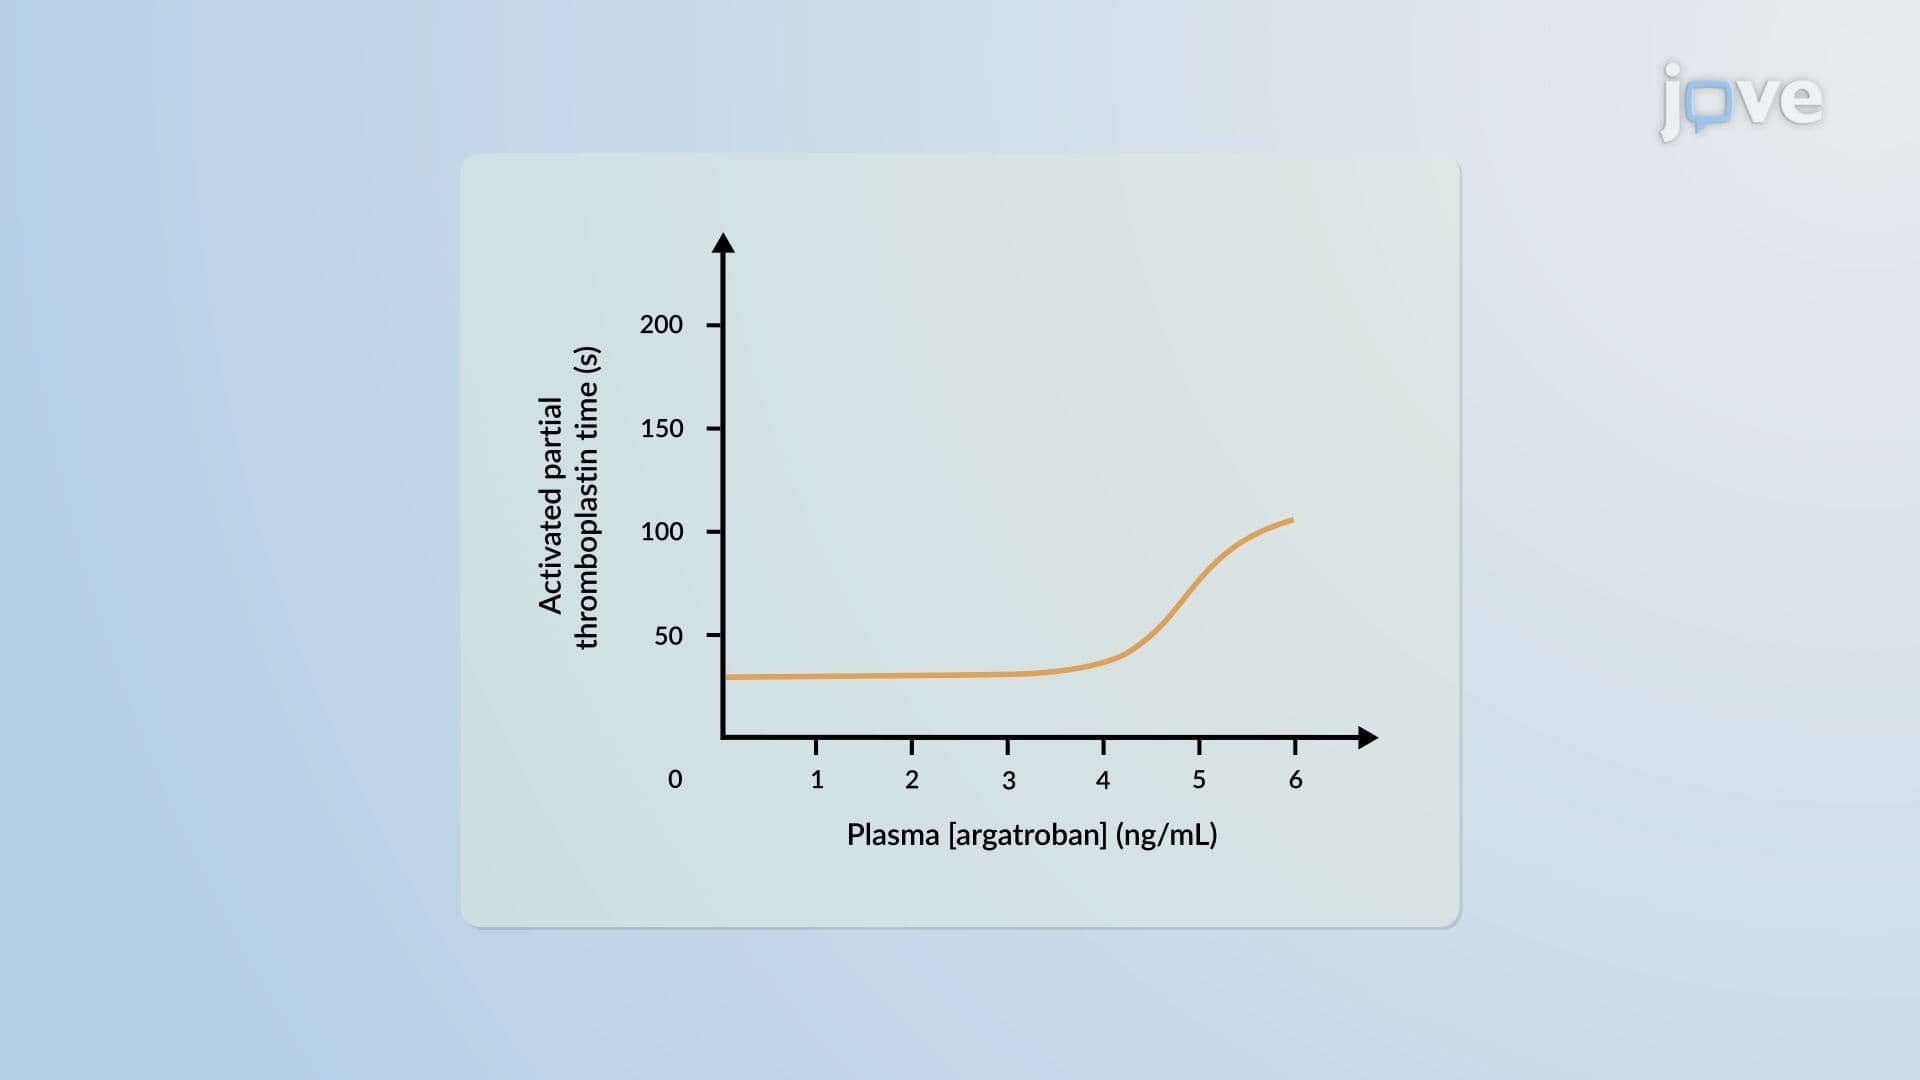
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions