Related Experiment Video
Updated: May 18, 2026
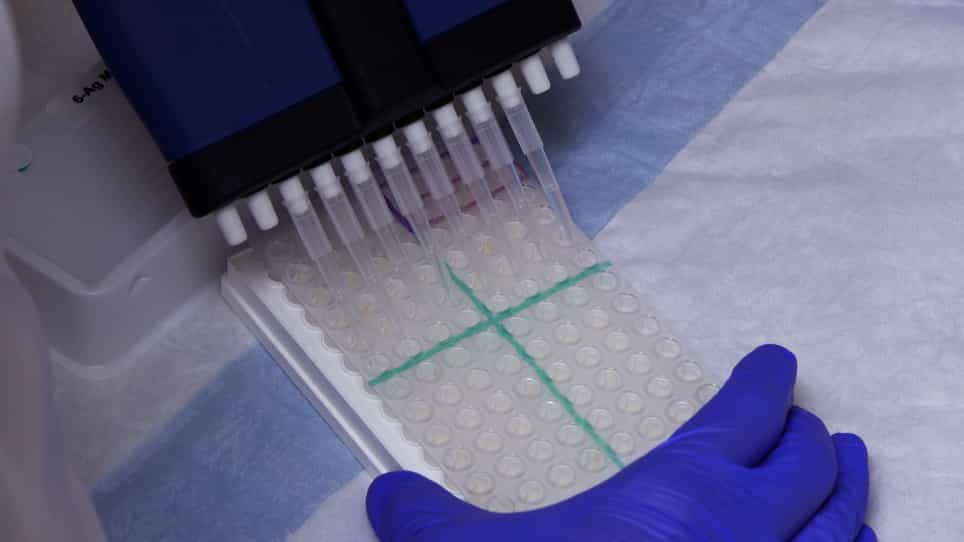

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Metabolic outcomes in young children with type 1 diabetes differ between treatment centers: the Hvidoere Study in
Carine E de Beaufort1, Karin Lange, Peter G F Swift
1Pediatric Clinic, Centre Hospitalier de Luxembourg, Luxembourg, GD de Luxembourg. debeaufort.carine@chl.lu

Insights
Center differences significantly impact glycemic control in children under 11 with type 1 diabetes. Center effectiveness in treatment strategies, not insulin regimens, is key to outcomes.
Area of Science:
- Pediatric Endocrinology
- Metabolic Disorders
- Clinical Research
Background:
- Glycemic control in type 1 diabetes mellitus (T1DM) is crucial for preventing long-term complications.
- Variability in clinical outcomes across pediatric centers managing T1DM suggests potential differences in care quality or approach.
Purpose of the Study:
- To determine if significant variations in glycemic control exist among pediatric centers treating prepubertal children (<11 years) with T1DM.
- To identify factors contributing to these center-specific differences in metabolic outcomes.
Main Methods:
- A cross-sectional study involving 1133 children (<11 years) with T1DM duration of at least 12 months across 18 international pediatric centers.
- Data collected included clinical characteristics, insulin regimens, diabetic ketoacidosis (DKA), severe hypoglycemia, language difficulties, and comorbidities.
- Centralized Hemoglobin A1c (HbA1c) measurement using liquid chromatography; statistical analysis to compare center outcomes.
Main Results:
- Significant differences were observed between centers in HbA1c levels (overall mean 8.0 ± 1.0%) and the frequency of severe hypoglycemia.
- Center differences in HbA1c persisted even after adjusting for insulin regimens, indicating other factors are influential.
- Language difficulties were negatively associated with HbA1c, and blood glucose monitoring frequency showed a weak negative correlation.
Conclusions:
- Substantial center-specific variations in metabolic outcomes exist for prepubertal children with T1DM, independent of patient demographics or diabetes duration.
- While insulin regimens are related to HbA1c, they do not account for the observed center differences, highlighting the importance of center-specific treatment strategy effectiveness.
- The incidence of severe hypoglycemia is lower in this younger cohort compared to adolescents, despite achieving better glycemic control.
Objective:
To investigate whether center differences in glycemic control are present in prepubertal children <11 yr with type 1 diabetes mellitus.
Research Design And Methods:
This cross-sectional study involved 18 pediatric centers worldwide. All children, <11 y with a diabetes duration ≥12 months were invited to participate. Case Record Forms included information on clinical characteristics, insulin regimens, diabetic ketoacidosis (DKA), severe hypoglycemia, language difficulties, and comorbidities. Hemoglobin A1c (HbA1c) was measured centrally by liquid chromatography (DCCT aligned, range: 4.4-6.3%; IFFC: 25-45 mmol/mol).
Results:
A total of 1133 children participated (mean age: 8.0 ± 2.1 y; females: 47.5%, mean diabetes duration: 3.8 ± 2.1 y). HbA1c (overall mean: 8.0 ± 1.0%; range: 7.3-8.9%) and severe hypoglycemia frequency (mean 21.7 events per 100 patient-years), but not DKA, differed significantly between centers (p < 0.001 resp. p = 0.179). Language difficulties showed a negative relationship with HbA1c (8.3 ± 1.2% vs. 8.0 ± 1.0%; p = 0.036). Frequency of blood glucose monitoring demonstrated a significant but weak association with HbA1c (r = -0.17; p < 0.0001). Although significant different HbA1c levels were obtained with diverse insulin regimens (range: 7.3-8.5%; p < 0.001), center differences remained after adjusting for insulin regimen (p < 0.001). Differences between insulin regimens were no longer significant after adjusting for center effect (p = 0.199).
Conclusions:
Center differences in metabolic outcomes are present in children <11 yr, irrespective of diabetes duration, age, or gender. The incidence of severe hypoglycemia is lower than in adolescents despite achieving better glycemic control. Insulin regimens show a significant relationship with HbA1c but do not explain center differences. Each center's effectiveness in using specific treatment strategies remains the key factor for outcome.
Related Concept Videos
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:19
Type I Diabetes III: Clinical Manifestations
 01:26
Type I Diabetes II: Pathophysiology
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:12
Type I Diabetes I: Introduction
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis