Related Experiment Video
Updated: May 18, 2026

Targeting the Corticospinal Tract in Neonatal Rats with a Double-Viral Vector using Combined Brain and Spine Surgery
Published on: June 30, 2021
Contribution of the corticospinal tract to motor impairment in spina bifida
Niels Geerdink1, Inge Cuppen, Jan Rotteveel
1Department of Pediatric Neurology, Radboud University Nijmegen Medical Center, Nijmegen, The Netherlands. n.geerdink@cukz.umcn.nl

Insights
Upper motor neuron dysfunction significantly contributes to motor impairment in children with spina bifida, more than previously recognized. This study clarifies the roles of both upper and lower motor neuron deficits in pediatric spina bifida.
Area of Science:
- Neurology
- Pediatric Medicine
- Biomedical Engineering
Background:
- Spina bifida is a complex congenital condition affecting motor function.
- The precise contributions of upper and lower motor neuron dysfunction to motor impairment in pediatric spina bifida are not fully understood.
- Accurate assessment is crucial for targeted interventions.
Purpose of the Study:
- To differentiate and quantify the roles of upper and lower motor neuron dysfunction in children with spina bifida.
- To correlate neurophysiological findings with motor impairment severity.
- To improve understanding of the pathophysiology of motor deficits in spina bifida.
Main Methods:
- Recruited 42 children with spina bifida and 36 controls.
- Assessed motor impairment severity using established scales.
- Recorded motor evoked potentials (MEPs) via transcranial and lumbosacral magnetic stimulation.
- Measured compound muscle action potentials (CMAPs) using electric nerve stimulation.
Main Results:
- Severely impaired children showed reduced CMAP and lumbosacral MEP areas, indicating lower motor neuron involvement.
- Children with spina bifida exhibited smaller transcranial MEP areas and longer central motor conduction times, pointing to upper motor neuron dysfunction.
- Upper motor neuron dysfunction severity correlated with overall motor impairment.
Conclusions:
- Upper motor neuron dysfunction plays a more substantial role in motor impairment in children with spina bifida than clinically apparent.
- Neurophysiological assessments provide critical insights beyond standard neurological examination.
- Findings may inform future therapeutic strategies for pediatric spina bifida.
Abstract:
We aimed to disentangle the proportional contributions of upper and lower motor neuron dysfunction to motor impairment in children with spina bifida. We enrolled 42 children (mean age, 11.2 years; standard deviation, 2.8 years) with spina bifida and 36 control children (mean age, 11.4 years; standard deviation, 2.6 years). Motor impairment was graded to severity scales in children with spina bifida. We recorded motor evoked potentials after transcranial and lumbosacral magnetic stimulation and compound muscle action potentials after electric nerve stimulation. Regarding lower motor neuron function, severely impaired children with spina bifida demonstrated smaller compound muscle action potential areas and lumbosacral motor evoked potential areas than control children; mildly impaired children hardly differed from control children. Compound muscle action potential latencies and lumbosacral motor evoked potential latencies did not differ between children with spina bifida and control children. Regarding upper motor neuron function, children with spina bifida demonstrated smaller transcranial motor evoked potential areas and longer central motor conduction times than control children. The smallest motor evoked potential areas and longest central motor conduction times were observed in severely impaired children. In children with spina bifida, the contribution of upper motor neuron dysfunction to motor impairment is more considerable than expected from clinical neurologic examination.
Related Concept Videos
 01:22
Indirect Motor Pathways
The vestibulospinal tract originates in the vestibular nuclei of the brainstem. The vestibular system detects changes in...
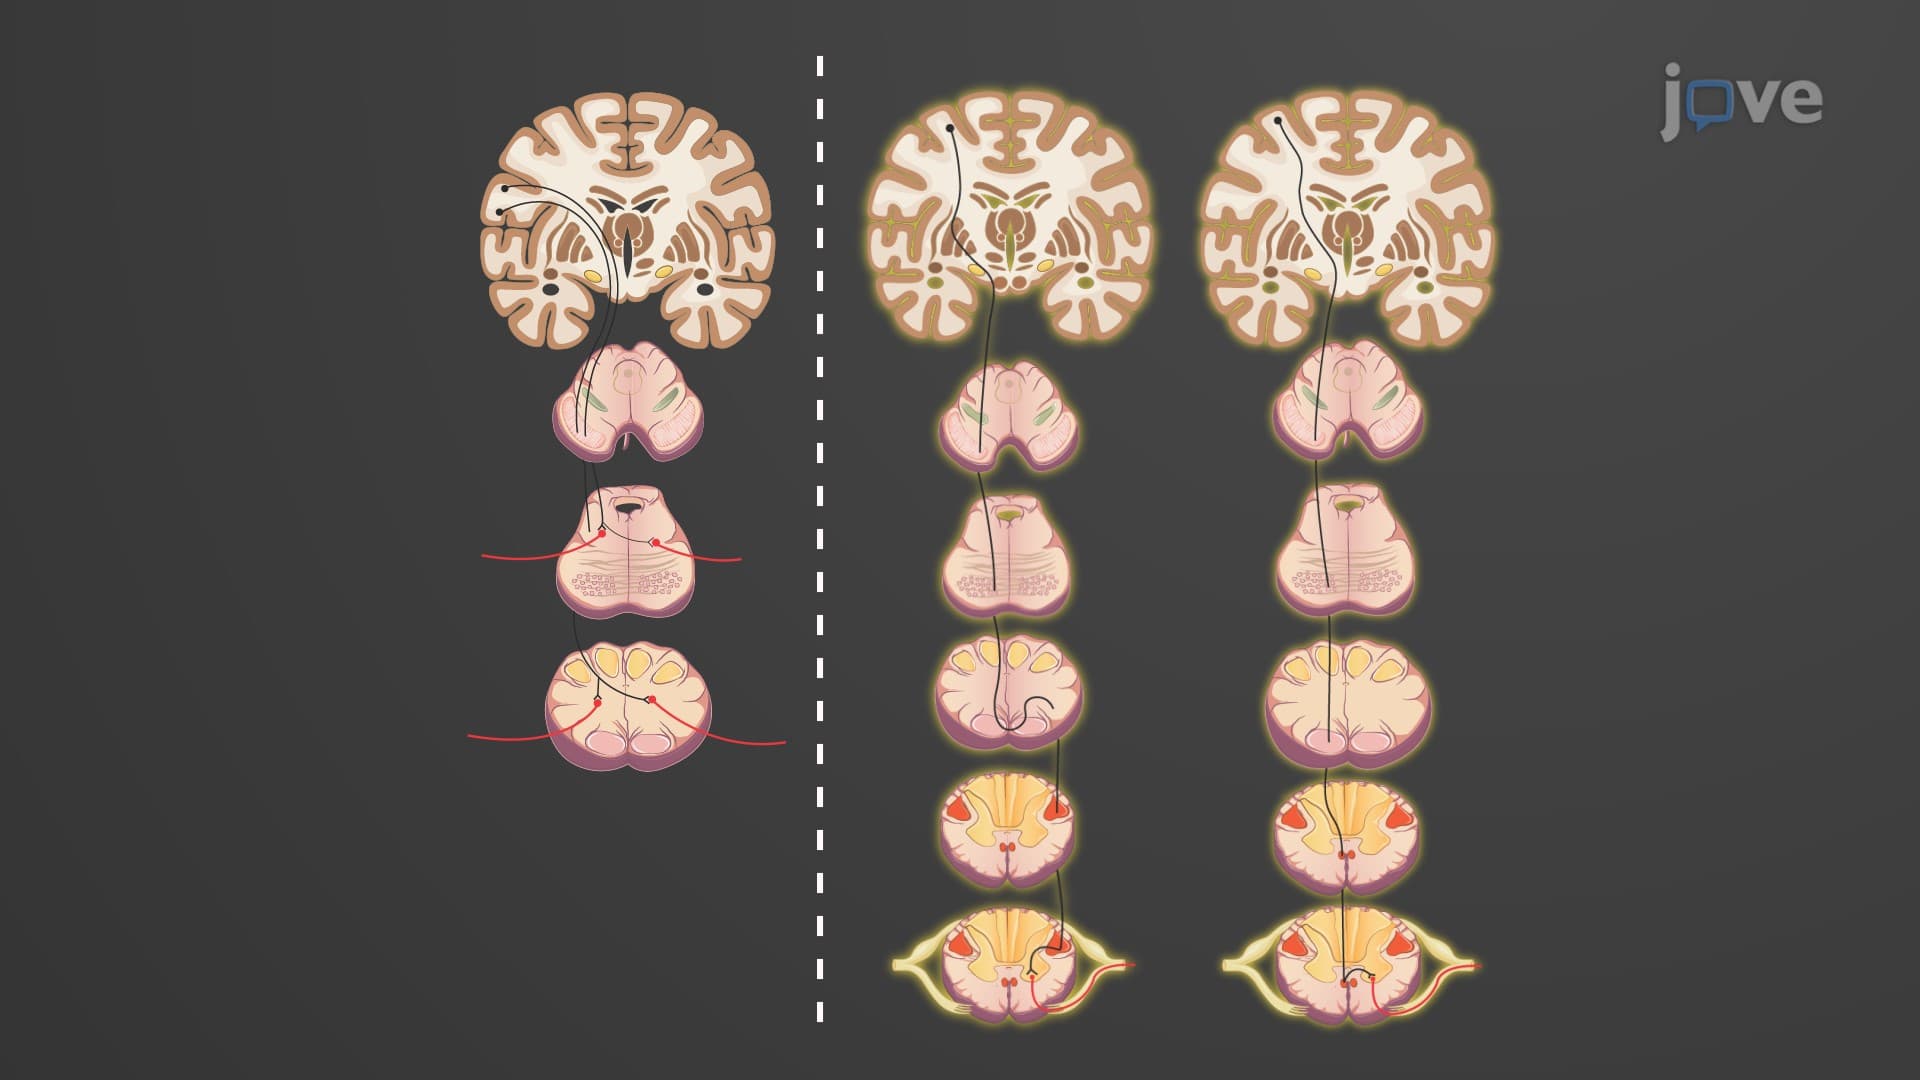 01:11
Direct Motor Pathways
The corticospinal tract is responsible for the voluntary movement of the limbs and trunk. It originates in the cerebral cortex of the brain and descends through the cerebrum's internal capsule and the...
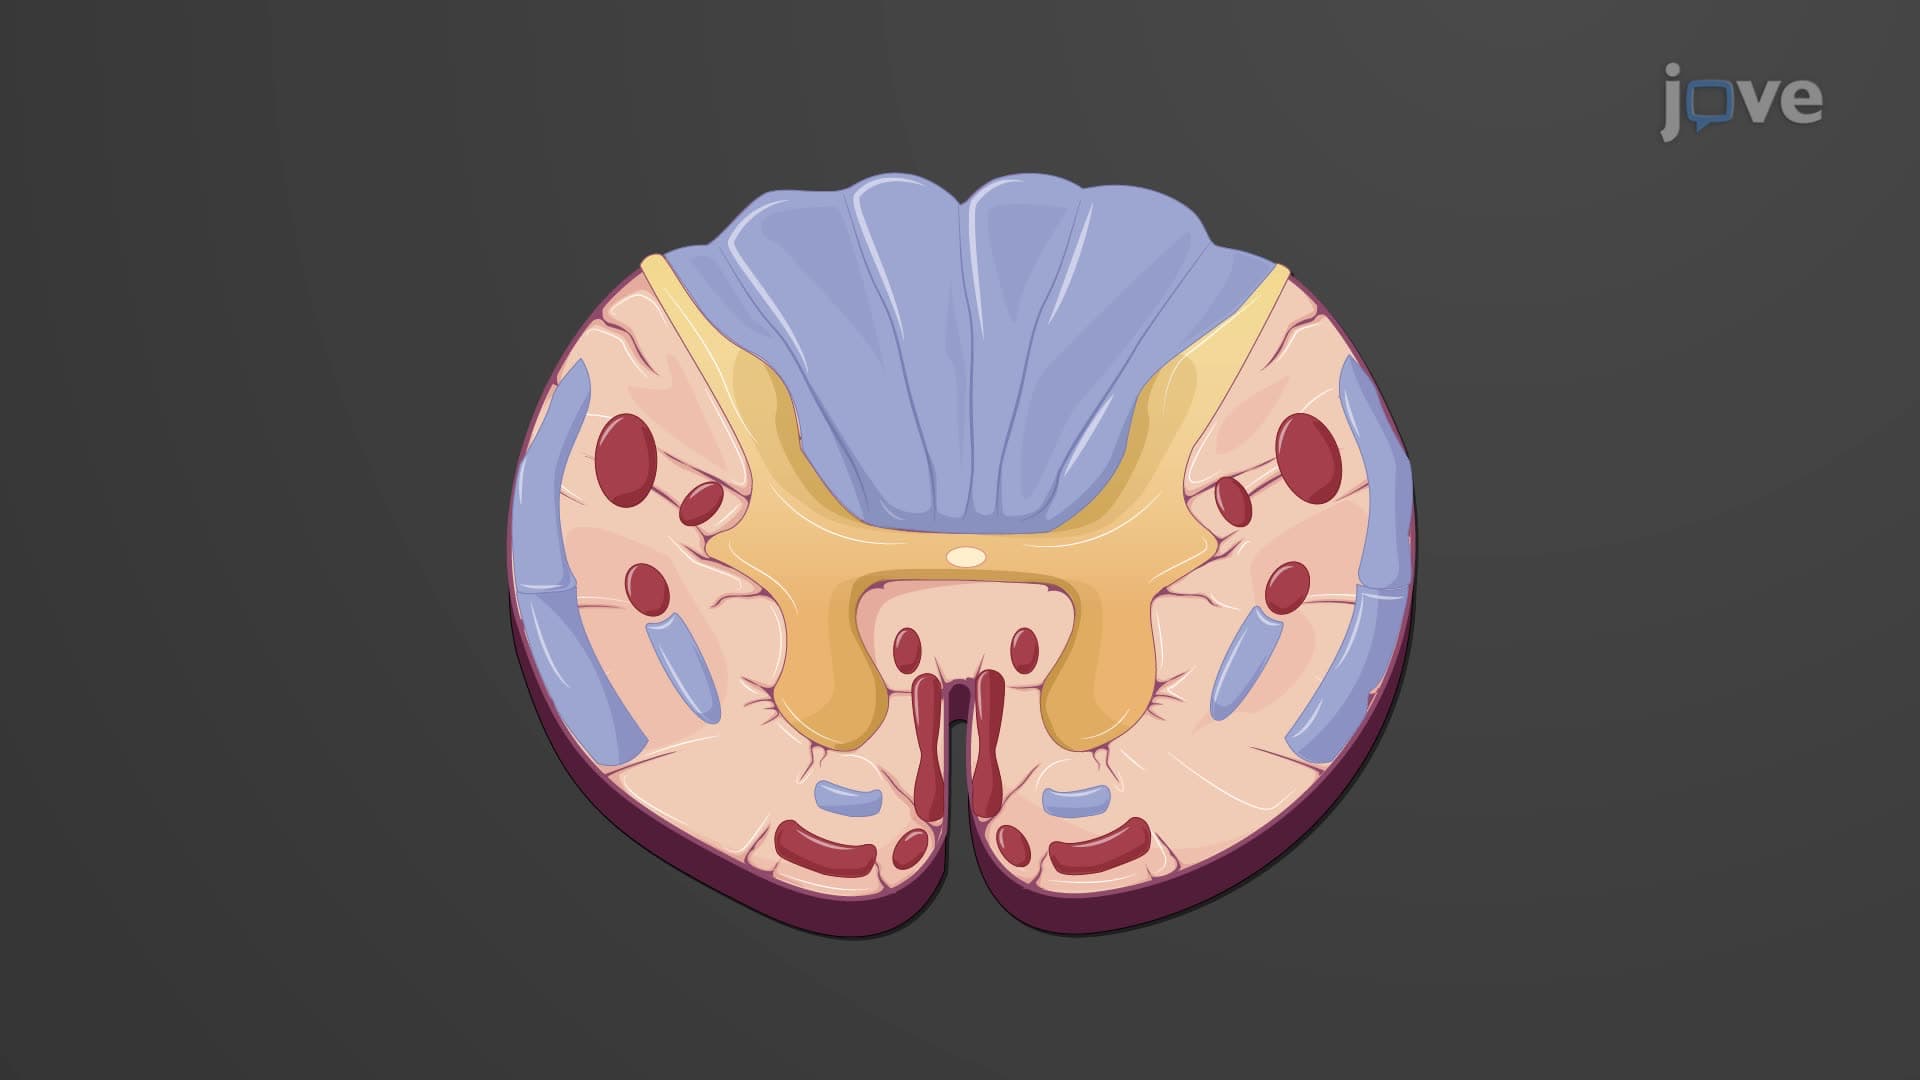 01:16
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:28
Major Somatic Sensory Pathways