Related Experiment Video
Updated: May 18, 2026

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Normal values for respiratory muscle strength in healthy preschoolers and school children
João Paulo Heinzmann-Filho1, Paula Cristina Vasconcellos Vidal, Marcus Herbert Jones
1Graduate Program of Pediatrics and Children's Health, Pontifícia Universidade Católica do Rio Grande do Sul-PUCRS, Porto Alegre, Rio Grande do Sul, Brazil.

Insights
Reference values for respiratory muscle strength in children aged 3-12 were established. Height and weight best predict maximal inspiratory pressure (MIP), while age and weight predict maximal expiratory pressure (MEP).
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Biometrics
Background:
- Establishing normative data for respiratory muscle strength is crucial for assessing pediatric lung health.
- Previous research has not comprehensively defined reference values for maximal inspiratory pressure (MIP) and maximal expiratory pressure (MEP) in healthy children across a wide age range.
- Understanding factors influencing respiratory muscle strength is essential for early detection of potential respiratory impairments.
Purpose of the Study:
- To determine reference values for respiratory muscle strength in healthy children aged three to twelve years.
- To identify key anthropometric and demographic predictors of respiratory muscle strength in this pediatric population.
- To provide a basis for clinical assessment and research in pediatric respiratory function.
Main Methods:
- A cohort of 171 healthy children aged 3-12 years was recruited from three schools.
- Respiratory muscle strength (MIP and MEP) was assessed by a single examiner following standardized pulmonary function test guidelines.
- Multiple linear regression analysis was employed to identify predictors of MIP and MEP, with height, weight, and age as covariates.
Main Results:
- Height and weight were identified as the strongest predictors for MIP in both sexes (R² = 46-58%).
- Age and weight were the best predictors for MEP (R² = 46-58%).
- Intraclass correlation coefficients confirmed excellent reproducibility of the respiratory pressure measurements in a subgroup.
Conclusions:
- Respiratory muscle strength in healthy preschool and school-aged children is significantly influenced by age, height, and weight.
- The established reference values and predictive models provide valuable tools for pediatric respiratory health assessments.
- This study highlights the importance of anthropometric measures in understanding variations in respiratory muscle function during childhood.
Aim:
To generate reference values for respiratory muscle strength in healthy children aged three to twelve years.
Methods:
Participants were recruited from three schools and selected after a respiratory disease questionnaire analysis and written informed consent by parents or guardians. All participants included in the study had normal spirometry, height and weight were measured on the same day. Respiratory muscle strength was evaluated by a single examiner following the guidelines for pulmonary function tests. The association between MIP and MEP values with the potential predictive variables was analyzed using a multiple linear regression model.
Results:
A total of 171 participants were selected and distributed evenly by age. The age, height, weight and forced vital capacity showed moderate to strong correlations with both respiratory pressures. However, the regression model showed that height and weight were the best variables to predict MIP in both sexes, and age and weight to predict MEP. The power of prediction (R²) ranged from 46 to 58%. The intraclass correlation coefficient was used in a subgroup and demonstrated excellent reproducibility between tests.
Conclusion:
The results of this study demonstrate that the behavior of respiratory muscle strength in healthy preschool and school children can be explained by age, height and weight.

Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:15
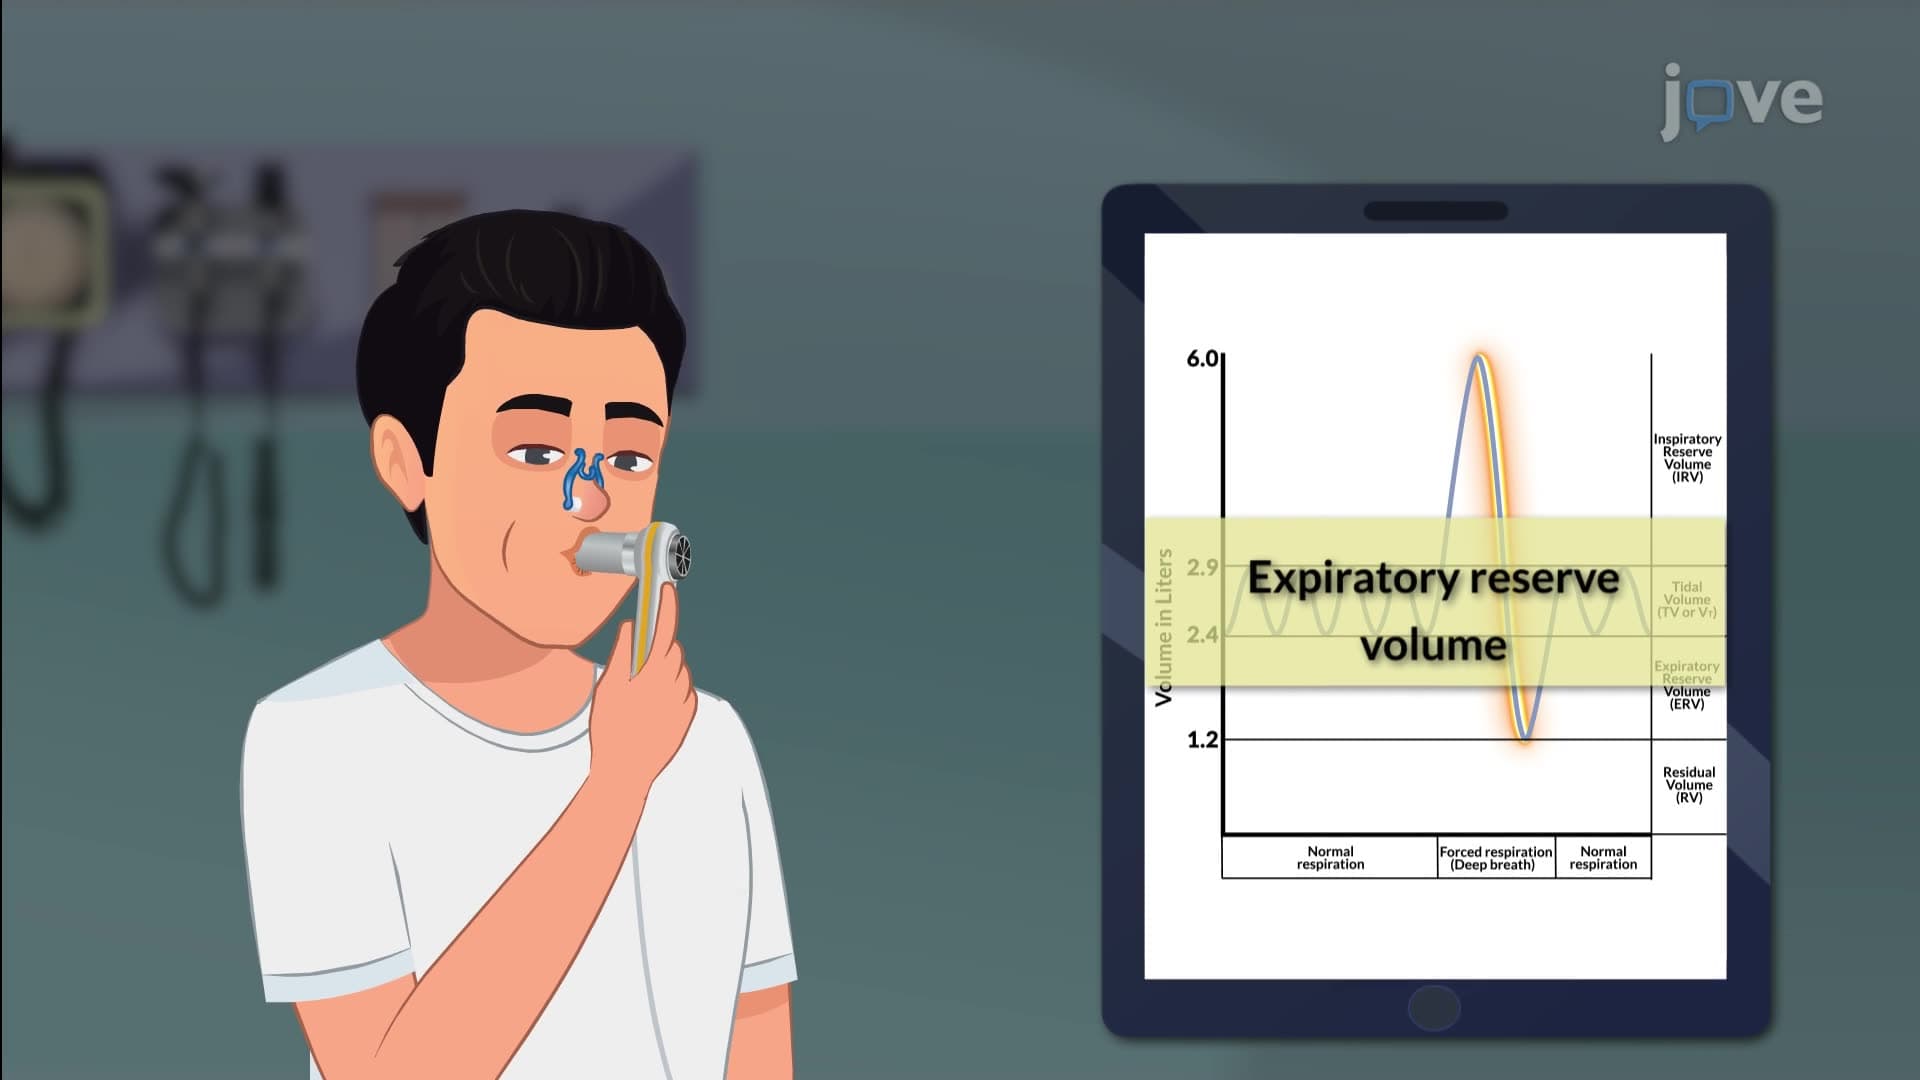
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...