
Prognostic value of 12-lead electrocardiogram and peak troponin I level after vascular surgery
Santiago Garcia1, Nicholas Marston, Yader Sandoval
1Department of Medicine, Division of Cardiology, Minneapolis VA Medical Center and University of Minnesota, Minneapolis, MN 55417, USA. garci205@umn.edu

Insights
Electrocardiographic (ECG) changes do not predict long-term mortality after vascular surgery when cardiac troponin (cTn) levels are elevated. Routine cTn surveillance aids in detecting cardiac events and stratifying risk post-surgery.
Area of Science:
- Cardiology
- Vascular Surgery
- Biomarker Analysis
Background:
- Postoperative cardiac events are a significant concern in vascular surgery patients.
- Risk stratification is crucial for improving patient outcomes.
- Electrocardiographic (ECG) changes and cardiac troponin (cTn) levels are used to assess cardiac risk.
Purpose of the Study:
- To evaluate if ischemic ECG changes provide additional prognostic information on long-term mortality risk compared to peak troponin levels post-vascular surgery.
- To determine the independent predictors of long-term mortality in patients undergoing vascular surgery.
Main Methods:
- Retrospective analysis of 337 patients undergoing moderate-to-high-risk vascular surgery.
- Categorization of peak cardiac troponin I (cTnI) levels as low-positive or high-positive.
- Classification of ECGs as ischemic or nonischemic.
- Cox proportional hazards regression analysis to identify predictors of 1-year mortality.
Main Results:
- Elevated cTnI levels were associated with increased 1-year mortality (11% for low-positive, 17% for high-positive).
- Age, stratified troponin levels, tissue loss, Revised Cardiac Risk Index, and statin use were independent predictors of mortality.
- Ischemia on ECG was not found to be an independent predictor of long-term mortality.
Conclusions:
- Elevated cTnI levels are more significant than ECG findings for predicting long-term mortality after vascular surgery.
- Routine surveillance of cTn levels is recommended for cardiac event detection and risk stratification post-vascular surgery.
Objective:
The aim of this investigation was to determine if the presence of ischemic electrocardiographic (ECG) changes in patients undergoing vascular surgery provides incremental prognostic information about the long-term risk of death compared with a single peak troponin level within 48 hours after surgery.
Methods:
This was a retrospective analysis of 337 patients undergoing moderate-risk to high-risk vascular surgery at our institution whose ECG and biomarker data were complete. Peak cardiac troponin (cTn) I values that exceeded the upper reference limit (URL) were categorized as low-positive (+), at or exceeding the URL but less than three times the URL, or high-positive (+), at or exceeding three times the URL. ECGs were classified as ischemic or nonischemic. The primary outcome was death at 1 year after the vascular operation. Independent predictors of long-term mortality were determined by Cox proportional hazards regression analysis.
Results:
The most common vascular problem was an expanding abdominal aortic aneurysm (n=185 [55%]). With regard to cTnI, 53 patients (16%) were classified as high (+) and 82 (24%) as low (+). The ECG in 21 patients (6%) showed evidence of myocardial ischemia. An increase in 1-year mortality of 3% for normal, 11% for low (+), and 17% for high (+) (P<.01) was seen with incremental cTn values. Independent predictors of long-term mortality were age (odds ratio [OR], 1.05, 95% confidence interval [CI], 1.02-1.07; P<.01), stratified troponin (OR, 1.62; 95% CI, 1.25-2.10; P<.01), tissue loss (OR, 3.30; 95% CI, 1.72-6.33; P<.01), stratified Revised Cardiac Risk Index (OR, 1.32; 95% CI, 0.97-1.81; P<.07), and statin use (OR, 0.62; 95% CI, 0.40-0.98; P=.04). The presence of ischemia on ECG was not a predictor of long-term mortality.
Conclusions:
In the presence of an elevated cTn I, the ECG is not an independent predictor of long-term mortality after vascular surgery. These results support a strategy of routine surveillance of cTns after vascular surgery for the detection of cardiac events and postoperative risk stratification.

Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
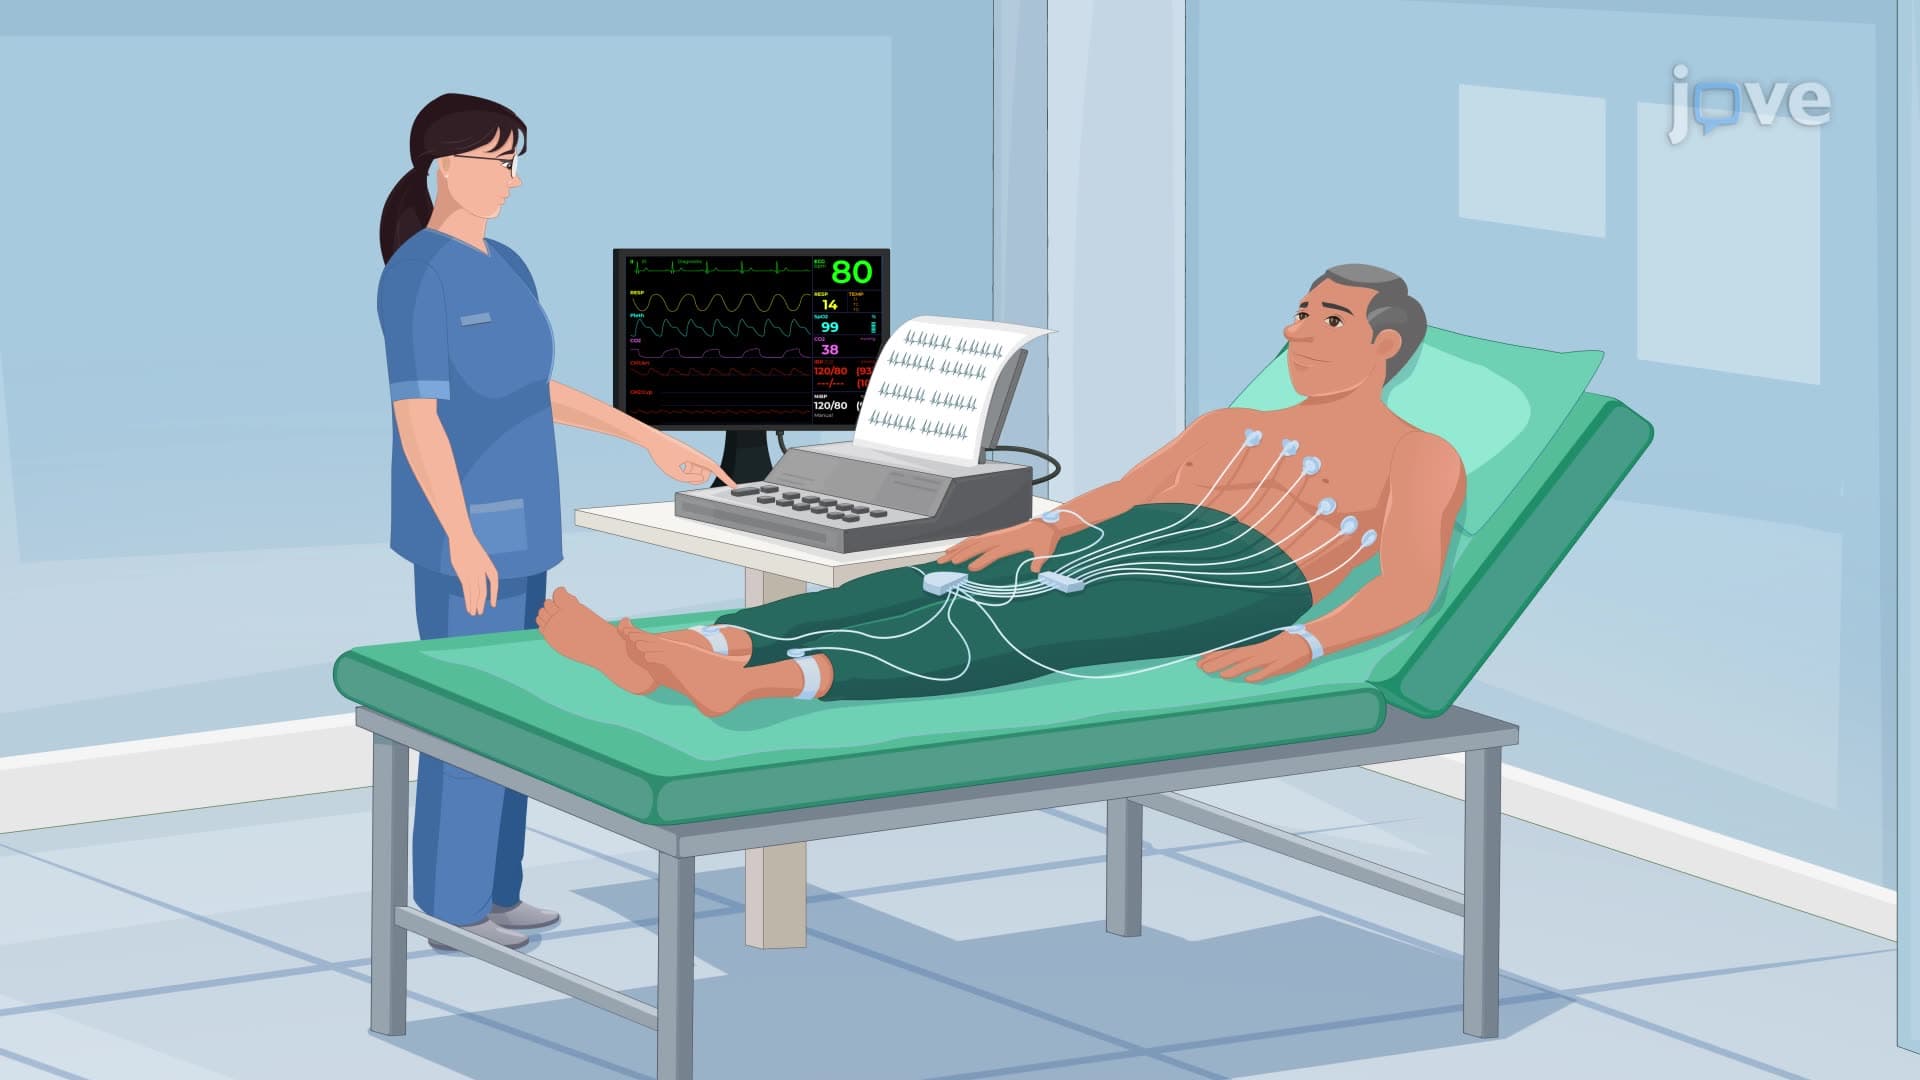 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:30
Acute Coronary Syndrome I: Introduction
 01:22
Aneurysm IV: Nursing Management