Related Experiment Video
Updated: May 18, 2026
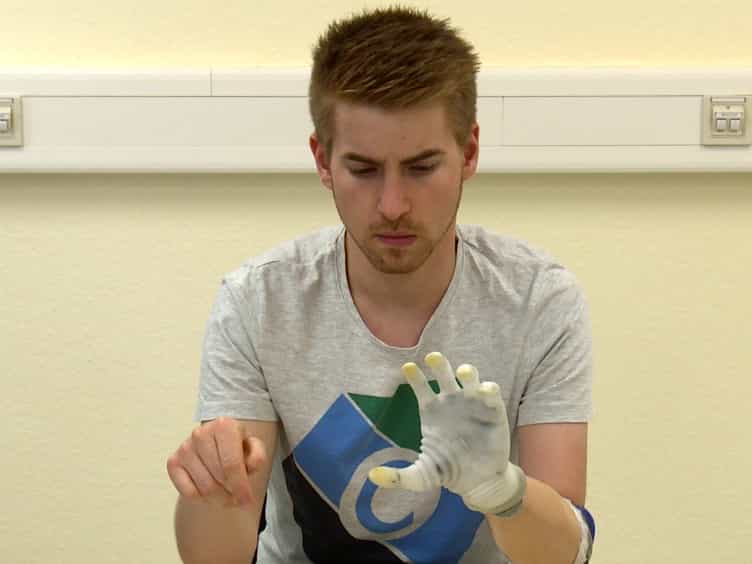

A Structured Rehabilitation Protocol for Improved Multifunctional Prosthetic Control: A Case Study
Published on: November 6, 2015
[Psychosocial characterization of a Portuguese lower limb amputee population]
Inês Machado Vaz1, Vanessa Roque, Sabrina Pimentel
1Serviço de Medicina Física e de Reabilitação do Centro Hospitalar S. João, Porto, Portugal.

Objective:
This study aims to describe psychosocial status in lower limb amputees referred to a Physical and Rehabilitation Medicine (PRM) department of a central Portuguese Hospital.
Methods:
Cross-sectional study of 45 consecutive patients with lower limb amputation, referred to PMR consultation after hospital discharge. Of the initial sample, two patients were excluded from the analysis, and four patients refused to participate in the study. The socio-demographic, medical and surgical history were obtained through structured questionnaire, and clinical information regarding the characteristics of the amputation was abstracted from medical records. Functional capacity was assessed with the Amputee Mobility Predictor (AMP), quality of life through short-form 36 (SF36), and depressive and anxious symptoms by the Hospital Anxiety and Depression Scale (HADS).
Results:
Out of 39 patients analyzed, 32 (82.1%) were men, aged [average (standard deviation): 67, 6 (12.57)] years, 28 (71.8%) were married, 30 (76.9%) were retired, 3 (7.7%) were unemployed, 4 (10.3%) were on sick leave, and 2 (5.1%) were active. Regarding the cause of amputation, 36 (92.3%) were of vascular etiology, 1 (2.6%) caused by an infection, and 2 (5.1%) due to bone tumours, 23 (59%) had a transfemoral amputation, 10 (25.6%) had a transtibial amputation, and 6 (15.4%) had foot amputations of the foot. In the sample studied, 14 (35.9%) had pathological levels of anxiety (HADS-anxiety ≥ 8) and 15 (38.5%) had clinical depression (HADS-depression ≥ 8). The evaluation of quality of life and general perception of health status, showed lower than average score especially in the physical dimensions with a physical component summary score of the SF36 [P50 (P25-P75): 31.4 (26.8-39.4)], and in the mental component summary of SF36 [P50 (P25-P75): 41.9 (31.8-48.3)]. In this sample, the data showed the AMP score [P50 (P25-P75): 8 (4-16)], ranging from 0 to 27.
Conclusion:
This sample has a high prevalence of depressive/anxious symptoms. Considering that these mood changes have a major impact on the adherence to the rehabilitation program, functional outcome and quality of life, its early identification and treatment should be part of their overall management.

Related Concept Videos
 01:30
Peripheral Artery Disease I: Introduction
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:30
Psychosurgery
Historical Development of Psychosurgery
In the 1930s, Portuguese neurologist Antonio Egas Moniz introduced a surgical procedure designed...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Peripheral Artery Disease IV: Nursing Management