Related Experiment Video
Updated: May 18, 2026
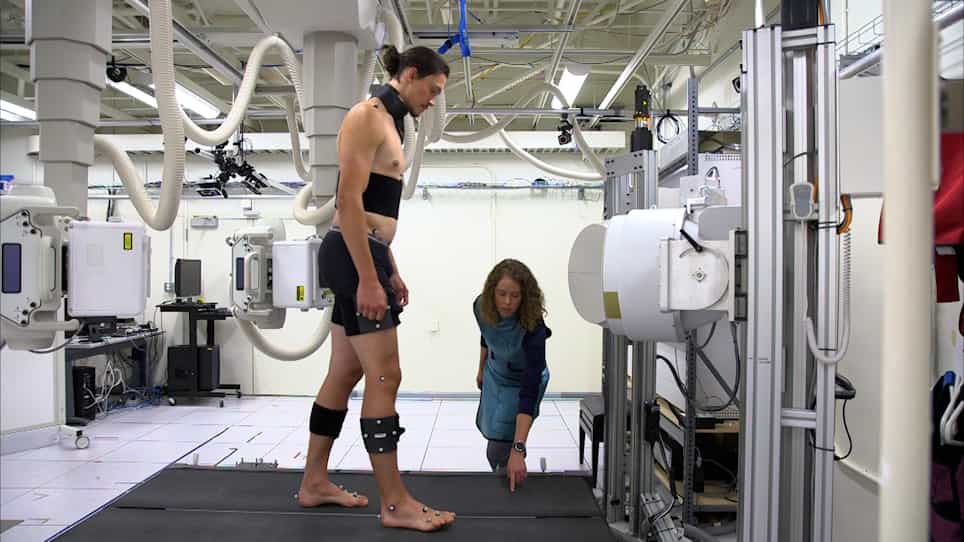

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Intra-abdominal fluid extravasation during hip arthroscopy: a survey of the MAHORN group
Mininder S Kocher1, Jeremy S Frank, Adam Y Nasreddine
1Division of Sports Medicine, Children's Hospital Boston, Massachusetts, USA. mininder.kocher@childrens.harvard.edu

Purpose:
The purpose of this study was to survey experts in the field of hip arthroscopy from the Multicenter Arthroscopy of the Hip Outcomes Research Network (MAHORN) group to determine the frequency of symptomatic intra-abdominal fluid extravasation (IAFE) after arthroscopic hip procedures, identify potential risk factors, and develop preventative measures and treatment strategies in the event of symptomatic IAFE.
Methods:
A survey was sent to all members of the MAHORN group. Surveys collected data on general hip arthroscopy settings, including pump pressure and frequency of different hip arthroscopies performed, as well as details on cases of symptomatic IAFE. Responses to the survey were documented and analyzed.
Results:
Fifteen hip arthroscopists from the MAHORN group were surveyed. A total of 25,648 hip arthroscopies between 1984 and 2010 were reviewed. Arthroscopic procedures included capsulotomies, labral reattachment after acetabuloplasty, peripheral compartment arthroscopy, and osteoplasty of the femoral head-neck junction. Of the arthroscopists, 7 (47%) had 1 or more cases of IAFE (40 cases reported). The prevalence of IAFE in this study was 0.16% (40 of 25,650). Significant risk factors associated with IAFE were higher arthroscopic fluid pump pressure (P = .004) and concomitant iliopsoas tenotomy (P < .001). In all 40 cases, the condition was successfully treated without long-term sequelae. Treatment options included observation, intravenous furosemide, and Foley catheter placement, as well as 1 case of laparotomy.
Conclusions:
Symptomatic IAFE after hip arthroscopy is a rare occurrence, with an approximate prevalence of 0.16%. Prevention of IAFE should include close intraoperative and postoperative monitoring of abdominal distention, core body temperature, and hemodynamic stability. Concomitant iliopsoas tenotomy and high pump pressures may be risk factors leading to symptomatic IAFE.
Level Of Evidence:
Level IV, therapeutic case series.
Related Concept Videos
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:17
Ultrasonography
During an ultrasonography procedure, a handheld device called a...