Related Experiment Video
Updated: May 18, 2026


Cutaneous Leishmaniasis in the Dorsal Skin of Hamsters: a Useful Model for the Screening of Antileishmanial Drugs
Published on: April 21, 2012
Levamisole-induced Wegener's granulomatosis following contaminated cocaine abuse
Sandra A Kopp1, Whitney A High, Justin J Green
1University of Medicine and Dentistry of New Jersey--Robert Wood Johnson Medical School at Camden, NJ, USA. kopp-sandra@cooperhealth.edu

Abstract:
A 44-year-old woman with a medical history of chronic pain syndrome presented with a 3-day history of a painful "rash" that started on her face and spread to her legs. Further history revealed that she recently started a new medication, varenicline, 7 weeks prior to admission and had a long-standing history of intranasal cocaine use. Review of systems was significant for rhinitis, nasal congestion, joint pain, and a febrile episode 2 days prior to admission. Physical examination revealed centrally violaceous, tender, stellate, and retiform purpuric patches and plaques on her extremities, nasal dorsum, and cheeks. Approximately 1.0-centimeter tender purpuric nodules were noted on her bilateral second proximal interphalangeal joints. She was afebrile. Initial laboratory data revealed a mild leukopenia, normal serum urea nitrogen and creatinine without hematuria, and an elevated erythrocyte sedimentation rate. Further analysis showed a normal complement level, negative antinuclear antibody, human immunodeficiency virus, rapid plasma reagin, and hepatitis panel. Trace cryoglobenemia and a positive anti-streptolysin O were noted, along with a positive antineutrophil cytoplasmic antibody (c-ANCA) (> 8.0 U) and perinuclear antineutrophil cytoplasmic antibodies, or p-ANCA (1.5 U). The hypercoagulable workup was negative. A skin biopsy taken from the left thigh was consistent with leukocytoclastic vasculitis. After several weeks of high-dose oral prednisone taper, the patient's symptoms improved, but flared upon discontinuation. On follow-up, she admitted to frequent relapses of cocaine abuse and had developed tender purpuric plaques on her nose, ears, and extremities, some with ulcerations (Figure 1 and Figure 2). She also had significant edema and joint pain that limited her ambulation. Further evaluation revealed normal chest x-ray results; however, computed tomography of her sinuses demonstrated thickened maxillary sinuses consistent with subacute/ chronic sinusitis. She also developed hematuria. Mass spectrometry analysis ofhair and urine samples tested positive for cocaine and levamisole. A presumptive diagnosis of levamisole-induced Wegener's vasculitis was made. She was restarted on high-dose prednisone and methotrexate with improvement and advised to discontinue cocaine use, so as to avoid exposure to both substances.

Related Concept Videos
 01:24
Drug Toxicity: Risk factors
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:16
Drug toxicity: Idiosyncratic Reactions
 01:30
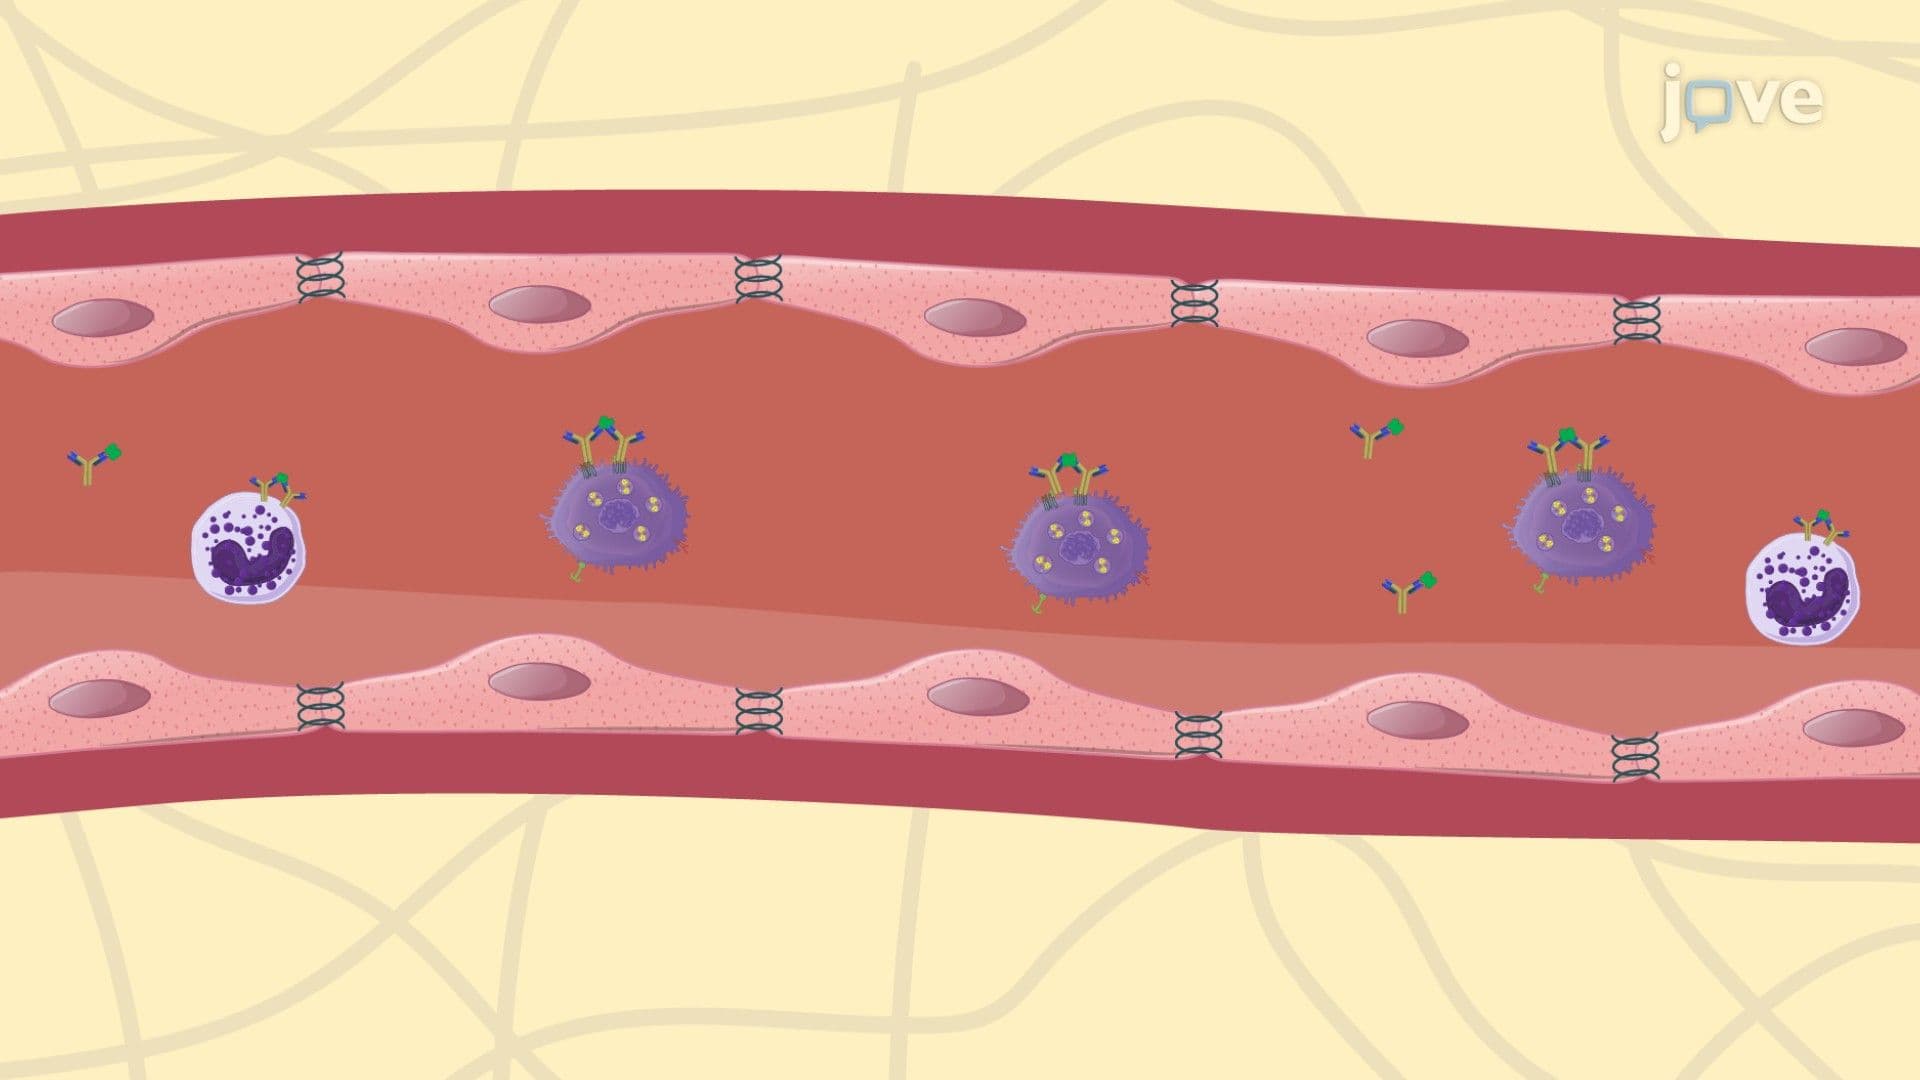
Drug Toxicity: Allergic Reactions
 01:00
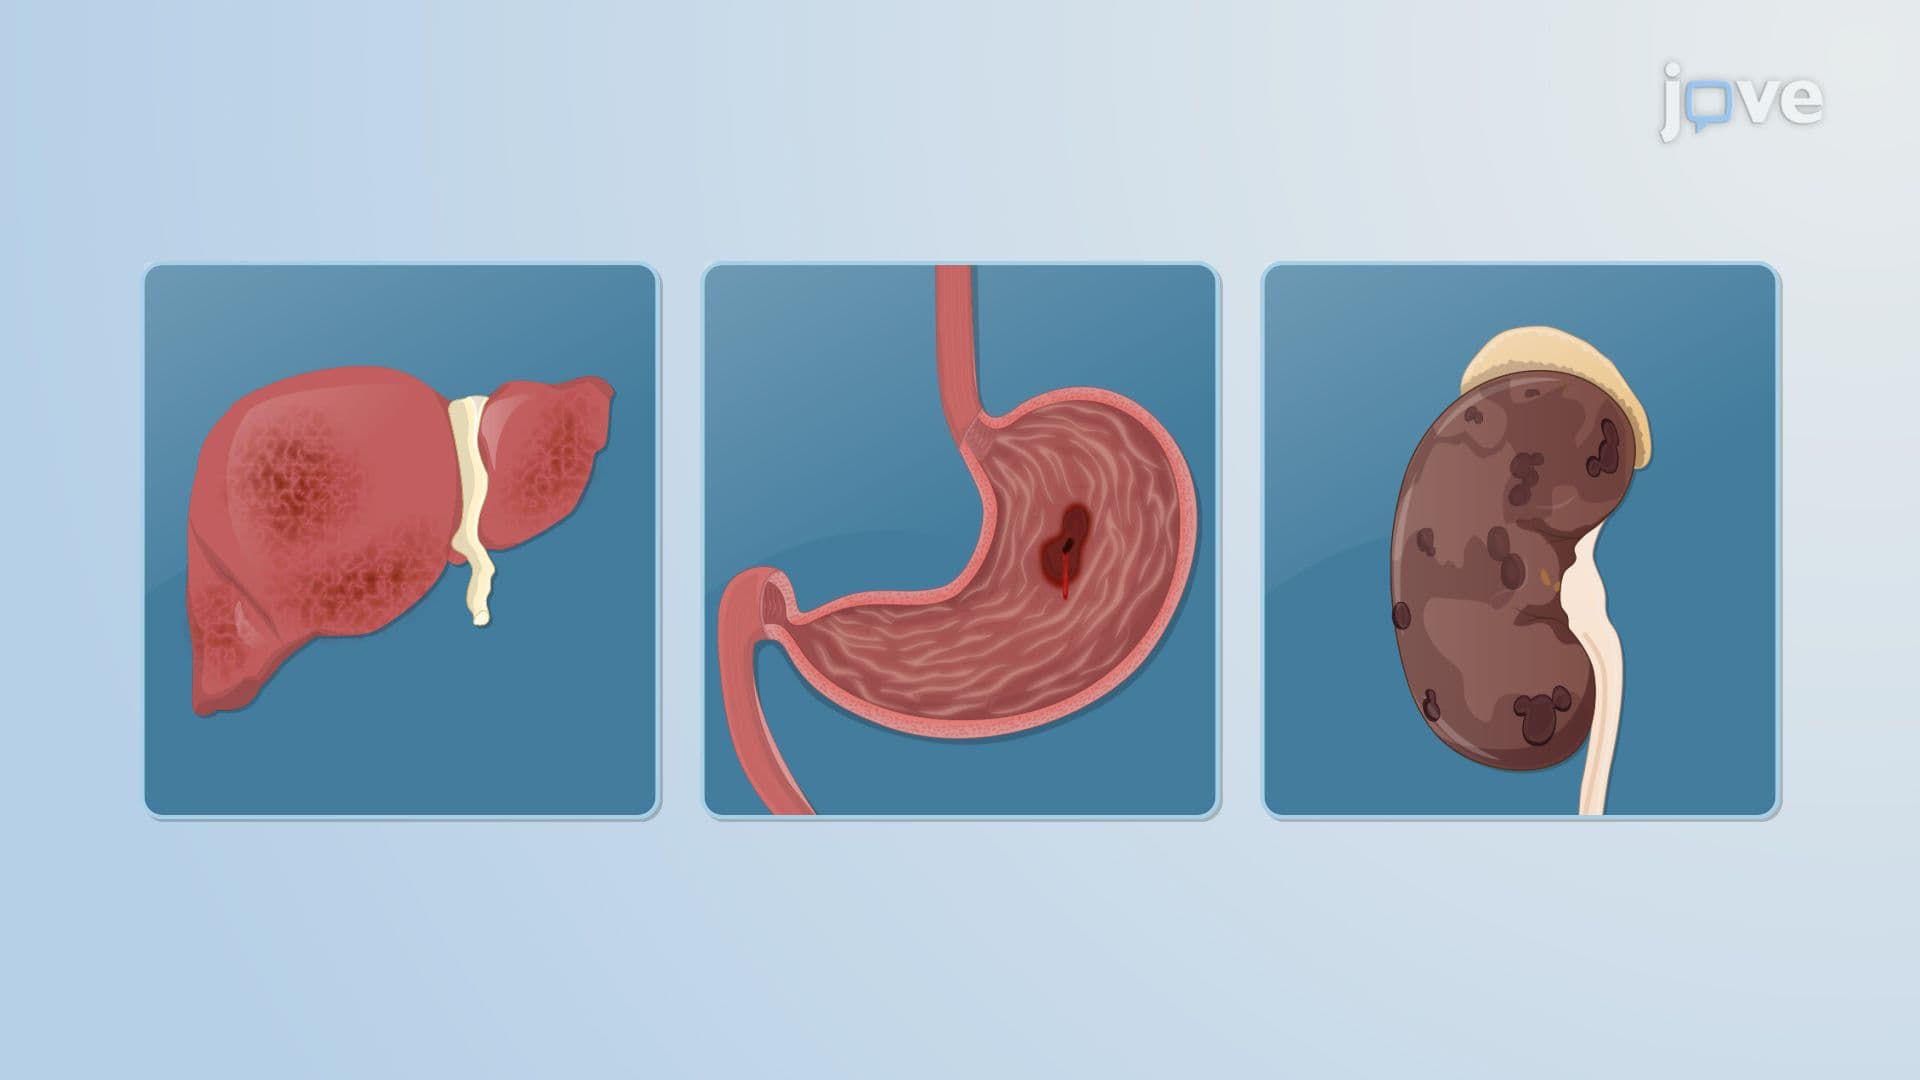
Drug Toxicity: Overview
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections