β-Arrestin-2 mediates the proinflammatory effects of proteinase-activated receptor-2 in the airway
Related Experiment Video
Updated: May 18, 2026
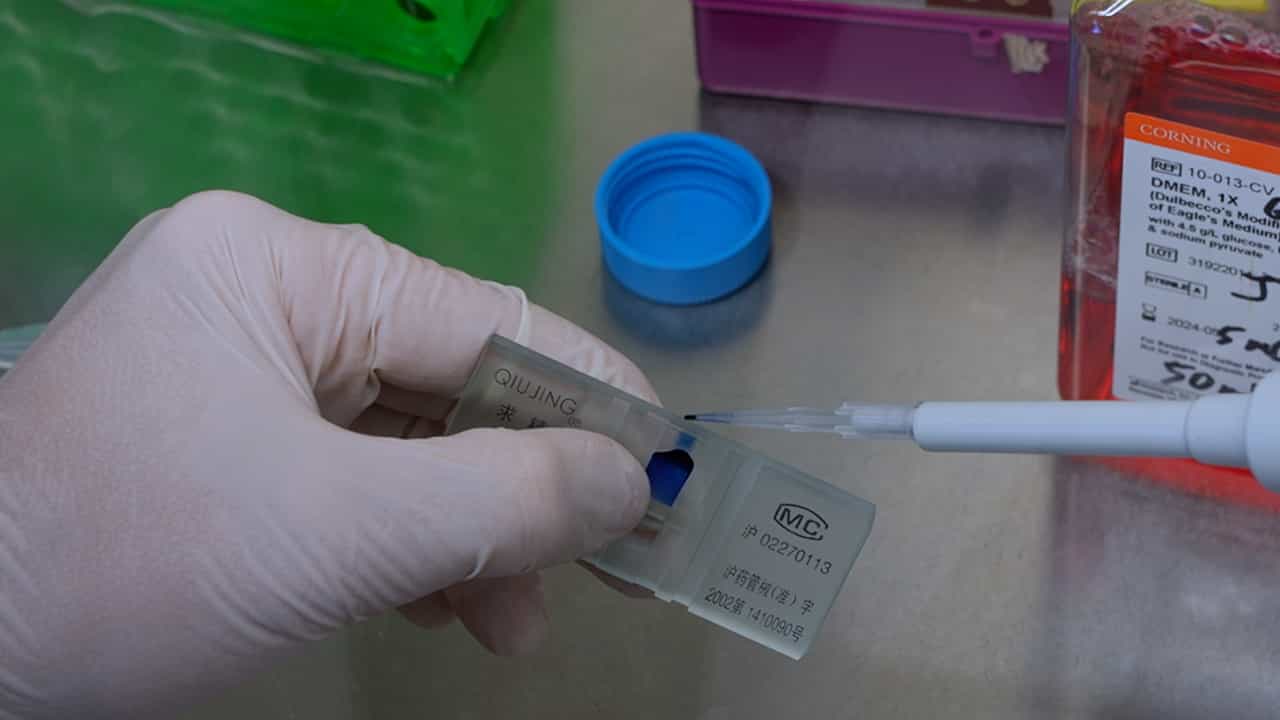
Characterizing Modulators of Protease-Activated Receptors with a Calcium Mobilization Assay Using a Plate Reader
Published on: May 24, 2024
Heddie L Nichols1, Mahmoud Saffeddine, Barbara S Theriot
1Division of Biomedical Sciences, University of California, Riverside, CA 92521, USA.

Abstract:
Proteinase-Activated receptor-2 (PAR(2)), a G-protein-coupled Receptor, activated by serine proteinases, is reported to have both protective and proinflammatory effects in the airway. Given these opposing actions, both inhibitors and activators of PAR(2) have been proposed for treating asthma. PAR(2) can signal through two independent pathways: a β-arrestin-dependent one that promotes leukocyte migration, and a G-protein/Ca(2+) one that is required for prostaglandin E(2) (PGE(2)) production and bronchiolar smooth muscle relaxation. We hypothesized that the proinflammatory responses to PAR(2) activation are mediated by β-arrestins, whereas the protective effects are not. Using a mouse ovalbumin model for PAR(2)-modulated airway inflammation, we observed decreased leukocyte recruitment, cytokine production, and mucin production in β-arrestin-2(-/-) mice. In contrast, PAR(2)-mediated PGE(2) production, smooth muscle relaxation, and decreased baseline airway resistance (measures of putative PAR(2) "protective" effects) were independent of β-arrestin-2. Flow cytometry and cytospins reveal that lung eosinophil and CD4 T-cell infiltration, and production of IL-4, IL-6, IL-13, and TNFα, were enhanced in wild-type but not β-arrestin-2(-/-) mice. Using the forced oscillation technique to measure airway resistance reveals that PAR(2) activation protects against airway hyperresponsiveness by an unknown mechanism, possibly involving smooth muscle relaxation. Our data suggest that the PAR(2)-enhanced inflammatory process is β-arrestin-2 dependent, whereas the protective anticonstrictor effect of bronchial epithelial PAR(2) may be β-arrestin independent.

Related Concept Videos
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:26
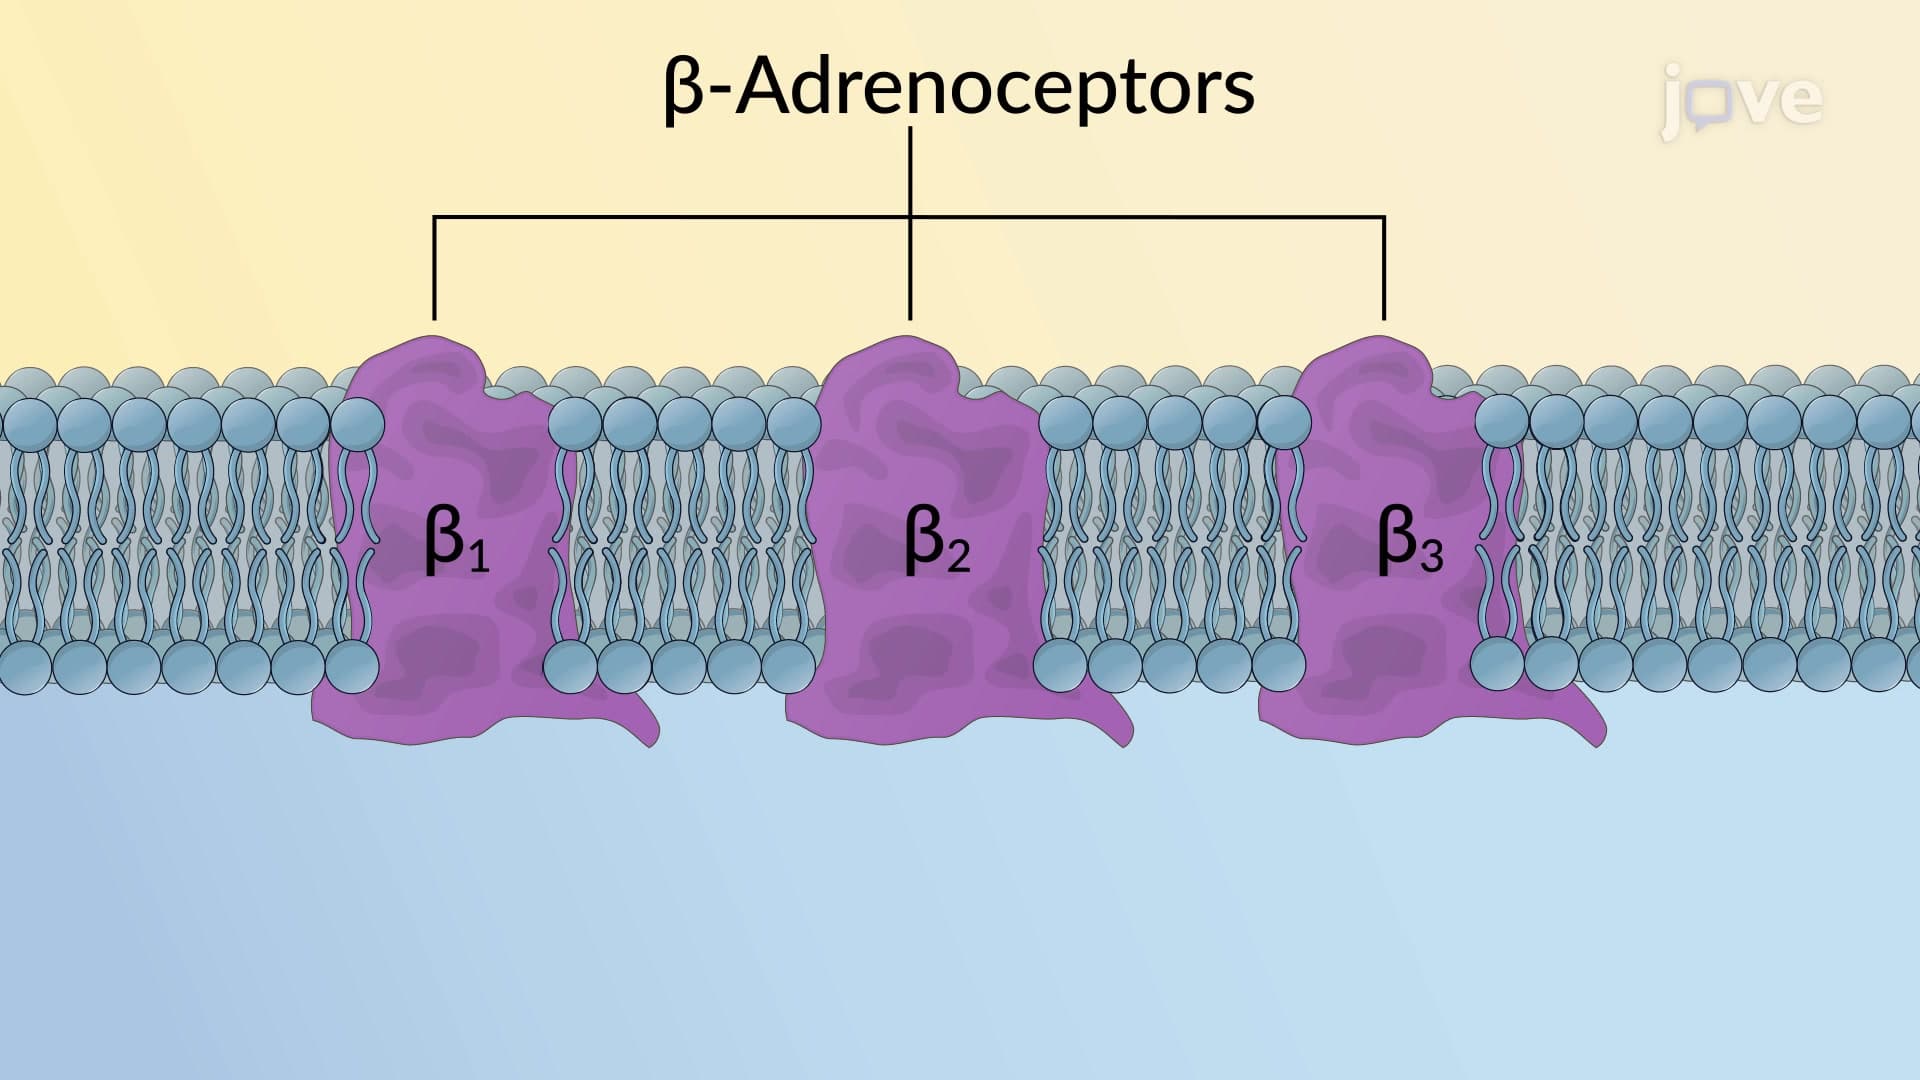
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:12
GPCR Desensitization
 01:31
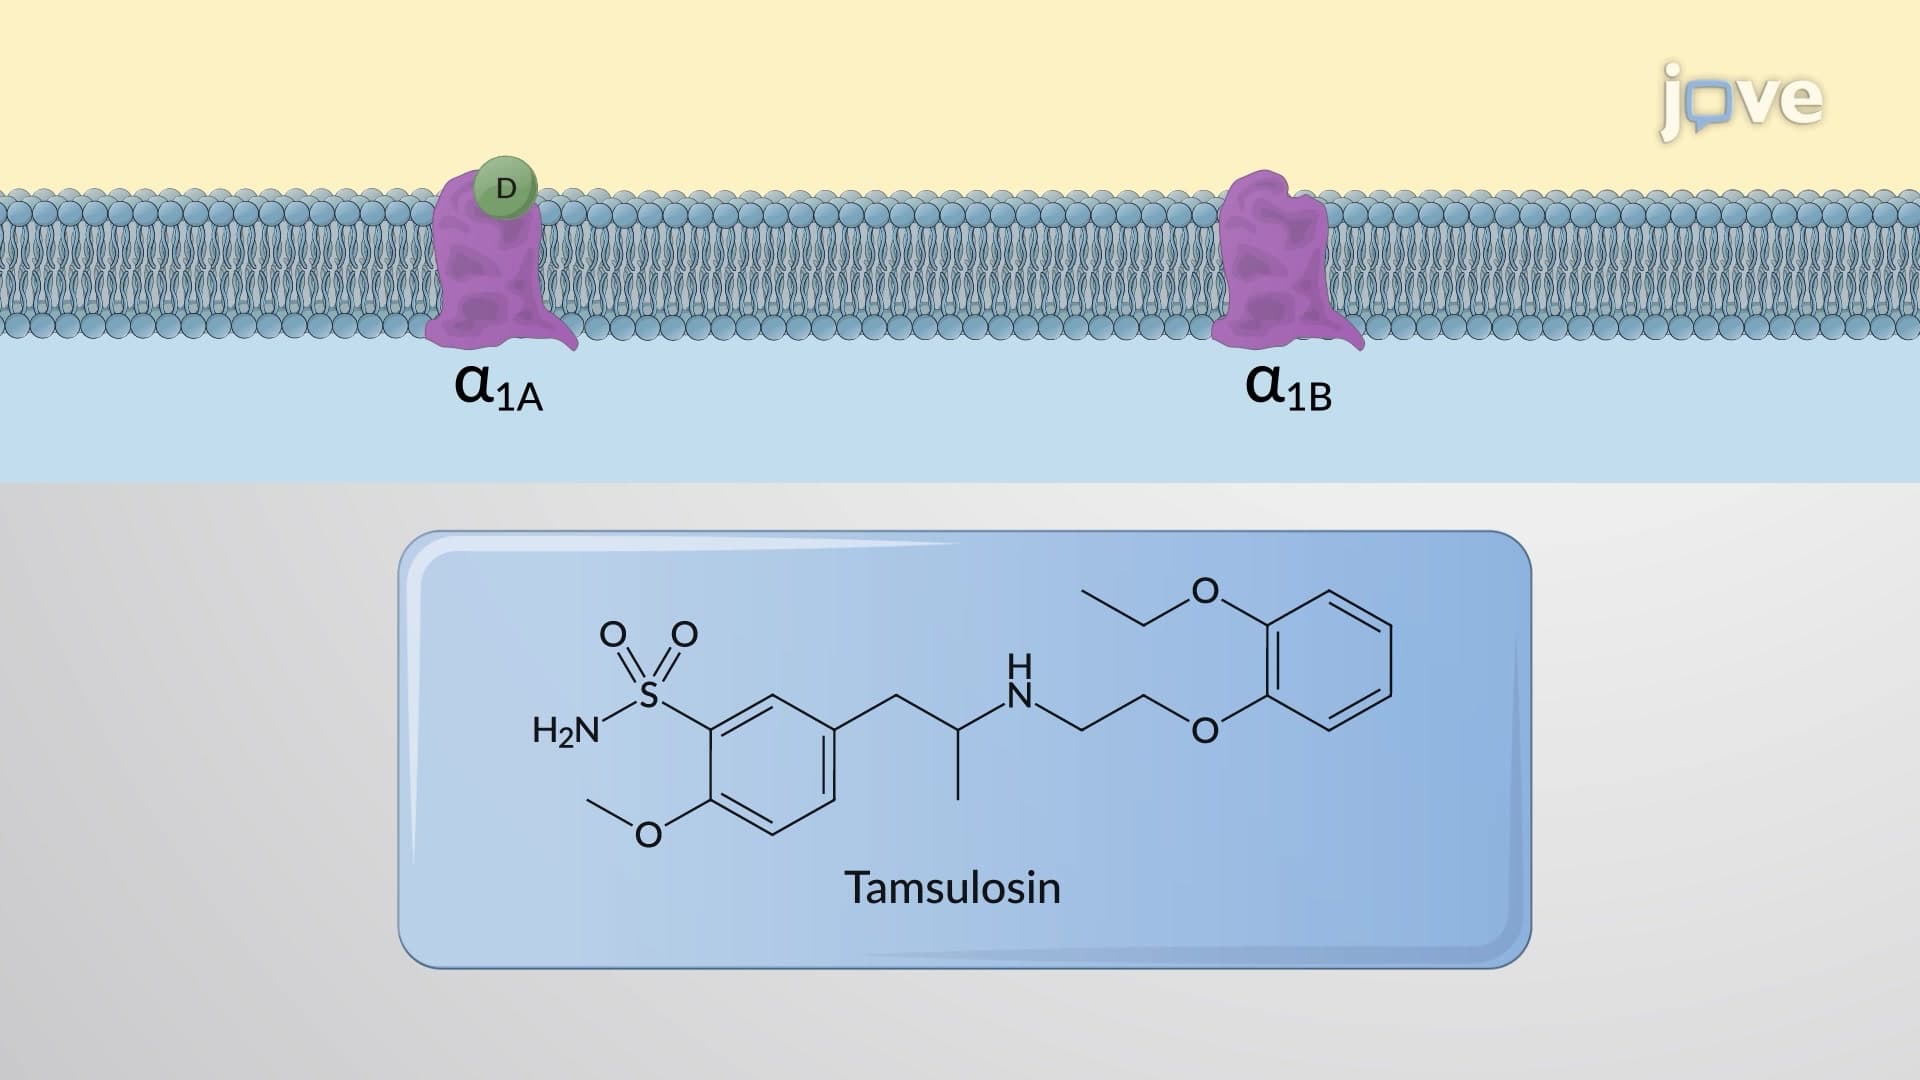
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:09
GPCRs Regulate Adenylyl Cylase Activity
Two...