Related Experiment Video
Updated: May 18, 2026
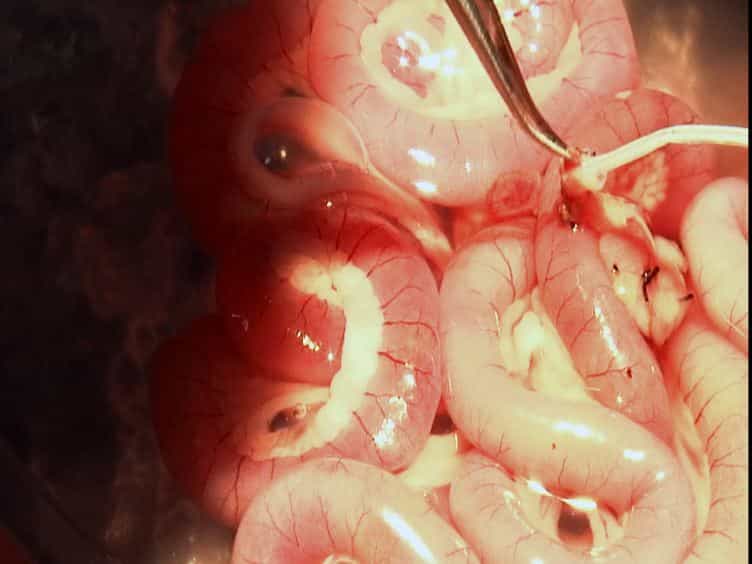
Orthotopic Small Bowel Transplantation in Rats
Published on: November 6, 2012
Combined liver-intestine grafts compared with isolated intestinal transplantation in children: a single-center
Cristina Dopazo1, Girish L Gupte, Khalid Sharif
1Liver Unit (including small bowel transplantation), Birmingham Children's Hospital, Birmingham, UK.

Insights
Combined liver-intestinal transplantation increases early mortality risk. Key predictors include intraoperative transfusions, low post-reperfusion base excess, and vascular complications.
Area of Science:
- Transplantation Surgery
- Gastroenterology
- Critical Care Medicine
Background:
- Intestinal transplantation carries a high risk of early complications and mortality.
- Combined liver-intestinal transplantation (CLITx) presents unique challenges compared to isolated intestinal transplantation (IITx).
Purpose of the Study:
- To identify perioperative factors influencing early mortality (≤6 months) in primary small bowel transplantations.
- To compare early mortality risks between isolated intestinal (IITx) and combined liver-intestinal transplantation (CLITx).
Main Methods:
- Prospective analysis of 51 primary small bowel transplantations (December 1999 - August 2009).
- Inclusion of isolated intestinal (n=12) and combined liver-intestinal (n=39) transplant recipients.
- Multivariate analyses to determine predictors of early mortality in the CLITx group.
Main Results:
- Ten patients (19%) died within 6 months post-transplantation, all within the CLITx group.
- Significant predictors of early mortality in CLITx included: intraoperative red blood cell transfusion >70 mL/kg (OR=13.79), post-reperfusion base excess <-16 (OR=14.05), thrombocytopenia (day 1-15, OR=5.22), and vascular complications (OR=8.96).
Conclusions:
- The inclusion of a liver graft in intestinal transplantation significantly increases the risk of early mortality.
- Strategies to mitigate this risk should focus on improved patient selection and earlier referral before severe liver failure develops.
Background:
Intestinal transplantation is known to be associated with a high risk of early complications and mortality.
Methods:
We analyzed prospective data of 51 primary small bowel transplantations from December 1999 to August 2009 and identified perioperative factors that impact on early mortality (≤6 months after transplantation) after isolated intestinal (IITx; n=12) and combined liver-intestinal transplantation (CLITx group; n=39).
Results:
Ten patients died during the first 6 months after transplantation, all of them in CLITx group (n=10/51, 19%). Multivariate analyses demonstrated intraoperative red blood cell transfusion greater than 70 mL/kg (P=0.019, odds ratio [OR]=13.79) and base excess 30-min after reperfusion less than -16 (P=0.001, OR=14.05), thrombocytopenia (<50,000 per dL) between day 1 and day 15 after transplantation (P=0.047, OR=5.22), and occurrence of vascular complications (P=0.003, OR=8.96) during the posttransplantation period as predictors of early mortality in CLITx group.
Conclusion:
Risk of mortality at 6 months after intestinal transplantation increased when the liver is included as combined graft. Strategies to reduce mortality such as refining selection for transplantation and early referral before the development of liver failure should be a priority.


