Related Experiment Video
Updated: May 18, 2026
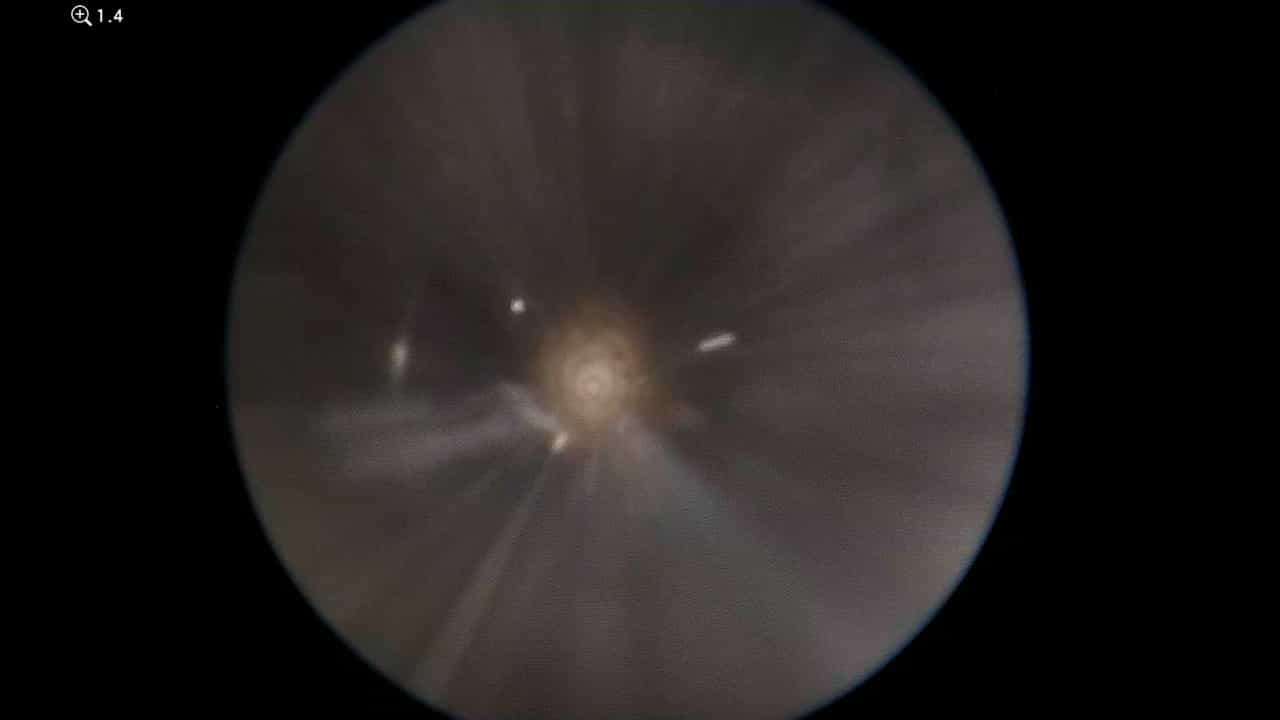
Endoscopic Third Ventriculostomy and Pineal Biopsy from a Single Entry Point
Published on: June 28, 2024
Growth hormone deficiency and diabetes insipidus as a complication of endoscopic third ventriculostomy
Kimberly S Tafuri1, Thomas A Wilson
1Stony Brook University, Department of Pediatrics, Stony Brook Childrens Hospital, Division of Pediatric Endocrinology, Stony Brook, NY, U.S.A. Kimberly.Tafuri@stonybrookmedicine.edu

Insights
Endoscopic third ventriculostomy (ETV) can cause rare pituitary complications. This case highlights a child with growth hormone deficiency and permanent diabetes insipidus (DI) after ETV, a unique presentation of multiple pituitary hormone deficiencies.
Area of Science:
- Neurosurgery
- Pediatric Endocrinology
- Neuroendocrinology
Background:
- Endoscopic third ventriculostomy (ETV) is a primary treatment for obstructive hydrocephalus.
- Endocrinological complications following ETV in pediatric patients are infrequent.
- Diabetes insipidus (DI) is the most common complication, typically transient and accounting for 0.5% of ETV-related issues.
Observation:
- A 6-year-old girl developed growth hormone deficiency and permanent DI post-ETV.
- This patient exhibited multiple pituitary hormone deficiencies, a previously undocumented complication of ETV.
- The patient presented with a classical triphasic response of DI, further distinguishing this case.
Findings:
- The presented case is the first documented instance of multiple pituitary hormone deficiencies after ETV.
- The development of permanent DI and growth hormone deficiency suggests significant pituitary stalk compression or hypothalamic injury.
- The triphasic DI response observed aligns with experimental findings in animal models.
Implications:
- This case underscores the potential for severe, long-term endocrinological sequelae from ETV, even if rare.
- It emphasizes the need for vigilant long-term endocrine monitoring in pediatric patients after ETV.
- Understanding the mechanism of pituitary injury may inform procedural modifications to minimize risks.
Abstract:
Endoscopic third ventriculostomy (ETV) has become the procedure of choice for the treatment of obstructive hydrocephalus in children and adults. Endocrinological complications of ETV in children are rare. Diabetes insipidus (DI) is the most common and accounts for only 0.5% of complications from ETV. The majority of documented cases are transient. To date, there are no documented cases of multiple pituitary hormone deficiencies. We present here a 6-year-old girl with growth hormone deficiency and permanent DI which developed as a complication of ETV. This patient is unique in both demonstrating multiple pituitary hormone deficiencies and the classical triphasic response of DI after ETV. We postulate that these complications were caused by compression of the pituitary stalk and hypothalamic injury during the procedure. We compare our case presentation to experimental studies conducted in rats.
Related Concept Videos
 01:22
Diabetes Insipidus II: Pathophysiology
 01:29
Diabetes Insipidus I: Introduction
 01:19
Type I Diabetes III: Clinical Manifestations
 01:22
Complications of Diabetes Mellitus
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...