Related Experiment Video
Updated: May 17, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Effect of high-flow nasal cannula and body position on end-expiratory lung volume: a cohort study using electrical
Jordi Riera1, Purificación Pérez, Jordi Cortés
1Critical Care Department, Vall d'Hebron Research Institut, Vall d'Hebron University Hospital, Universitat Autònoma de Barcelona, Barcelona, Spain. jorriera@vhebron.net

Background:
Electrical impedance tomography measures changes in lung impedance, which are mainly related to changes in lung volume. We used electrical impedance tomography to investigate the effects of high-flow nasal cannula (HFNC) and body position on global and regional end-expiratory lung impedance variation (ΔEELI).
Methods:
Prospective study with 20 healthy adults. Two periods were defined: the first in supine position and the second in prone position. Each period was divided into 3 phases. In the first and the third phases the subjects were breathing ambient air, and in the second HFNC was implemented. Four regions of interest were defined: 2 ventral and 2 dorsal. For each respiratory cycle, global and regional ΔEELI were measured by electrical impedance tomography and were expressed as a function of the tidal variation of the first stable respiratory cycle (units).
Results:
HFNC increased global EELI by 1.26 units (95% CI 1.20-1.31, P < .001) in supine position, and by 0.87 units (95% CI 0.82-0.91, P < .001) in prone position. The distribution of ΔEELI was homogeneous in prone position, with no difference between ventral and dorsal lung regions (-0.01 units, 95% CI -0.01 to 0, P = .18), while in supine position a significant difference was found (0.22 units, 95% CI 0.21-0.23, P < .001) with increased EELI in ventral areas.
Conclusions:
HFNC increased global EELI in our population, regardless of body position, suggesting an increase in functional residual capacity. Prone positioning was related to a more homogeneous distribution of ΔEELI, while in supine position ΔEELI was higher in the ventral lung regions.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:15
Respiratory Volumes
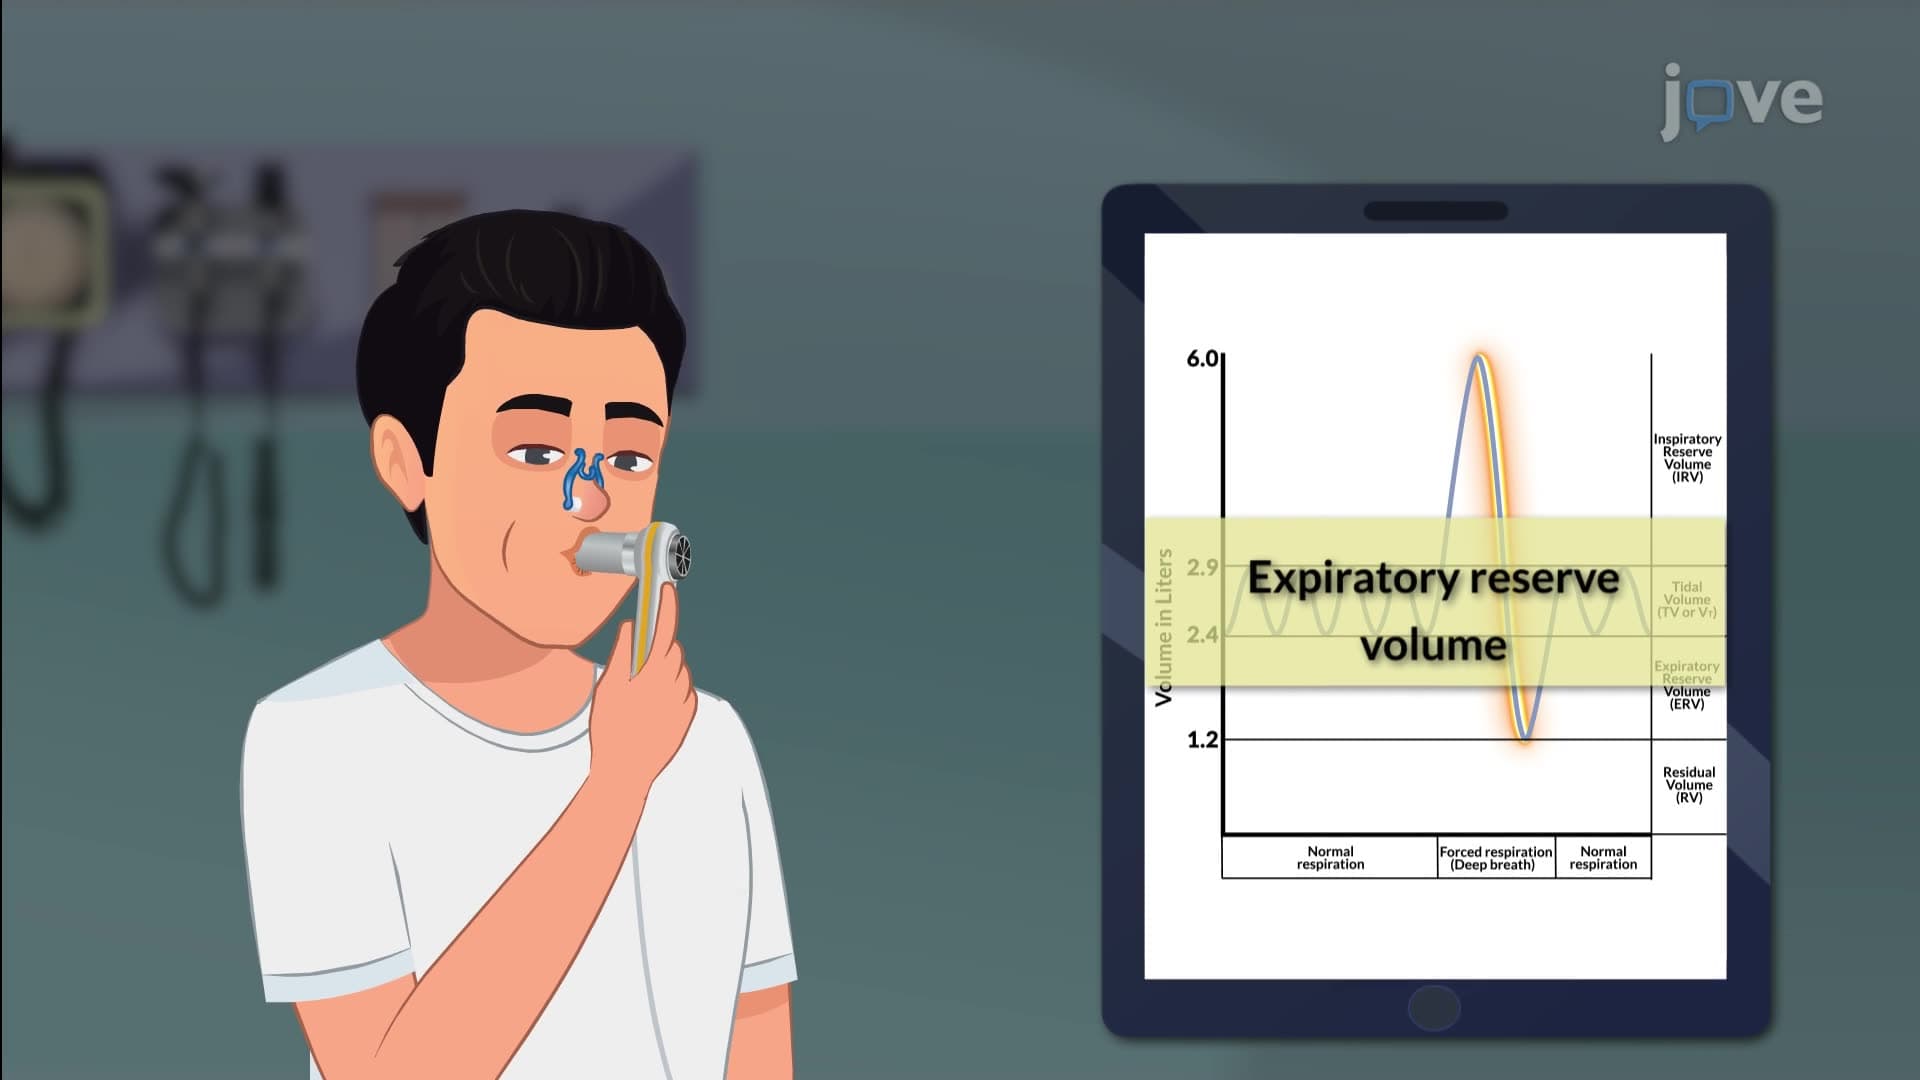
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: