Related Experiment Video
Updated: May 17, 2026
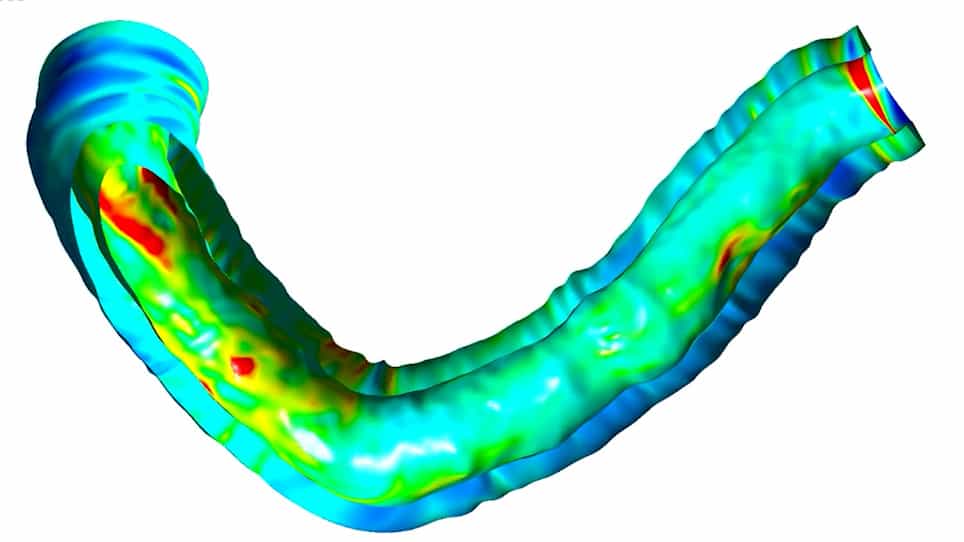

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Women and coronary artery disease. Part I: basic considerations
Seyed-Hesameddin Abbasi1, Seyed-Ebrahim Kassaian
1Tehran Heart Center, Tehran University of Medical Sciences, Tehran, Iran. ; Petroleum Industry Health Research Institute, NIOC Central Hospital, Tehran, Iran.

Insights
Cardiovascular disease (CVD) is a leading cause of death in women, often overlooked due to a lack of awareness and sex-specific research. New risk assessment tools and understanding female-specific pathophysiology are crucial for improving outcomes.
Area of Science:
- Cardiology
- Women's Health
- Public Health
Background:
- Cardiovascular disorders (CVD) are the leading cause of death in women, surpassing cancer.
- Coronary artery disease (CAD) mortality is high in women, with concerning trends in younger populations and higher pre-hospitalization death rates compared to men.
- A significant knowledge gap exists regarding CVD in women, stemming from a historical focus on male-centric research, leading to disparities in awareness, risk assessment, and treatment.
Purpose of the Study:
- To highlight the critical need for improved awareness and sex-specific approaches to cardiovascular disease in women.
- To advocate for the development and adoption of gender-specific risk assessment tools for coronary artery disease (CAD).
- To emphasize the importance of understanding female-specific pathophysiological mechanisms in CAD.
Main Methods:
- Review of epidemiological data on cardiovascular disease mortality in women compared to other major diseases.
- Analysis of trends in sudden cardiac death and pre-hospitalization mortality rates between genders.
- Discussion of current limitations in risk assessment tools (e.g., Framingham Risk Score) for women and the potential of alternatives (e.g., Reynolds Risk Score).
- Exploration of pathophysiological differences, particularly endothelial and microvascular dysfunction, in female CAD.
Main Results:
- Women experience higher mortality from cardiovascular disorders than from a combination of major cancers and lung disease.
- While age-adjusted CAD mortality shows mixed trends, young women face increasing risks, and women are more likely to die before reaching emergency care.
- Existing risk assessment models are often inadequate for women, necessitating the use of more appropriate tools like the Reynolds Risk Score.
- Endothelial and microvascular dysfunction are key contributors to non-obstructive CAD in women, an area underrepresented in research.
Conclusions:
- There is an urgent need to increase awareness of cardiovascular disease risks among women and healthcare providers.
- Current diagnostic and treatment strategies for CAD require adaptation to address female-specific pathophysiology and risk factors.
- Further research focusing on women's cardiovascular health, including enrollment in clinical trials and investigation of sex-specific mechanisms, is essential to reduce the burden of CAD in this population.
Abstract:
Women die of cardiovascular disorders even more than a combination of breast cancer, stroke, chronic obstructive pulmonary disease, and lung cancer. Recent data show that while 1 out of 2.6 women die of coronary artery disease (CAD), only 1 out of 4.6 die from cancer. Whereas some studies show an increase in the age-adjusted mortality of CAD in both women and men, some other studies report an increase in mortality amongst young women. There is a significant decrease in sudden cardiac death in men without significant change in women, and more women die of CAD before their arrival at the emergency room of hospitals than do men. It is, therefore, regrettable that many women and their physicians are not sufficiently aware of the problem and this unawareness is believed to be a major culprit for the existing gender disparities and inaction on the part of women as regards risk modification. What is more, the bulk of our knowledge, preventive measures, diagnostic strategies, and treatment plans are on the basis of studies conducted chiefly in men, when powerful evidence-based gender-specific recommendations call for efforts to enroll more women in order to reach a desirable level of sex representation.Given the significance of CAD assessment in women, it is essential that an acceptable risk score system be devised to estimate the risk of coronary events. The Framingham Risk Score, which has been used for this purpose for a long time, is no longer suitable for women and the Reynolds Risk Score seems to be a more appropriate tool.Finally, from a pathophysiological point of view, endothelial and microvascular dysfunctions are the most salient contributors to the development of CAD in women by comparison with men and they give rise to non-obstructive CAD. Lamentably, most of the relevant studies conducted hitherto have focused predominantly on men; any attempt to redress the balance would be of great value in the endeavors to decrease the risk in women.
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:30
Angina I: Introduction
 01:30
Coronary Artery Disease III: Clinical Manifestations