Related Experiment Video
Updated: May 17, 2026

A Mouse Model of Hemorrhagic Transformation Induced by Acute Hyperglycemia Combined with Transient Focal Ischemia
Published on: November 15, 2024
Post-ischemic hyperglycemia exacerbates the development of cerebral ischemic neuronal damage through the cerebral
Yui Yamazaki1, Shinichi Harada, Shogo Tokuyama
1Department of Clinical Pharmacy, School of Pharmaceutical Sciences, Kobe Gakuin University, 1-1-3 Minatojima, Chuo-ku, Kobe 650-8586, Japan.

Abstract:
Post-ischemic hyperglycemia may be one of the triggers of ischemic neuronal damage. However, the detailed mechanisms of this injury process are still unknown. Here, we focused on the involvement of the sodium-glucose transporter (SGLT), which transports glucose together with Na(+) ions, and generates inward currents while transporting glucose into cells, resulting in depolarization and increased excitability. The aim of this study was to determine the involvement of the SGLT in the development of cerebral ischemic stress-induced neuronal damage. Male ddY mice were subjected to 2h of middle cerebral artery occlusion (MCAO). Fasting blood glucose (FBG) was measured using the glucose pilot. Neuronal damage was estimated by histological and behavioral analyses. Phlorizin and glucose were administered by intraperitoneal (i.p.) or intracerebroventricular (i.c.v.) injection. Administration of phlorizin (40, 120 or 200mg/kg, i.p.) significantly and dose-dependently suppressed the elevation of FBG and ischemic neuronal damage. In contrast, phlorizin (10 or 40μg/mouse, i.c.v.) significantly and dose-dependently suppressed ischemic neuronal damage without reducing the elevation of FBG. Moreover, the development of neuronal damage was significantly and dose-dependently exacerbated following i.c.v. administration of glucose (10% or 25% (w/v)), and its exacerbation was suppressed by i.c.v. administration of phlorizin (40μg/mouse). These results suggest that cerebral SGLT is activated by post-ischemic hyperglycemia and may be involved in the exacerbation of ischemic neuronal damage.
Insights
Post-ischemic hyperglycemia exacerbates brain injury by activating sodium-glucose transporters (SGLT). Inhibiting SGLT with phlorizin reduces neuronal damage, suggesting SGLT as a therapeutic target for stroke.
Area of Science:
- Neuroscience
- Biochemistry
- Pathophysiology
Background:
- Post-ischemic hyperglycemia is linked to neuronal damage, but mechanisms remain unclear.
- Sodium-glucose transporters (SGLT) mediate glucose uptake and cellular depolarization.
- SGLT's role in cerebral ischemic stress-induced neuronal injury requires investigation.
Purpose of the Study:
- To determine the involvement of SGLT in cerebral ischemic stress-induced neuronal damage.
- To investigate the therapeutic potential of SGLT inhibition in stroke models.
Main Methods:
- Middle cerebral artery occlusion (MCAO) model in male ddY mice.
- Administration of phlorizin (SGLT inhibitor) and glucose via intraperitoneal and intracerebroventricular routes.
- Assessment of fasting blood glucose, histological neuronal damage, and behavioral changes.
Main Results:
- Phlorizin administration reduced hyperglycemia and neuronal damage in a dose-dependent manner.
- Intracerebroventricular phlorizin suppressed neuronal damage without affecting blood glucose levels.
- Exogenous glucose administration exacerbated neuronal damage, an effect reversed by phlorizin.
Conclusions:
- Cerebral SGLT activation by post-ischemic hyperglycemia contributes to neuronal damage.
- SGLT inhibition represents a potential therapeutic strategy for mitigating ischemic stroke injury.

Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
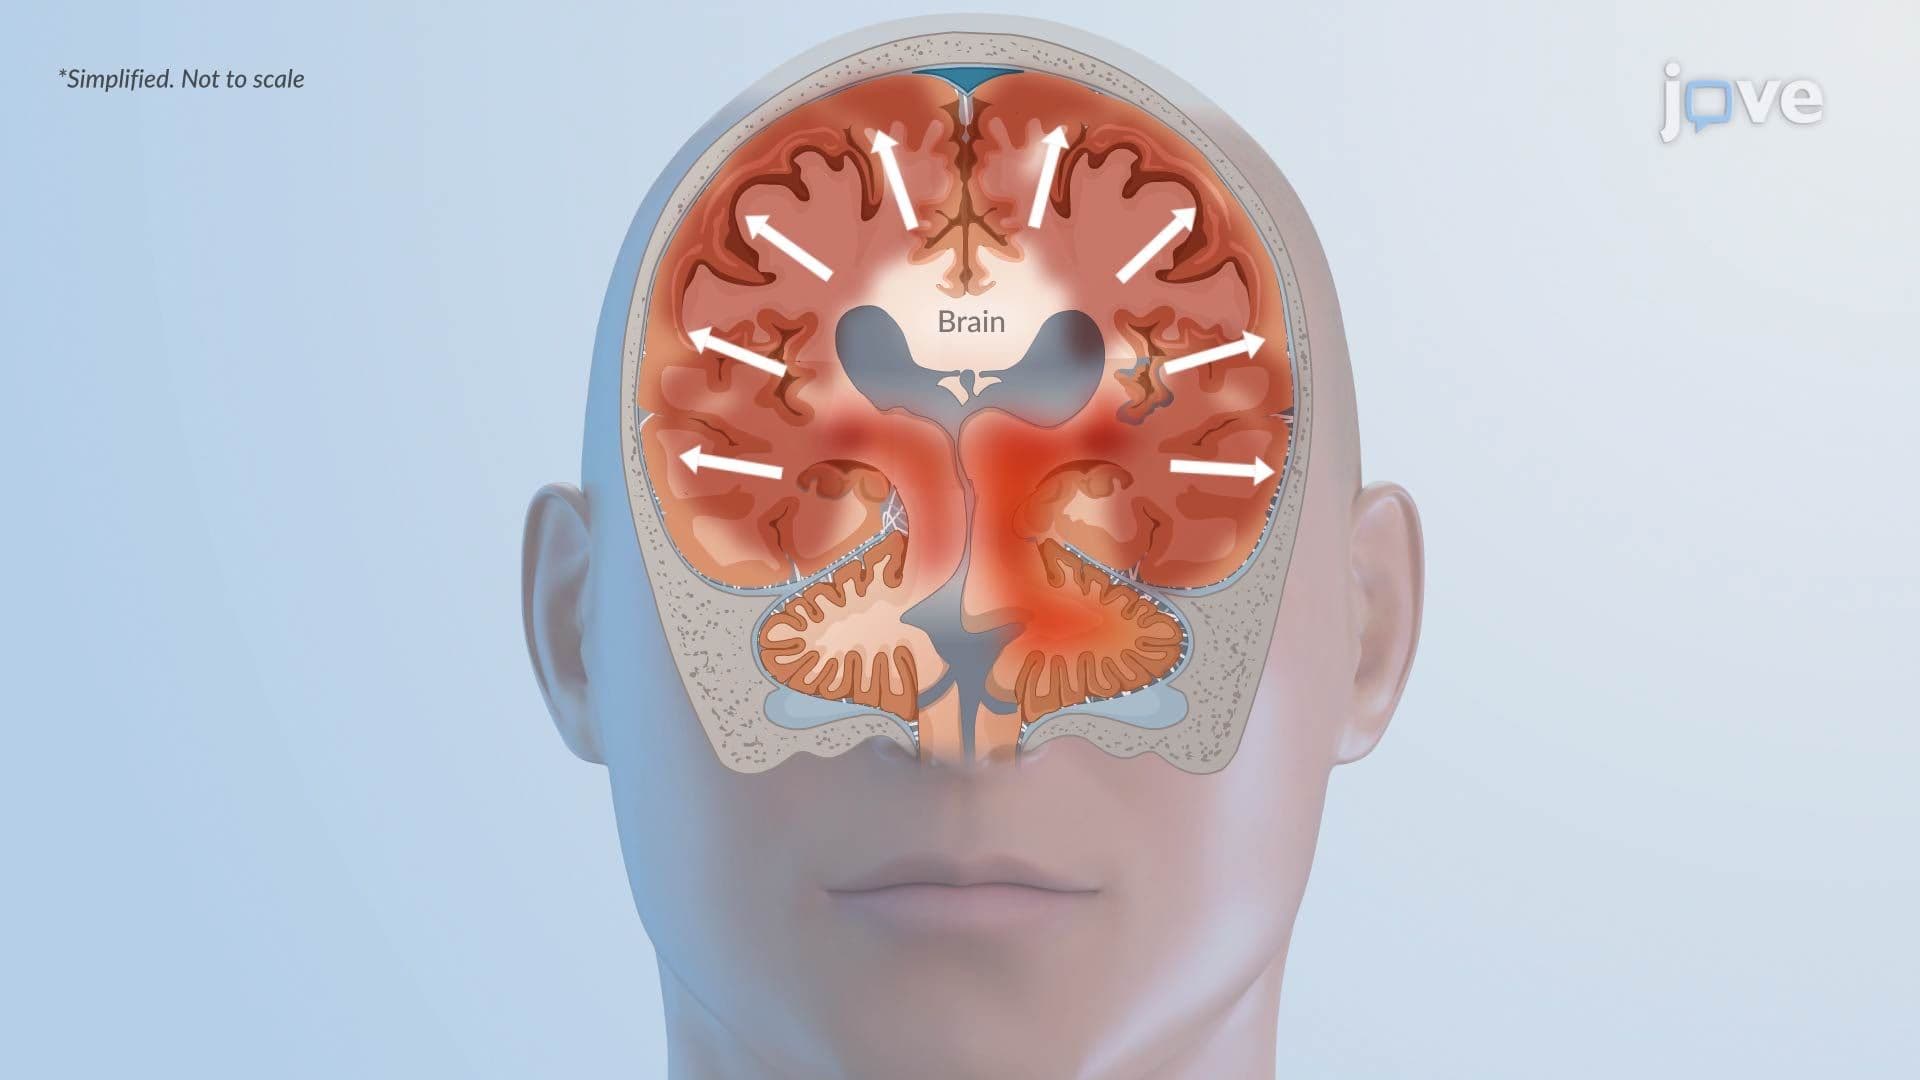 01:21
Cytotoxic Edema: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
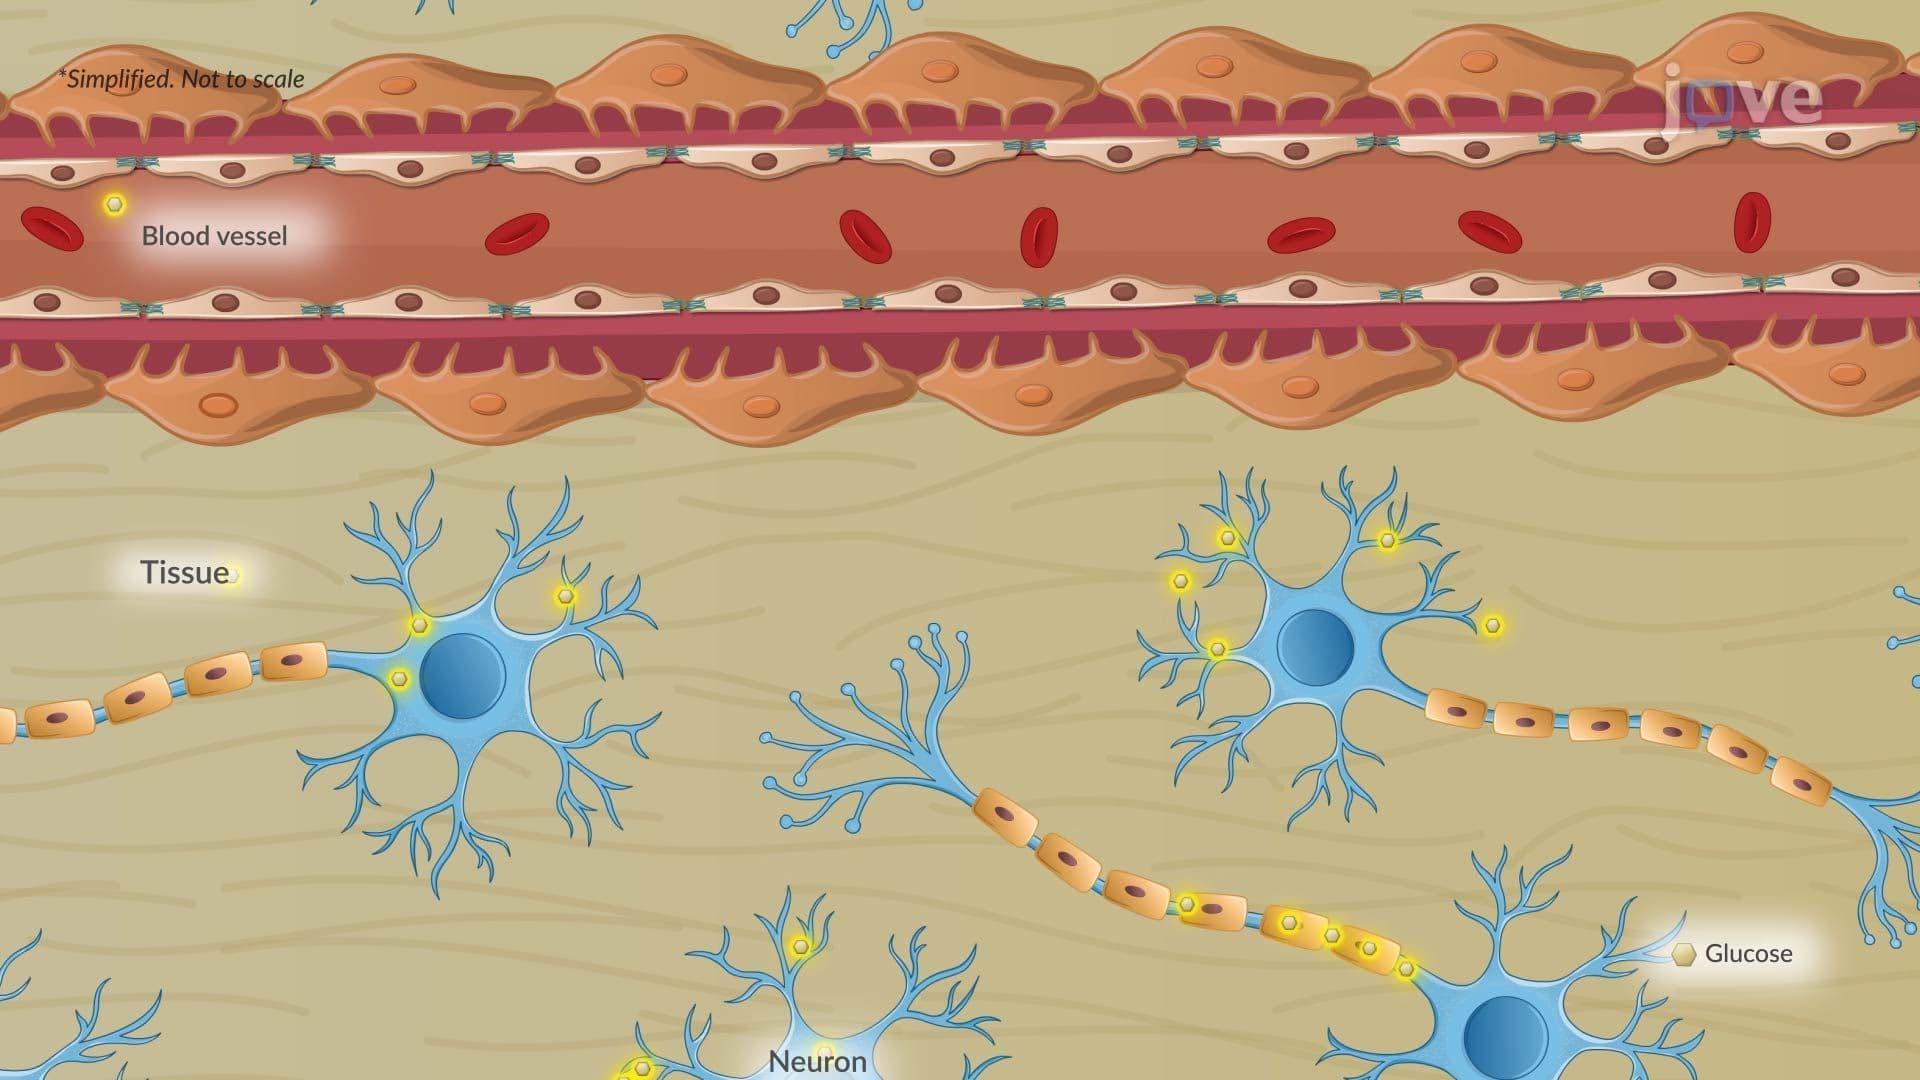 01:22
Diabetic Neuropathy
 01:29
Hyperglycemia
 01:22
Cerebral Edema ll: Pathophysiology