Related Experiment Video
Updated: May 17, 2026
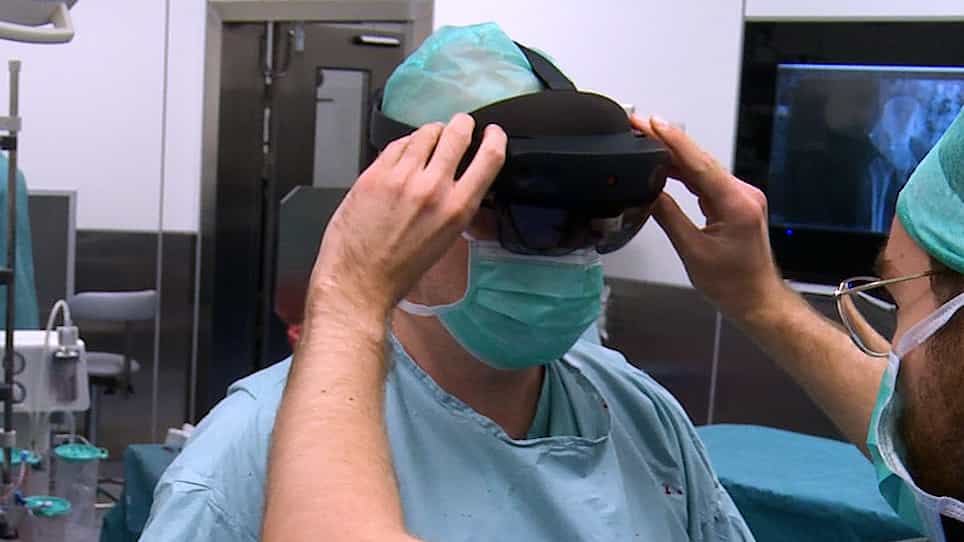

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Twelve-year risk of revision after primary total hip replacement in the U.S. Medicare population
Jeffrey N Katz1, Elizabeth A Wright, John Wright
1Orthopedic and Arthritis Center for Outcomes Research, Brigham and Women's Hospital, 75 Francis Street, OBC - 4-016, Boston, MA 02115. jnkatz@partners.org

Insights
Revision total hip replacement rates are higher in the first 18 months post-surgery. Younger patients and males face increased revision risks, highlighting areas for targeted intervention to improve outcomes.
Area of Science:
- Orthopedic Surgery
- Biostatistics
- Epidemiology
Background:
- Limited population-based data exists on revision rates and risk factors after primary total hip replacement.
- Understanding these factors is crucial for improving long-term joint replacement outcomes.
Purpose of the Study:
- To determine the rates and identify preoperative risk factors for revision total hip replacement (THR).
- To analyze long-term outcomes in a large cohort of Medicare beneficiaries undergoing THR.
Main Methods:
- Retrospective cohort study of Medicare beneficiaries undergoing elective THR for osteoarthritis (1995-1996).
- Follow-up through 2008 using Medicare claims data.
- Kaplan-Meier survival analysis and Cox proportional hazard regression models were used.
Main Results:
- Revision risk was ~2% annually in the first 18 months, then 1% annually.
- Death risk exceeded revision risk by 10x in patients >75 years and 3x in patients 65-75 years.
- Higher revision risk observed in men, patients aged 65-75, and those with lower-volume surgeons.
Conclusions:
- Interventions to reduce revision THR should focus on the initial 18 months post-surgery.
- Younger patients require specific attention due to higher long-term revision likelihood.
- Surgeon volume and patient demographics are significant factors influencing revision rates.
Background:
There is limited population-based literature on rates and risk factors for revision following primary total hip replacement.
Methods:
We performed a retrospective cohort study of Medicare beneficiaries who had elective total hip replacement for osteoarthritis between July 1, 1995, and June 30, 1996. Patients were followed with use of Medicare claims through 2008. The primary end point was revision total hip replacement as indicated by hospital discharge codes according to the International Classification of Diseases, Ninth Revision. We used the Kaplan-Meier method to plot the risks of revision and of death over a twelve-year follow-up period. We used Cox proportional hazard regression models to identify preoperative risk factors for revision of primary total hip replacement. We conducted sensitivity analyses to account for competing risks of major comorbid conditions.
Results:
The risk of revision total hip replacement for patients remaining alive was approximately 2% per year for the first eighteen months and then 1% per year for the remainder of the follow-up period. The absolute risk of death over the twelve-year follow-up period exceeded the risk of revision total hip replacement by a factor of ten (59% vs. 5.7%) in patients older than seventy-five years at the time of primary total hip replacement and by a factor of three (29% vs. 9.4%) in patients sixty-five to seventy-five years old at the time of surgery. In multivariate Cox proportional hazard models, the relative risk of revision was higher in men than in women (hazard ratio [HR], 1.23; 95% confidence interval [95% CI], 1.15, 1.31) and in patients sixty-five to seventy-five years of age at the time of primary total hip replacement than in those over seventy-five years (HR, 1.47; 95% CI, 1.37, 1.58). Patients of surgeons who performed fewer than six total hip replacements annually in the Medicare population had a higher risk of revision than those whose surgeons performed more than twelve per year (HR, 1.21; 95% CI, 1.12, 1.32).
Conclusions:
Efforts to reduce the number of revision hip arthroplasties should be targeted at revisions occurring in the first eighteen months following the index arthroplasty, when revision risk is higher, and at younger patients, who are more likely to survive long enough to require revision. .
