Related Experiment Video
Updated: May 17, 2026
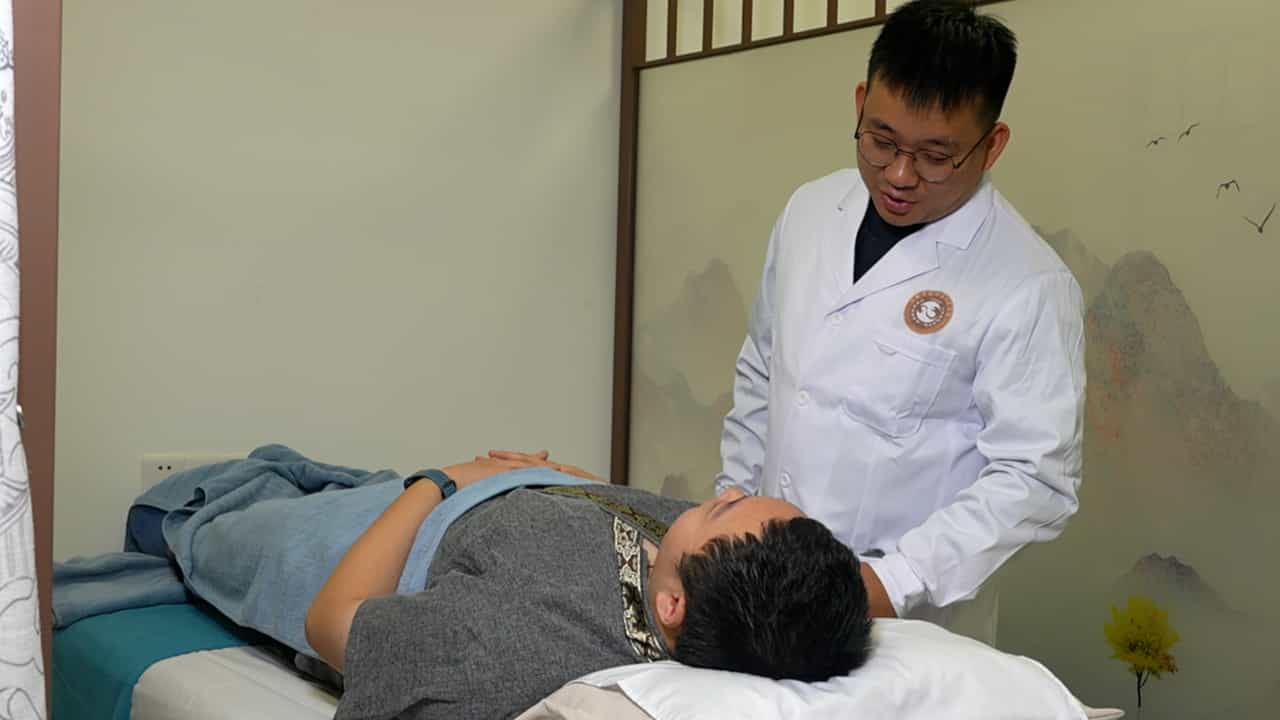
Alternative Therapy for Acute Exacerbation of Chronic Obstructive Pulmonary Disease: Moving Cupping Along Meridians
Published on: September 27, 2024
Effect of an additional dose of indacaterol in COPD patients under regular treatment with indacaterol
Mario Cazzola1, Andrea Segreti, Emanuele Stirpe
1Department of System Medicine, University of Rome 'Tor Vergata', Via Montpellier 1, 00133 Rome, Italy. mario.cazzola@uniroma2.it

Aim:
In this randomized, double-blind, crossover study, we explored the acute effects on respiratory function and safety of an additional dose of indacaterol 150 μg in stable COPD patients regularly treated with a conventional dose of indacaterol 150 μg.
Methods:
On two non-consecutive days, patients inhaled indacaterol 150 μg. After 180 min, they inhaled an additional dose of indacaterol 150 μg or placebo. Lung function, oxygen saturation by pulse oximetry (SpO(2)) and heart rate were measured before the first drug administration and up to 360 min thereafter.
Results:
In both treatment groups, indacaterol induced a significant (P < 0.05) bronchodilation during all the study time. The difference between the FEV(1) AUCs(0-180 min) was not statistically significant (P = 0.971). On the contrary, the difference between the FEV(1) AUCs(180-360 min) was significant (P < 0.0001). However, only 8 out of 20 patients showed a further increase of at least 100 ml from the peak obtained after the first administration of indacaterol 150 μg with the second dose of 150 μg. Indacaterol 150 μg induced a modest but significant decrease in SpO(2) up to 60 min and a second dose of indacaterol 150 μg significantly decreased the SpO(2) mean value up to 360 min.
Conclusion:
This study suggests that it is reasonable and safe to increase the dose of indacaterol in those stable COPD patients who are under regular therapy with indacaterol 150 μg from which they do not draw the maximum benefit because they are unable to perceive bronchodilation. However, only a minority of patients seem to benefit from this dose escalation, at least in terms of spirometric improvement.
Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation