

Bone mineral density in children and young adults with neurofibromatosis type 1
Maya B Lodish1, Urania Dagalakis, Ninet Sinaii
1Section on Endocrinology and Genetics, Eunice Kennedy Shriver National Institute of Child Health and Human Development, National Institutes of Health, Bethesda, Maryland 20892, USA. lodishma@mail.nih.gov

Insights
Children with neurofibromatosis type 1 (NF-1) often have impaired bone health. This study found lumbar spine bone density is particularly affected in pediatric NF-1 patients with high plexiform neurofibroma burden.
Area of Science:
- Pediatric Endocrinology
- Skeletal Biology
- Genetics
Background:
- Neurofibromatosis type 1 (NF-1) is a genetic disorder associated with various complications, including potential bone health issues.
- Children with NF-1, especially those with a significant plexiform neurofibroma burden, may be at higher risk for impaired bone development.
- Bone densitometry is increasingly utilized to assess skeletal health in pediatric populations with chronic conditions.
Purpose of the Study:
- To evaluate bone mineral apparent density (BMAD) and whole-body bone mineral content (BMC)/height in pediatric patients with NF-1.
- To investigate the relationship between plexiform neurofibroma burden and bone health parameters in this cohort.
- To identify specific skeletal sites most affected by impaired bone density in pediatric NF-1.
Main Methods:
- Sixty-nine pediatric and young adult patients with NF-1 were enrolled (age range 5.2-24.8 years).
- Hologic dual-energy X-ray absorptiometry (DXA) scans were performed to measure lumbar spine (LS 2-4), femoral neck (FN), and total body BMC/height.
- Bone mineral apparent density (BMAD) was calculated to normalize bone mineral density for bone volume, and Z-scores were determined. Impaired bone mineral density was defined as a Z-score ≤-2.
Main Results:
- Nearly half (47%) of patients exhibited impaired bone mineral density at any site.
- Lumbar spine (LS) showed the highest prevalence of impaired bone density (36%), followed by total body BMC/height (20%) and femoral neck (FN) (18%).
- Lumbar spine BMAD Z-scores were significantly more impaired (-1.60 ± 1.26) compared to the femoral neck (-0.54 ± 1.58) and total body BMC/height (-1.16 ± 0.90).
- A negative correlation was observed between plexiform neurofibroma burden and lumbar spine BMAD (r(s)=-0.36, P=0.01), indicating poorer bone density with higher tumor burden.
Conclusions:
- Pediatric and young adult patients with NF-1 frequently experience impaired bone health, particularly at the lumbar spine.
- The lumbar spine appears to be the most vulnerable skeletal site for bone density reduction in this population.
- Increased plexiform neurofibroma burden is associated with more severe impairment of lumbar spine bone mineral apparent density in NF-1 patients.
Abstract:
Concern for impaired bone health in children with neurofibromatosis type 1 (NF-1) has led to increased interest in bone densitometry in this population. Our study assessed bone mineral apparent density (BMAD) and whole-body bone mineral content (BMC)/height in pediatric patients with NF-1 with a high plexiform neurofibroma burden. Sixty-nine patients with NF-1 (age range 5.2-24.8; mean 13.7 ± 4.8 years) were studied. Hologic dual-energy X-ray absorptiometry scans (Hologic, Inc., Bedford, MA, USA) were performed on all patients. BMD was normalized to derive a reference volume by correcting for height through the use of the BMAD, as well as the BMC. BMAD of the lumbar spine (LS 2-4), femoral neck (FN), and total body BMC/height were measured and Z-scores were calculated. Impaired bone mineral density was defined as a Z-score ≤-2. Forty-seven percent of patients exhibited impaired bone mineral density at any bone site, with 36% at the LS, 18% at the FN, and 20% total BMC/height. BMAD Z-scores of the LS (-1.60 ± 1.26) were more impaired compared with both the FN (-0.54 ± 1.58; P=0.0003) and the whole-body BMC/height Z-scores (-1.16 ± 0.90; P=0.036). Plexiform neurofibroma burden was negatively correlated with LS BMAD (r(s)=-0.36, P=0.01). In pediatric and young adult patients with NF-1, LS BMAD was more severely affected than the FN BMAD or whole-body BMC/height.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
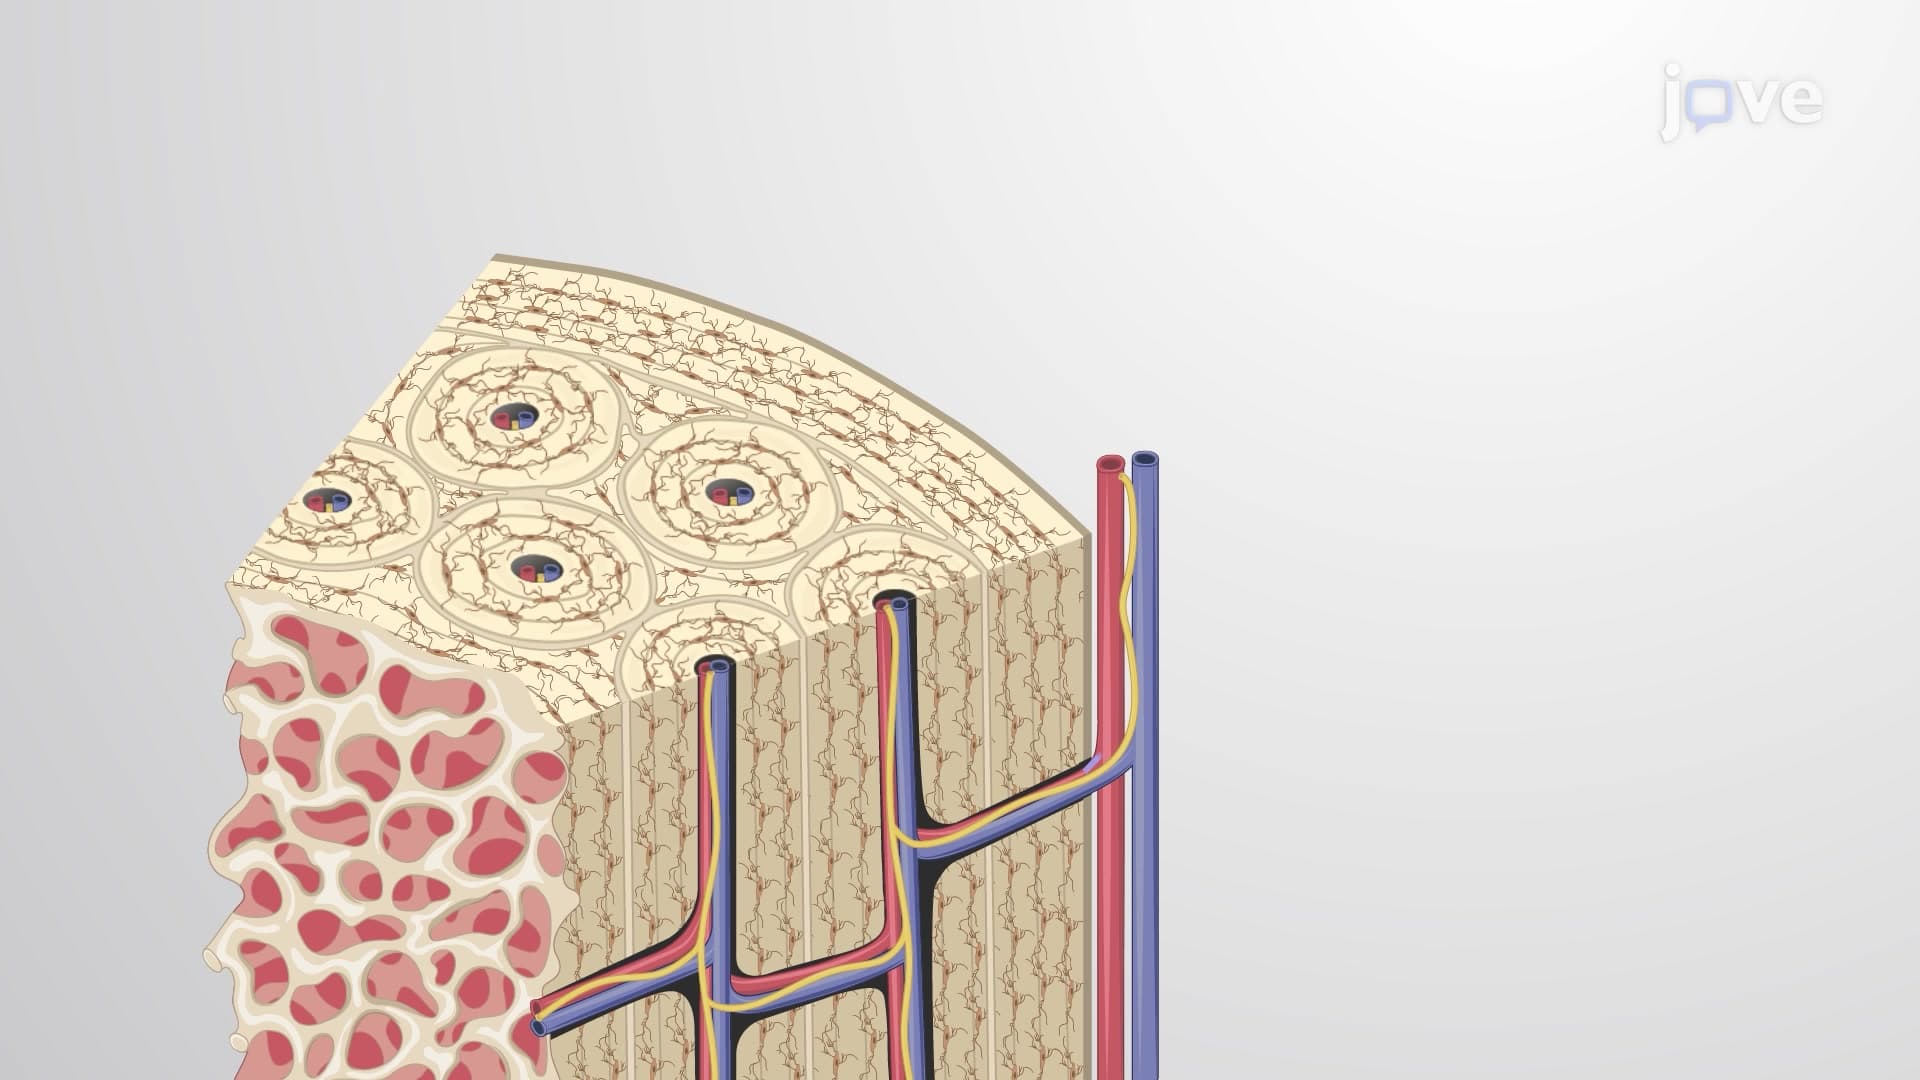
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:18
The Bone Matrix
 01:09
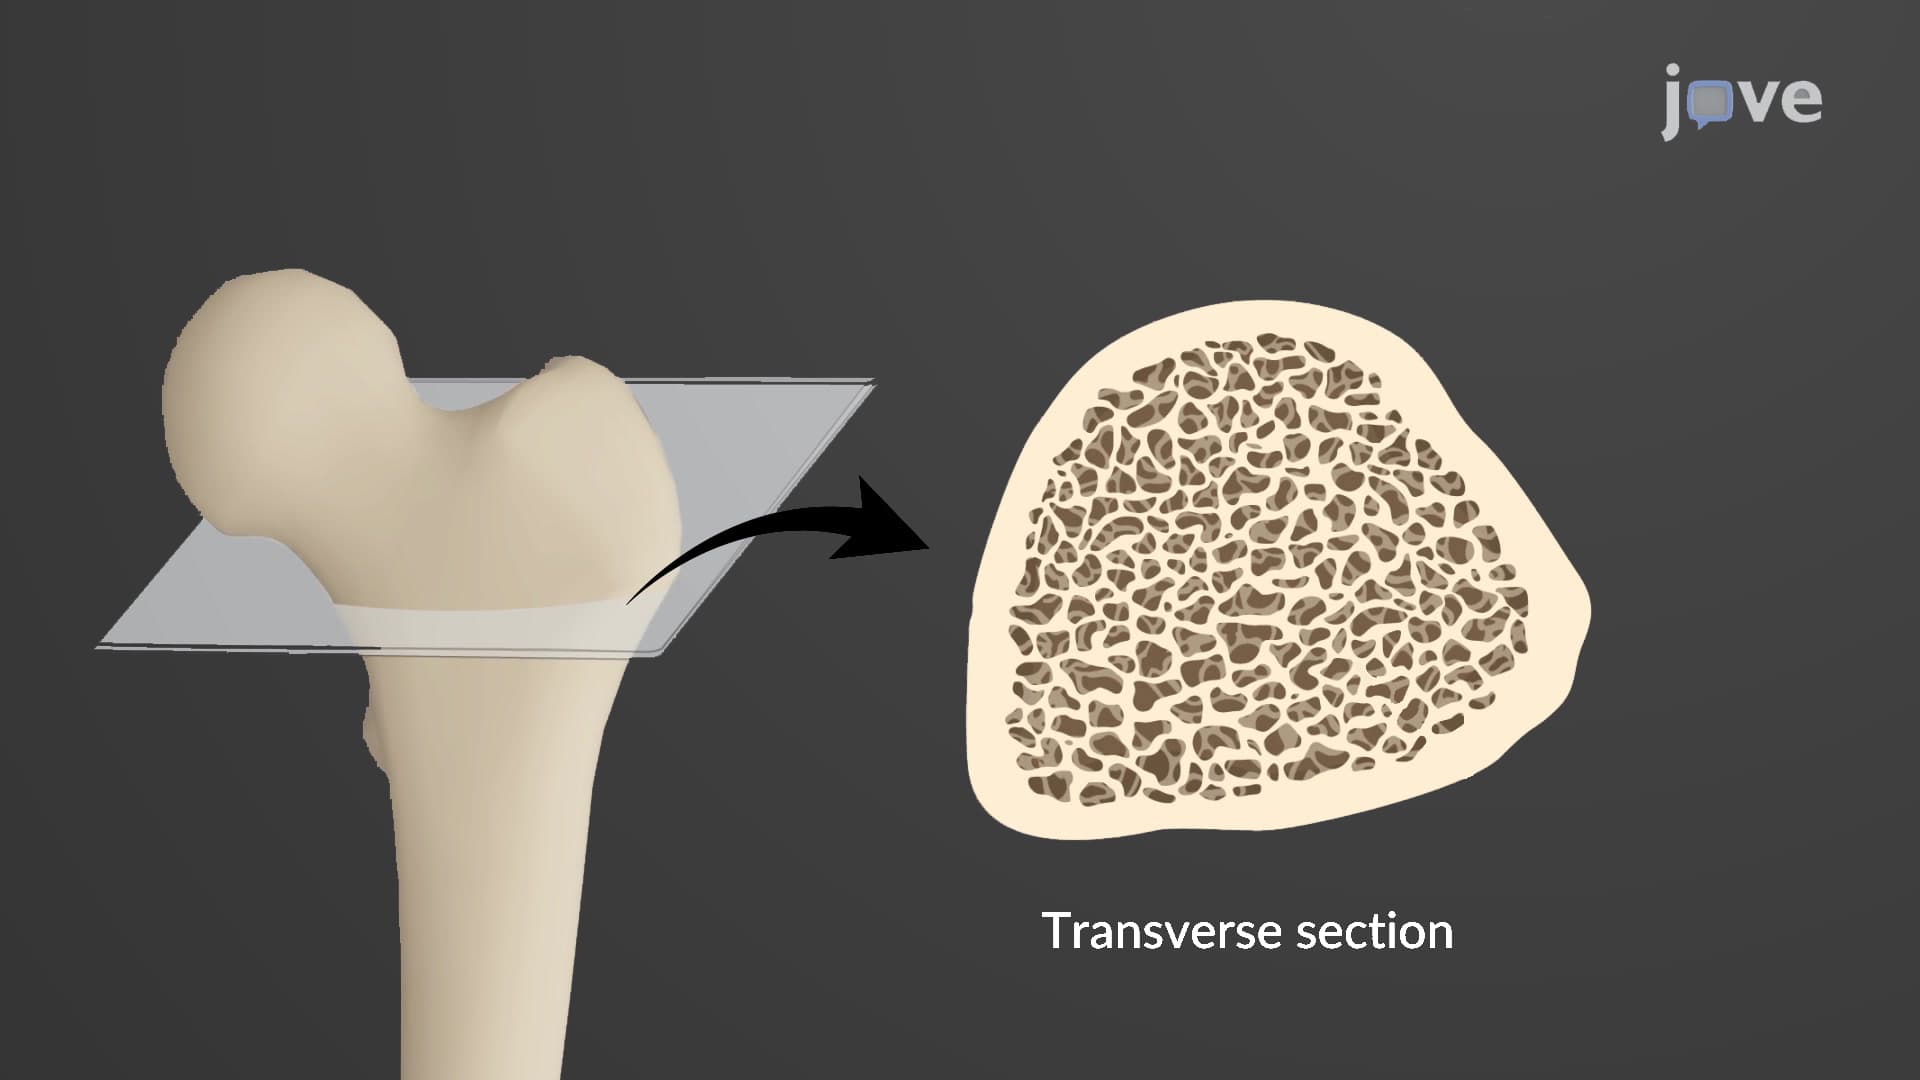
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...