Related Experiment Video
Updated: May 17, 2026
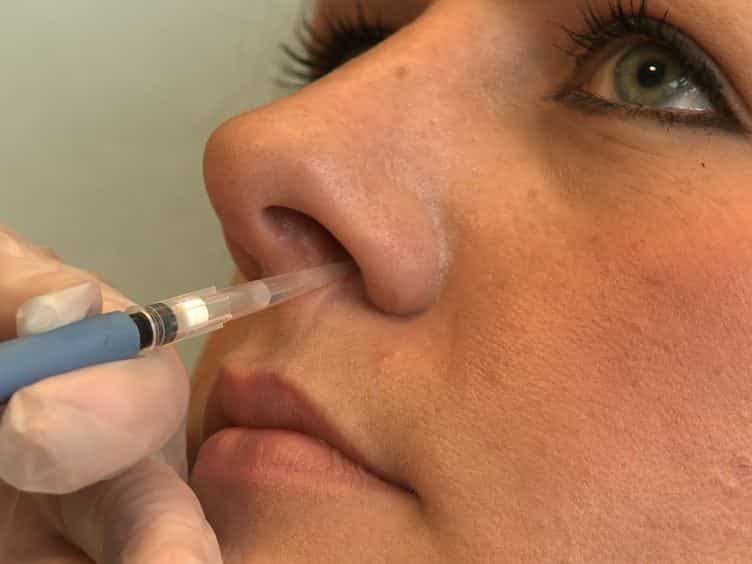

Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
Invasive pneumococcal disease and 7-valent pneumococcal conjugate vaccine, the Netherlands

Insights
The 7-valent pneumococcal conjugate vaccine (PCV7) significantly reduced invasive pneumococcal disease (IPD) in young children and older adults in the Netherlands. However, non-PCV7 serotype IPD cases increased, particularly in older adults.
Area of Science:
- * Public Health
- * Infectious Diseases
- * Vaccinology
Background:
- * The Netherlands implemented the 7-valent pneumococcal conjugate vaccine (PCV7) into its national immunization program for newborns in April 2006.
- * Invasive pneumococcal disease (IPD) remains a significant public health concern globally, necessitating ongoing surveillance and vaccine impact assessment.
Purpose of the Study:
- * To evaluate the impact of PCV7 introduction on the incidence and characteristics of IPD in the Netherlands.
- * To compare IPD trends before and after PCV7 implementation, focusing on different age groups and serotypes.
Main Methods:
- * A retrospective study design comparing IPD cases before (June 2004-June 2006) and after (June 2008-June 2010) PCV7 introduction.
- * Culture-confirmed IPD cases were identified through a network of 9 sentinel laboratories representing approximately 25% of the Dutch population.
- * Analysis included IPD incidence, patient demographics, disease characteristics, serotype distribution, and case fatality rates.
Main Results:
- * Significant reductions in overall IPD incidence were observed in children under 2 years (60% decrease) and individuals over 65 years (13% decrease).
- * A notable trend of increasing non-PCV7 serotype IPD infections occurred across all age groups, with the most substantial rise in adults aged 50-64 (37%) and over 65 (25%).
- * The proportion of immunocompromised individuals among adult IPD patients increased. Overall IPD-related mortality decreased from 16% to 12% due to a lower case-fatality rate for non-PCV7 serotype infections.
Conclusions:
- * PCV7 vaccination has been effective in reducing the burden of IPD, especially in the youngest and oldest populations in the Netherlands.
- * The emergence and increase of non-PCV7 serotype IPD highlight the need for ongoing surveillance and potentially broader-spectrum pneumococcal vaccines.
- * The findings underscore the dynamic nature of IPD epidemiology following vaccine introduction and the importance of monitoring serotype replacement.
Abstract:
In the Netherlands, the national immunization program includes 7-valent pneumococcal conjugate vaccine (PCV7) for all newborns born after April 1, 2006. We compared the incidence of invasive pneumococcal disease (IPD) and patient and disease characteristics before PCV7 introduction (June 2004-June 2006) with those after PCV7 introduction (June 2008-June 2010). Culture-confirmed IPD cases were identified by 9 sentinel laboratories covering ≈25% of the Dutch population. Significant declines in overall IPD incidence were observed in children <2 (60%) and in persons >65 (13%) years of age. A trend toward gradual increases in non-PCV7 serotype IPD infections was observed in all age groups; the largest increases were among persons 50-64 (37%) and >65 (25%) years of age. In adults, the proportion of immunocompromised persons increased among IPD patients. Overall, deaths from IPD decreased from 16% to 12% because of a lower case-fatality rate for persons with non-PCV7 serotype IPD.


Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:26
Bacterial Meningitis II: Pathophysiology
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:22
Bacterial Meningitis I: Introduction
 01:29
Pneumonia I: Introduction