Related Experiment Video
Updated: May 17, 2026
Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
A randomized trial of hemithyroidectomy versus Dunhill for the surgical management of asymmetrical multinodular
Juan J Sancho1, Rosa Prieto, Juan P Dueñas
1Endocrine Surgery Unit, Hospital del Mar, Passeig Maritim 25-29, Barcelona, Spain.

Objective:
To assess the immediate and long-term clinical results of 2 different surgical procedures for the treatment of asymmetrical multinodular goiter (AMG).
Background:
Half of the patients presenting with a single benign thyroid nodule have contralateral subclinical disease. There is a controversy whether these patients should be treated with hemithyroidectomy (HMT) or with a more extensive procedure.
Methods:
Adult patients with a benign unilateral dominant nodule and contralateral nodule(s) with a diameter of less than 10 mm detected on neck ultrasonography were randomized to HMT or Dunhill (DUN). Rates of complications, remnant growth, incidental carcinoma, and reoperation were assessed.
Results:
A total of 118 patients (F/M:110/8, mean age 43 years) were included and randomized: 65 to HMT and 53 to DUN. After randomization, 28 patients were excluded leaving 47 HMT and 43 DUN long-term (55 ± 35 months) evaluable patients. Mean nodule size was 38 and 6 mm for the dominant and contralateral nodules, respectively. No differences were found in operative time, accidental parathyroidectomy, parathyroid autotransplantation, or wound complications. Transient hypocalcemia was more common in DUN (30% vs 8%; P < 0.001). No permanent complications were observed. At the last follow-up visit, thyroid-stimulating hormone was similar in both groups. Remnant growth (20 vs 0%; P < 0.001), appearance of new nodules (55 vs 14%; P < 0.001), and overall reoperation rate (9.2 vs 1.8%, P = 0.2) were more common in HMT, mostly because of undiagnosed cancer requiring completion thyroidectomy. Thirty percent of HMTs developed hypothyroidism and required long-term T4 supplementation.
Conclusions:
DUN appears superior to HMT for the treatment of AMG in terms of early reoperation for missed carcinomas and disease progression. Both procedures have a similarly uneventful postoperative course.
Related Concept Videos
 01:27
Goiter
 01:27
Hyperthyroidism II: Pathophysiology
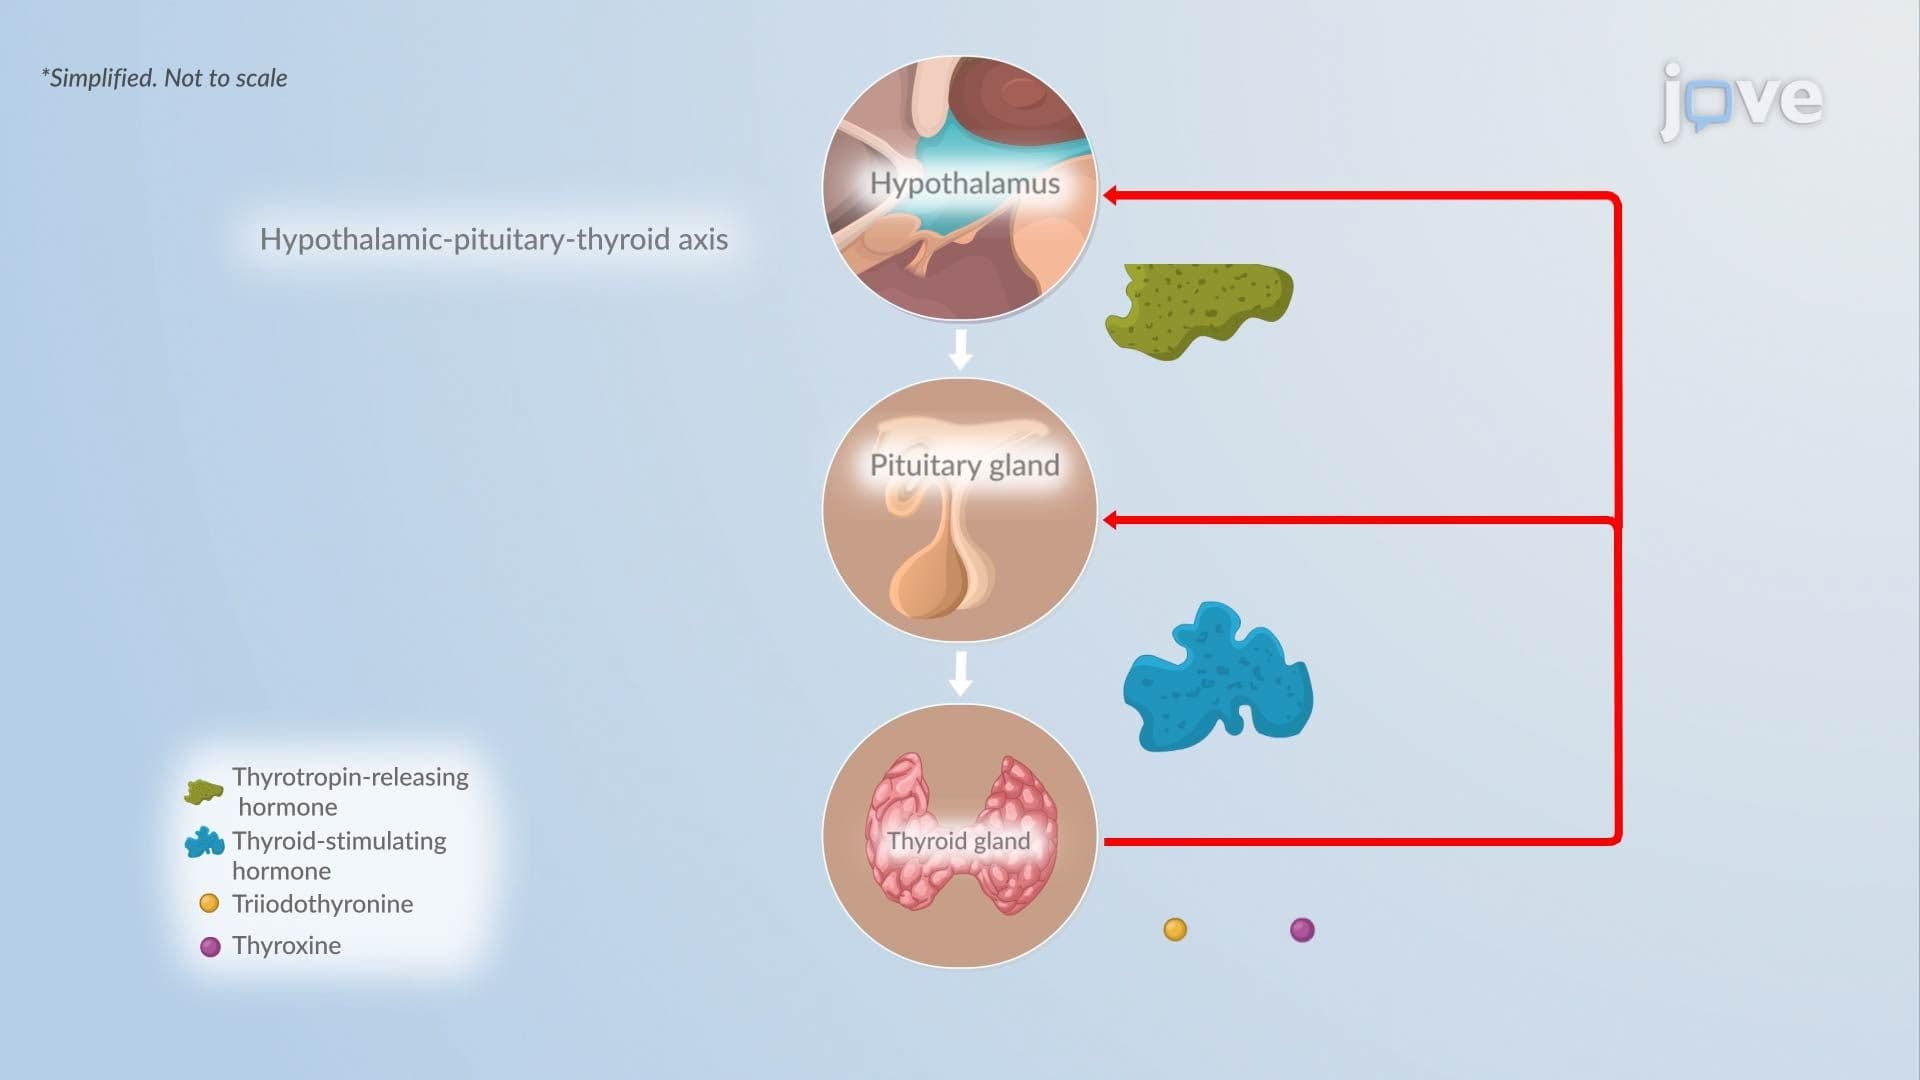 01:25
Hyperthyroidism I: Introduction
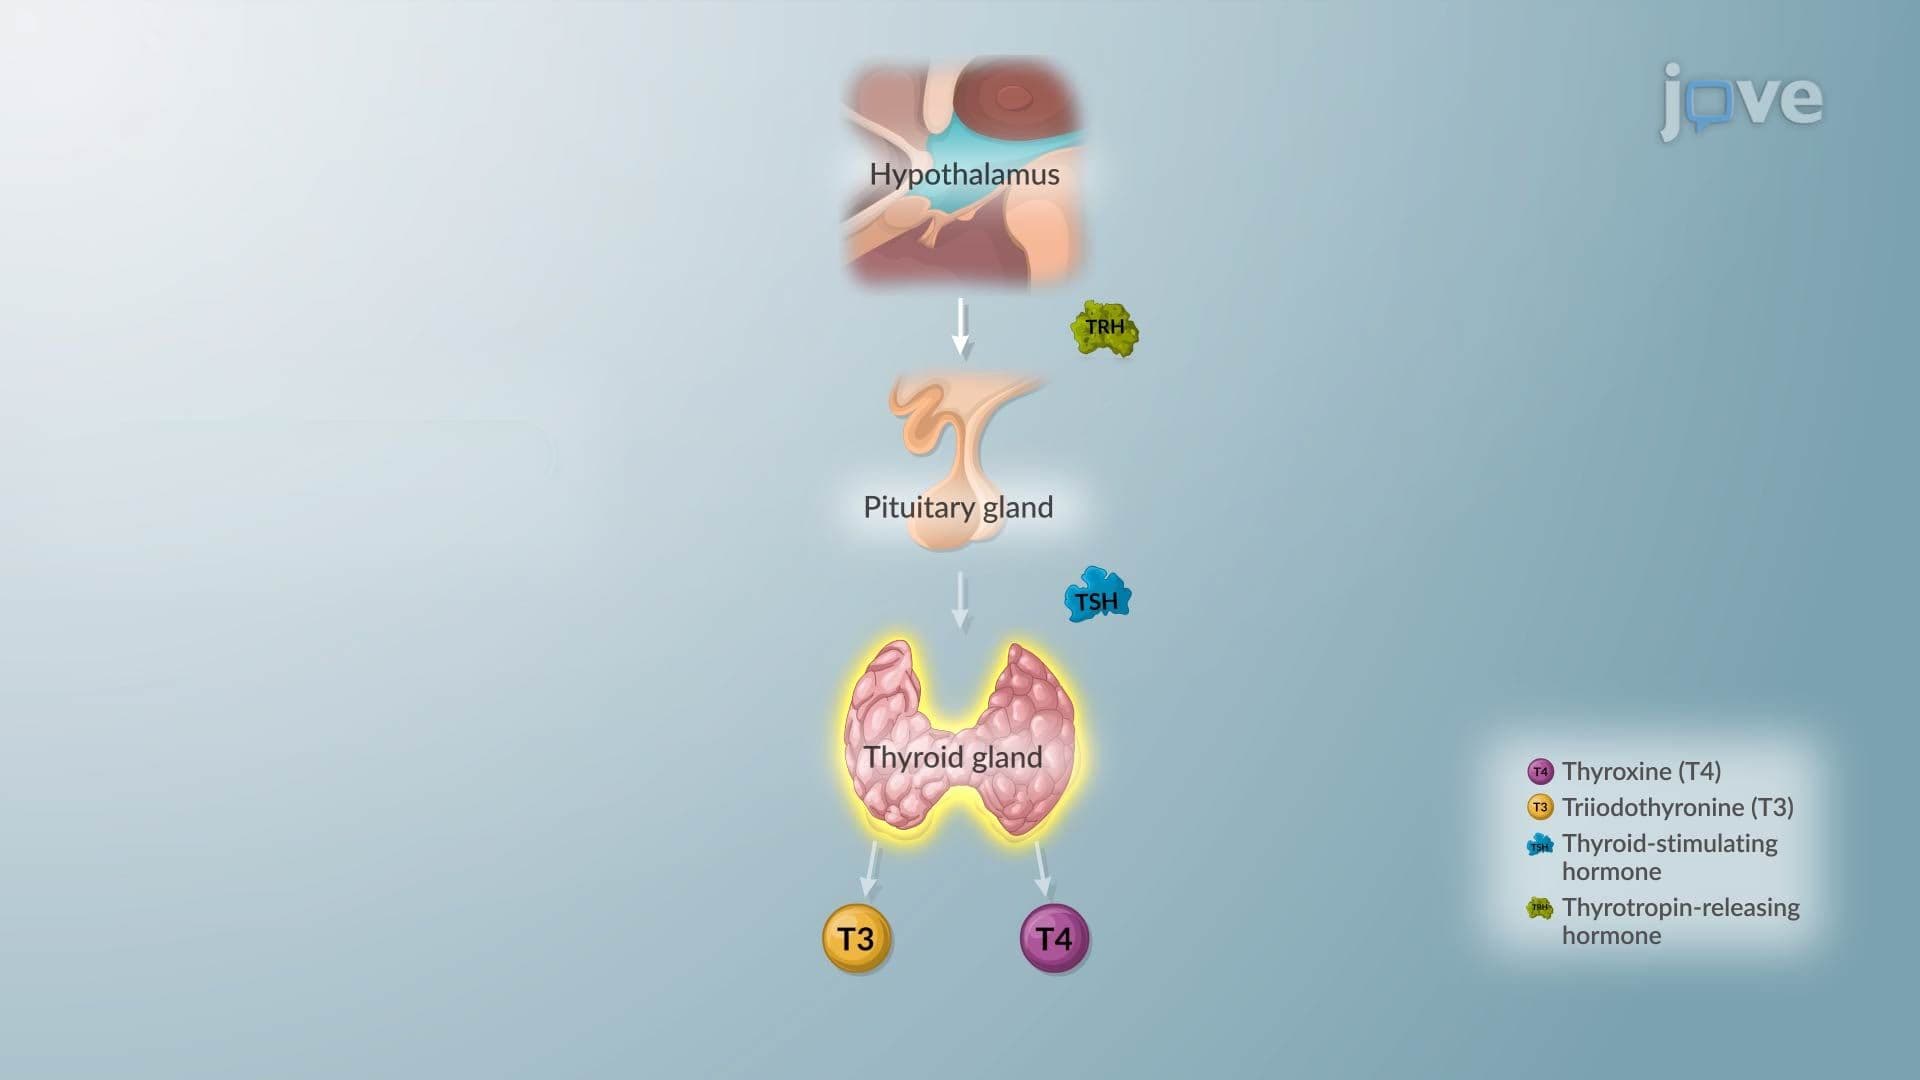 01:23
Hypothyroidism II: Pathophysiology