Related Experiment Video
Updated: May 17, 2026
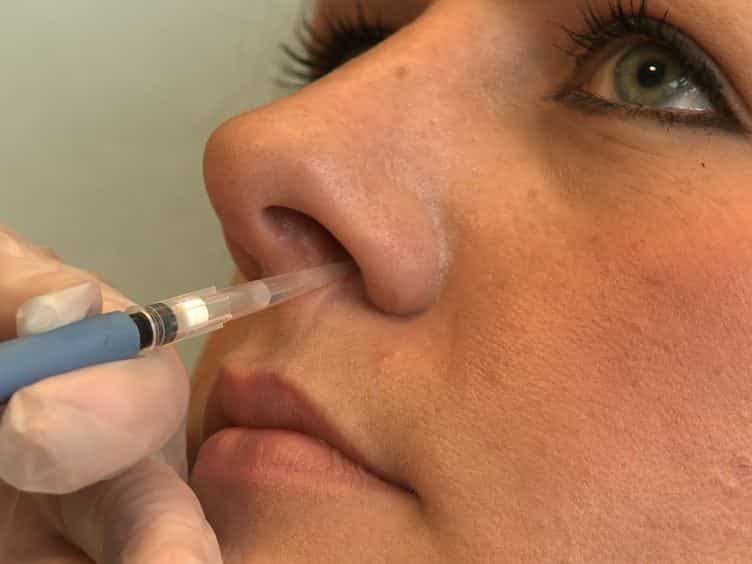
Experimental Human Pneumococcal Carriage
Published on: February 15, 2013
Vaccination of risk groups in England using the 13 valent pneumococcal conjugate vaccine: economic analysis
Mark H Rozenbaum1, Albert Jan van Hoek, Douglas Fleming
1Unit of PharmacoEpidemiology and PharmacoEconomics, Department of Pharmacy, University of Groningen, Antonius Deusinglaan 1, 9713 AV Groningen, Netherlands. m.h.rozenbaum@rug.nl

Objective:
To estimate the cost effectiveness of vaccinating people with high risk conditions against invasive pneumococcal disease using the 13 valent pneumococcal conjugate vaccine.
Design:
Economic evaluation using a cohort model from the perspective of healthcare providers.
Setting:
England.
Participants:
People aged 2 years and older at increased risk of invasive pneumococcal disease due to chronic kidney disease; splenic dysfunction; HIV infection; a compromised immune system; chronic heart, liver, or respiratory disease; or diabetes.
Main Outcome Measures:
Costs, gains in life years and quality adjusted life years (QALYs), and incremental cost effectiveness ratios.
Results:
Increasing indirect protection resulting from the vaccination programme of infants using the 13 valent pneumococcal conjugate vaccine means that the burden of disease preventable by targeting high risk groups will diminish in time. Under base case assumptions--that is, no overall impact on non bacteraemic pneumonia in high risk groups and assuming the high risk vaccination programme would be launched two to three years after the infant programme--the incremental cost effectiveness ratio was estimated to be more than £30,000 (€37,216; $48,210) per QALY gained for most risk groups. If, however, the vaccine does not offer protection against non-bacteraemic pneumococcal pneumonia or the vaccine was introduced concomitantly with the infant 13 valent pneumococcal conjugate vaccination programme then vaccinating high risk people would (more) likely be cost effective. Sensitivity analyses showed that the cost effectiveness was particularly sensitive to assumed herd benefits and vaccine efficacy estimates.
Conclusion:
Under base case assumptions it is unlikely that a pneumococcal vaccination programme aimed at risk groups could be considered cost effective. Uncertainty could be substantially reduced by establishing the effectiveness of the 13 valent pneumococcal conjugate vaccine against non-bacteraemic pneumococcal pneumonia, particularly in at risk groups.
More Related Videos
 11:32
Following in Real Time the Impact of Pneumococcal Virulence Factors in an Acute Mouse Pneumonia Model Using Bioluminescent Bacteria
Published on: February 23, 2014
 13:47
Opsono-Adherence Assay to Evaluate Functional Antibodies in Vaccine Development Against Bacillus anthracis and Other Encapsulated Pathogens
Published on: May 19, 2020
Related Concept Videos
 01:51
Vaccinations
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...
 01:21
Vaccines
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: