Related Experiment Video
Updated: May 17, 2026
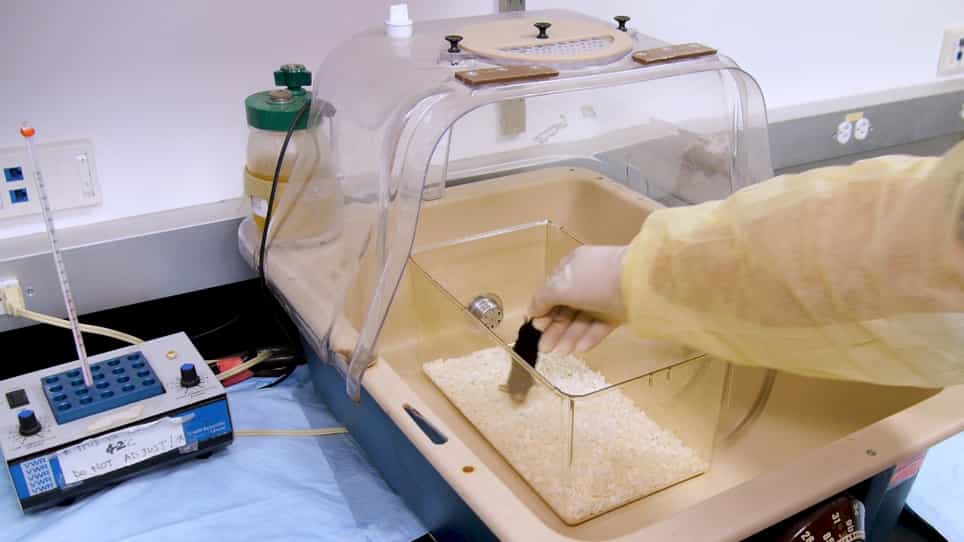

Implantation of an Isoproterenol Mini-Pump to Induce Heart Failure in Mice
Published on: October 3, 2019
Cardiotoxic and cardioprotective features of chronic β-adrenergic signaling
Xiaoying Zhang1, Christopher Szeto, Erhe Gao
1Cardiovascular Research Center, Department of Physiology, Temple University School of Medicine, Philadelphia, PA 19140, USA.

Rationale:
In the failing heart, persistent β-adrenergic receptor activation is thought to induce myocyte death by protein kinase A (PKA)-dependent and PKA-independent activation of calcium/calmodulin-dependent kinase II. β-adrenergic signaling pathways also are capable of activating cardioprotective mechanisms.
Objective:
This study used a novel PKA inhibitor peptide to inhibit PKA activity to test the hypothesis that β-adrenergic receptor signaling causes cell death through PKA-dependent pathways and cardioprotection through PKA-independent pathways.
Methods And Results:
In PKA inhibitor peptide transgenic mice, chronic isoproterenol failed to induce cardiac hypertrophy, fibrosis, and myocyte apoptosis, and decreased cardiac function. In cultured adult feline ventricular myocytes, PKA inhibition protected myocytes from death induced by β1-adrenergic receptor agonists by preventing cytosolic and sarcoplasmic reticulum Ca(2+) overload and calcium/calmodulin-dependent kinase II activation. PKA inhibition revealed a cardioprotective role of β-adrenergic signaling via cAMP/exchange protein directly activated by cAMP/Rap1/Rac/extracellular signal-regulated kinase pathway. Selective PKA inhibition causes protection in the heart after myocardial infarction that was superior to β-blocker therapy.
Conclusions:
These results suggest that selective block of PKA could be a novel heart failure therapy.
Insights
Selective inhibition of protein kinase A (PKA) prevents heart failure by blocking PKA-dependent cell death pathways and revealing PKA-independent cardioprotection, offering a novel therapeutic strategy.
Area of Science:
- Cardiovascular Research
- Molecular Cardiology
- Pharmacology
Background:
- Persistent β-adrenergic receptor activation in heart failure contributes to myocyte death via protein kinase A (PKA)-dependent and independent pathways.
- β-adrenergic signaling also activates cardioprotective mechanisms, suggesting a dual role.
Purpose of the Study:
- To investigate the role of PKA in β-adrenergic receptor-induced cell death and cardioprotection using a novel PKA inhibitor peptide.
- To test the hypothesis that PKA-dependent pathways mediate cell death and PKA-independent pathways mediate cardioprotection.
Main Methods:
- Utilized PKA inhibitor peptide transgenic mice and cultured adult feline ventricular myocytes.
- Administered chronic isoproterenol and β1-adrenergic receptor agonists.
- Assessed cardiac hypertrophy, fibrosis, apoptosis, cardiac function, and intracellular calcium handling.
Main Results:
- PKA inhibition prevented isoproterenol-induced cardiac dysfunction, hypertrophy, fibrosis, and apoptosis in mice.
- Inhibition of PKA protected myocytes from agonist-induced death by preventing calcium overload and calcium/calmodulin-dependent kinase II activation.
- Revealed a cardioprotective β-adrenergic signaling pathway (cAMP/exchange protein directly activated by cAMP/Rap1/Rac/extracellular signal-regulated kinase) upon PKA inhibition.
- Selective PKA inhibition demonstrated superior protection post-myocardial infarction compared to β-blocker therapy.
Conclusions:
- Selective blockade of PKA emerges as a potential novel therapeutic approach for heart failure.
- Targeting PKA offers a promising strategy to mitigate cardiac damage and improve function in failing hearts.

Related Concept Videos
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:25
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers