Related Experiment Video
Updated: May 17, 2026


Isolation and Functional Characterization of Human Ventricular Cardiomyocytes from Fresh Surgical Samples
Published on: April 21, 2014
Ventricular repolarization in diabetic patients: characterization and clinical implications
David Clemente1, Telmo Pereira, Susana Ribeiro
1Unidade de Cuidados de Saúde Personalizados de Salvaterra de Magos, Portugal. david_s_clemente@hotmail.com

Background:
Diabetes mellitus is a chronic and very common condition, and there has been lately a considerable increase in its prevalence and incidence. Diabetic patients have increased cardiovascular mortality, in which malignant ventricular arrhythmias seem to be implicated.
Objective:
To study the effects of diabetes on ventricular repolarization parameters responsible for an increased susceptibility to malignant ventricular arrhythmias and/or sudden death.
Methods:
We selected a group of 110 diabetic patients and a group of 110 controls with the same distribution of age, gender and race. We evaluated the following parameters of ventricular repolarization: QT(max), QT(mean), QT(min), QTc(max), QTc(mean), QTc(min), QT and QTc dispersions, T(peak)-T(end) and jT(peak)-jT(end) intervals (D(II), V(2) and V(5)), T(peak)-T(end) and jT(peak)-jT(end) dispersions. The electrocardiograms (ECG) were performed by the same operator and reviewed by the same observers. QT intervals were corrected according to Bazzet's formula.
Results:
We found significantly higher values of QTc(max) (p < 0.001), QTc(mean) (p < 0.001), QT dispersion (p < 0.001), QTc dispersion (p < 0.001), T(peak)-T(end) dispersion ( p < 0.001), and jT(peak)-jT(end) dispersion (p < 0.001) in diabetic patients than in controls. In diabetic patients, we observed prolonged values of QTc interval (5.5%), QT dispersion (0.9%), QTc dispersion (0%), T(peak)-T(end) interval (7.3%), jT(peak)-jT(end) interval (6.4%), T(peak)-T(end) dispersion (16.4%), and jT(peak)-jT(end) dispersion (12.7%). In the controls there were no prolonged values of any of the parameters.
Conclusion:
We concluded that diabetes causes prolongation and spatial dispersion of repolarization, and it may contribute to a greater ventricular electrical instability, whose expected clinical expression may be malignant ventricular arrhythmias.
Related Concept Videos
 01:22
Diabetic Ketoacidosis ll: Pathophysiology
 01:19
Type I Diabetes III: Clinical Manifestations
 01:26
Type I Diabetes II: Pathophysiology
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:30
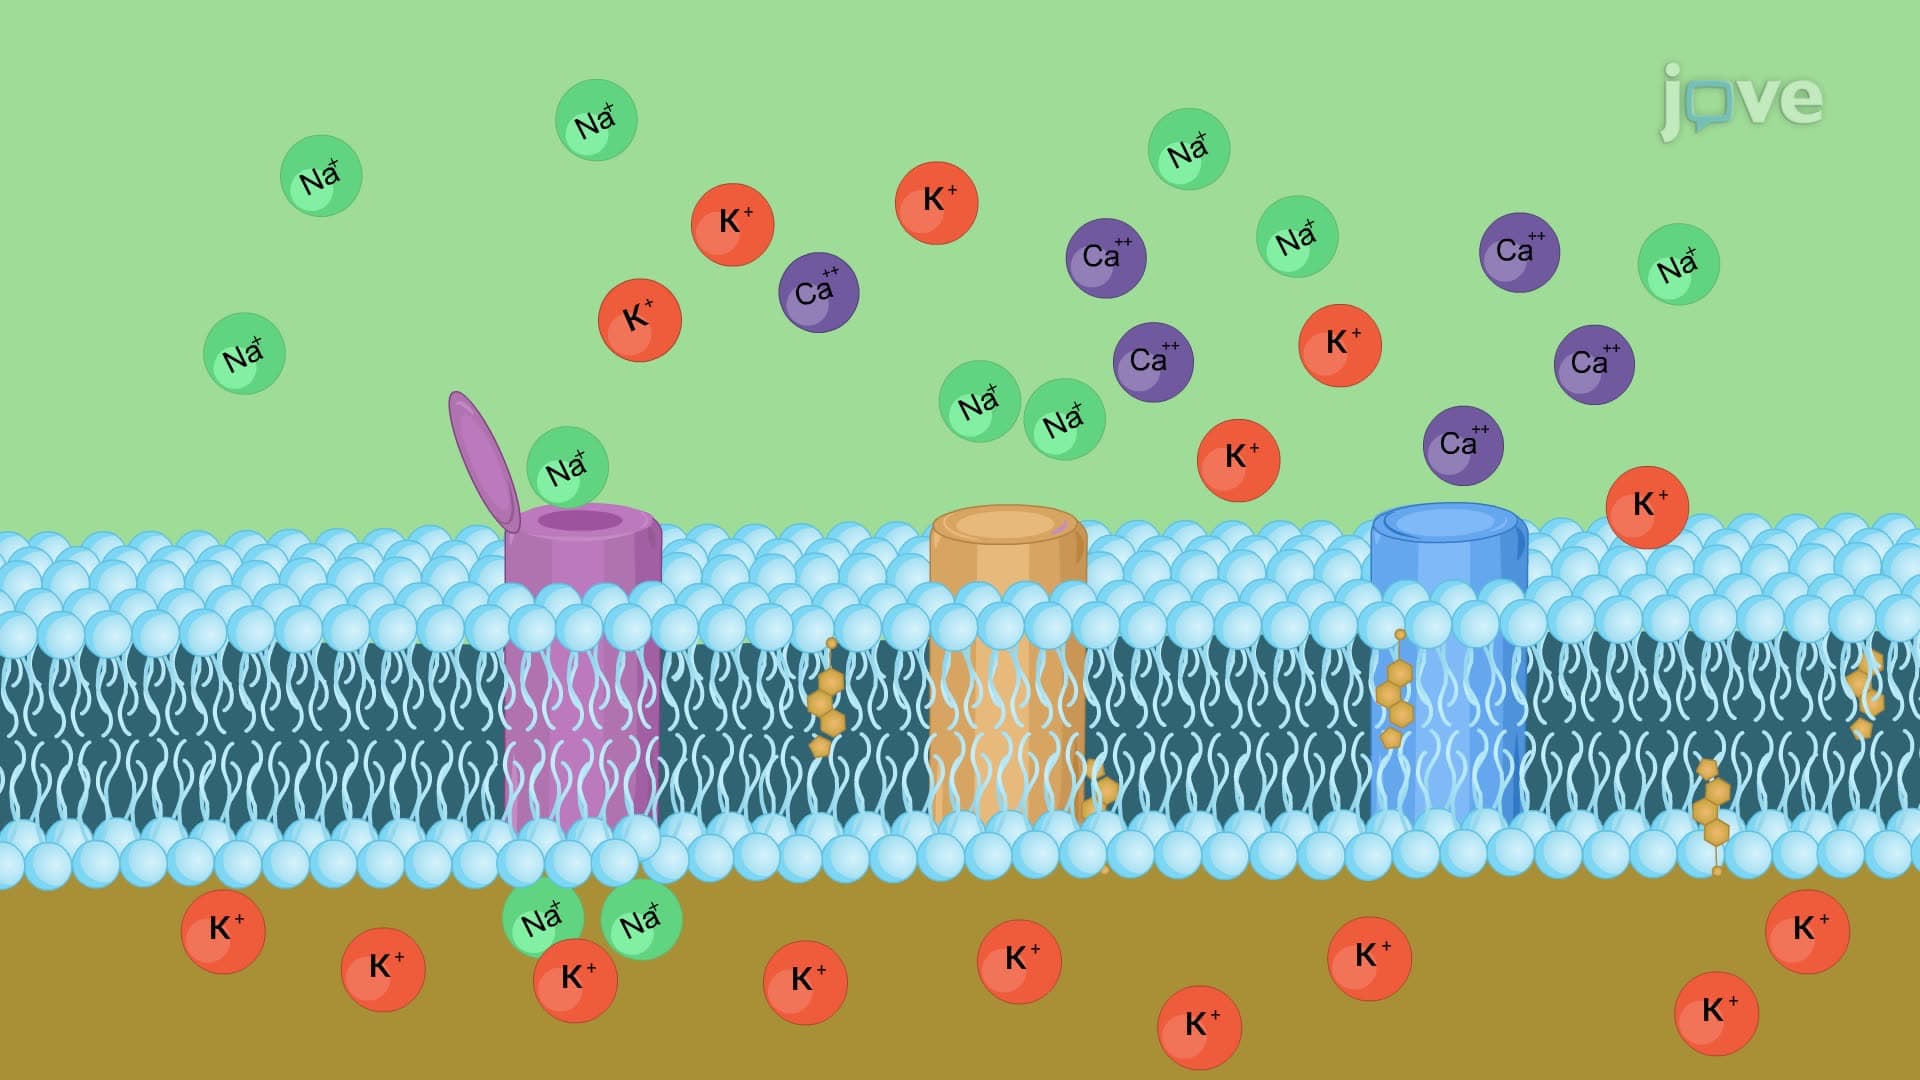
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:24
Type II Diabetes II: Pathophysiology