Related Experiment Video
Updated: May 17, 2026
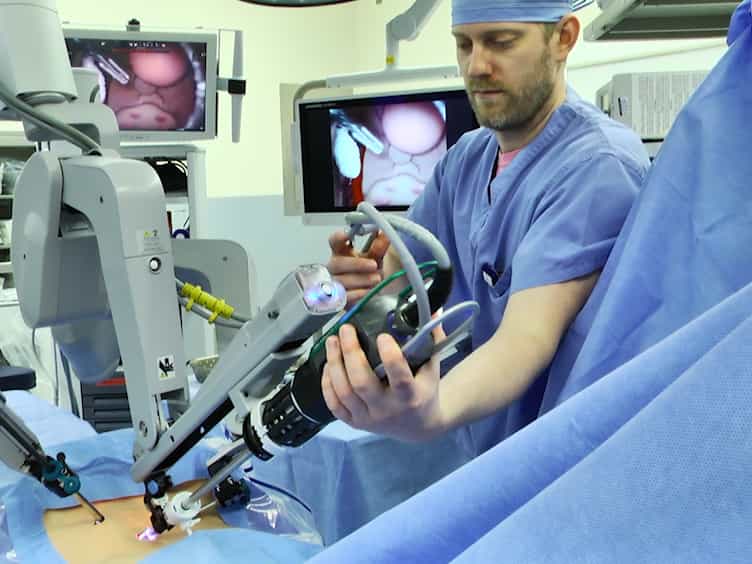

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Does success on the American Board of Surgery general surgery qualifying examination guarantee certifying examination
Thomas W Biester1, Jonathan D Rubright, Andrew T Jones
1American Board of Surgery, Philadelphia, PA 19103-1847, USA. tbiester@absurgery.org

Objective:
The purpose of this study was to explore the relationship between qualifying examination (QE) and certifying examination (CE) results and to determine whether an appropriate cut-point on the QE would predict success on the CE.
Design:
The scaled American Board of Surgery (ABS) QE scores of all first-time examinees from 2006 to 2010 were retrospectively matched to their first-time CE pass/fail decisions. Contingency tables illustrating the QE-CE relationship were constructed and appropriate correlational statistics were computed. A receiver operating characteristic (ROC) curve analysis was constructed, with sensitivity and 1-specificity calculated for each possible QE cut-point used to predicted CE pass/fail classifications. Additionally, the area under the curve (AUC) was calculated.
Participants:
All first-time American Board of Surgery examinees for the Surgery Qualifying Examination from 2006 to 2010.
Results:
A total of 4385 surgeons were analyzed, with QE scores averaging 82.1 ± 5.8 (range, 58-99) and 82.8% of surgeons passing the CE on their first attempt. Contingency tables suggest a moderate relationship between QE and CE performance, although correlation indexes are low (phi = 0.13, point-biserial = 0.23). For the ROC analysis, the AUC = 0.674 (95% CI; 0.654-0.695) provides a better than chance pass/fail classification (p < 0.001), yet does not meet the minimum threshold for acceptability as a predictive test. No QE cut-point accurately predicted CE pass/fail decisions.
Conclusions:
While a moderate relationship between QE scores and CE performance is evident, correlations suggest that the 2 examinations measure different abilities. The low AUC value on the ROC analysis, along with poor predictability at all possible cut-points, show that no appropriate cut-point on the QE predicts success on the CE. These data add to the validity of both tests by providing evidence that distinct latent traits are being measured by both tests.
Related Concept Videos
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:26
Endoscopic Procedures V: ERCP
Patient...